Author Archives: author

Raman Spectroscopy of Boric Acid Daughter Crystals with Different B-isotopes: H311BO3 and H310BO3, and Different Hydrogen and Deuterium Concentrations

DOI: 10.31038/GEMS.2025781

Abstract

First, we present Raman spectroscopic results for commercial boric acid [H3 nBO3] and for the boric acid end members containing 10B and 11B. Furthermore, we show in this short contribution, using boric acid as a daughter mineral in melt and fluid inclusions in pegmatite quard from Elba Island/Italy, that the isotopic composition of boric acid is determinable in situ with an acceptable error of 6%. As a result, we obtain an 11B concentration of 91.9 ± 7.4 %. To our surprise, we also found detectable amounts of D3BO3 in the inclusions, in addition to H3BO3. The very high D concentration clearly shows that a significant portion of the pegmatite-forming fluids originated in the deep mantle.

Keywords

Raman spectroscopy, Pegmatites, Boric acid, Bor isotopes, D3BO3, Supercritical fluids

Introduction

Boron is the fifth element (atomic number) in the periodic table of elements in the third main group. Boron is a rare element, and its concentration in the lithosphere is, according to Rösler and Lange (1975) [1], 12 ppm. In granitic rock, according to the same authors, the concentration is 15 ppm. In Sn-granites from Ehrenfriedersdorf, Central Erzgebirge/Germany, the B-concentration can increase to 132 ppm [2]. In melt and fluid inclusions related to the granites and pegmatites from the Ehrenfriedersdorf deposit, boron concentrations as boric acid increase significantly to 6.88 ± 0.40 % [3] Recent studies [4] showed an extreme rise in B2O3 to 16% (corresponding to nearly 50000 ppm B) with the introduction of supercritical fluids from the mantle. At such high concentrations, it should be possible to determine boron isotopes with Raman spectroscopy. The concentration of boric acid in fluid and melt inclusions in the studied pegmatite from Elba Island can reach up to 20% (vol/vol), corresponding to about 30%(g/g).

Methods and Samples

Methods

Generally, we used boron acid-bearing fluids and melt inclusions in pegmatite quartz from Elba Island. That means fluid- and melt- inclusion with sassolite [H3BO3] daughter crystals. Solid boric acid (sassolite) crystals are easy to identify under crossed Nicols under the transmission light by their peculiar interference color. To select suitable samples, we used a transmission polarization microscope (JenaLab Pol). All Raman spectroscopic studies were performed with a petrographic polarization microscope (BX 43) equipped with an XY- or rotating stage, coupled to the EnSpectr Raman spectrometer R532 (Enhanced Spectrometry, Inc., Mountain View, CA, USA) in transmission. The Raman spectra were recorded in the spectral range of 0–4000 cm-1 using the 30 mW of a single-mode 532 nm laser, an entrance aperture of 20 µm, a holographic grating of 1800 g/mm, and a spectral resolution of 4 cm-1.

Samples

The sample is from the Mining Academy of Freiberg. It’s a small graphic granite sample from Prato alla Valle, located 400 m south of the cemetery of the village San Piero in Campo on the Island of Elba. A detailed description of the paragenesis and the melt and fluid inclusions is in Thomas et al. (2008) [5]. For the study presented here, we used quartz chips approximately 300 µm thick, polished on both sides. All quartz chips contain melt and fluid inclusions with relatively large boric acid (sassolite) [H3BO3] daughter crystals, making the sample suitable for in situ isotope studies. Figure 1 shows such a fluid inclusion.

Figure 1: Fluid inclusion in pegmatite quartz from Elba Island. F -fluid, V – vapor, H3BO3 – boric acid (sassoline), PB – pentaborate: ramanite-(Cs).
Some inclusions also contain meta-boric acid crystals. Generally, the used samples are exceptionally rich in inclusions with soluble B-bearing phases

Basic Experimental Section

At first, we took Raman measurements of commercial boric acid (H3 nBO3 ) and of both pure B-isotopes of solid boric acid. The results are in Table 1.

Table 1: Raman of crystallized H3 nBO3 , H3 10BO3 , and H3 11BO3 (n = 20 measurements each).

Boric acid with different B-isotopes

Raman band (cm-1) H3nBO3  Raman band (cm-1)
10B-isotope
Raman band (cm-1)
11B-isotope

Irel

76.0 ± 1.6

74.2 ± 0.5 75.4 ± 0.2 w
119.1 ± 3.8 118.3 ± 1.0 118.2 ± 0.3

w

207.8 ± 1.6

211.0 ± 0.4 208.3 ± 0.2 m
497.2 ± 3.8 499.7 ± 0.4 498.3 ± 0.2

s

879.8± 0.3

880.1 ± 0.4 880.0 ± 0.2 vs
1092.0 ± 7.2 – –

w

1166.6 ± 2.7

1171.6 ± 0.4 1166.4 ± 0.4 w
1383.5 ± 6.3 1411.9 ± 0.6 1381.8 ± 1.1

w

2294.1 ± 2.7

– – vw
3173.6 ± 4.2 3172.2 ± 1.3 3170.4 ± 0.2

w

3246.4 ± 4.1

3252.0 ± 0.6 3252.0 ± 0.1

w

nB refers to boron of natural abundance with 19.78 % 10B and 80.22% 11B.
Irel – relative intensity: vs – very strong, s – strong, m – medium, w – weak, vw -very weak.

Table 2 presents both Raman lines of boric acid, which show the most significant differences between the two B-isotopes.

Table 2: Raman lines of B-isotopes of solid boric acid with the most substantial differences(for the 532 nm laser: 20 measurements each).

Hilger quartz spectrograph: 253.7 nm

EnSpectr Raman: 532 nm
B-isotopes Raman band
(cm-1)
Raman band
(cm-1)
Raman band
(cm-1)

Raman band
(cm-1)

11B

1166 1373 1165.8 ± 0.3 1380.8 ± 0.9
nB 1168 1375 1166.6 ± 2.7

1383.5 ± 6.3

10B

1173 1422 1171.6 ± 0.4

1411.9 ± 0.6

n – refers to boron of natural abundance with 19.78% 10B and 80.22% 11B.

Results

The basis of the present study is the determination of the Raman spectra of commercial and isotope-pure boric acid. The obtained results were applied to the melt and fluid inclusion in quartz from a graphic pegmatite of the Island of Elba/Italy. The study shows that the ~1380 cm-1 Raman band yields the best results. From 27 studied inclusions, we obtained a mean value of 1383.3 ± 2.3 cm-1. Using the data from Table 2, we obtained a linear curve with a correlation coefficient (R2 = 0.99839) and an 11B concentration of 91.9 ± 7.4 %. For the other Raman line (1165.2 ± 1.65 cm-1), we obtained a similar mean, but with a larger standard deviation. This result may be that the deuterium content influences the position of the Raman line (Figure 2).

Figure 2: Correlation of the B-isotopes in daughter crystals of boric acid in quartz from an Elba Island pegmatite. 11B-isotope content = 4532.64139 – 3.21026 * RS. RS – Raman shift. The black points are the measured ones, and the open points are from Table 2. The data for commercial boric acid were not used for the correlation because of uncontrolled partial fractionation on the microscope specimen slide.

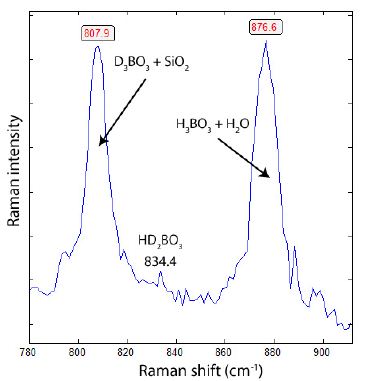
That means the 11B concentration is incredibly high (91.9 ± 7.4 %) in the boric acid samples from the studied Elba Island pegmatite. Besides the high 11B concentration, there are also, in part, very high deuterium concentrations in the boric acid daughter crystals, as shown in Figure 3. The key results are given in Thomas (2025) [6]. Almost every boric acid crystal shows the Raman band for D3BO3. An extreme example is shown in Figure 4, along with the corresponding Raman spectrum from Figure 3. That should be the first natural example of nearby pure D3BO3. Note that each Raman spectrum of pure H3BO3 daughter crystals shows a very weak Raman band at about 807 cm-1, caused by the quartz host.

Figure 3: Raman spectrum of H and D-rich boric acid crystals shown in Figure 4. A perfect separation of both phases (H3BO3 and D3BO3) is at the moment not possible with the used Raman spectrometer, because the solution also contains both components. In the case of D3BO3, the separation from the SiO2 host is not unambiguously possible. However, the intensity of the SiO2 band at 807 cm-1 is usually very low (about 5% of the whole band).

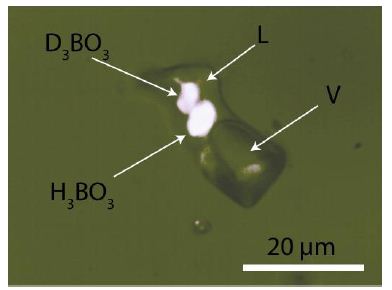
Figure 4 shows the two daughter crystals (D3BO3 and H3BO3), which differ slightly in color and represent different phases.

Figure 4: Fluid inclusion in quartz from the Elba pegmatite with H3BO3 and D3BO3 daughter mineral phases. L – liquid phase, V – vapor phase.
Both boric acid daughter crystals in Figure 4 (H3BO3 and D3BO3) have the same B-isotope composition: 11B is 91.9% and 8.1% 10B.

Discussion

We report here, for the first time, unusual boric acid daughter crystals with extremely high 11B and high deuterium content at the % level. Both findings underline the author’s view that, for some pegmatites, a significant part of the volatiles and rare elements comes via supercritical fluids from the, in part, deep mantle of the Earth (Thomas and Rericha, 2024). Furthermore, we demonstrate that B-isotopes can be determined using Raman spectroscopy. That provides an opportunity to directly and non-destructively explore B-isotope fractionation in mineral-forming fluids, because the boric acid daughter minerals in primary inclusions represent the isotope composition of this solution (see Roedder, 1984).

Acknowledgment

We thank in memory Prof. Ludwig Baumann (1929-2008), of the Mining Academy Freiberg, for the provision of the sample from the Island of Elba.

References

  1. Rösler HJ, Lange H (1975) Geochemische Leipzig. Pg: 675.
  2. Hösel G (1994) Das Zinnerz-Lagerstättengebiet Ehrenfriedersdorf/Erzgebirge. Pg: 195.
  3. Thomas R, Förster H-J, Heinrich W (2003) The behaviour of boron in a peraluminous granite-pegmatite system and associated hydrothermal solutions: a melt and fluid- inclusion study. Contrib Mineral Petrol. 144: 457-472.
  4. Thomas R, Rericha A (2024) Extreme element enrichment, according to the Lorenzian distribution at the transition of supercritical to critical and under-critical melt or Geol Earth Mar Sci. 6: 1-6.
  5. Thomas R, Davidson P, Hahn A (2008) Ramanite-(Cs) and ramanite-(Rb): New cesium and rubidium pentaborate tetrahydrate minerals identified with Raman American Mineralogist. 93: 1034-1042.
  6. Thomas R (2025) Behavior of deuterium on boric acid: Raman spectrometric measurements: Preliminary Geol Earth Mar Sci. 7(7): 1-4.
  7. Roedder E (1984) Fluid Reviews in mineralogy. 12.
  8. Gmelin L (1954) Gmelins Handbuch der anorganischen Chemie: Bor (Ergänzungsband). Verlag Chemie, Weinheim. Pg: 253.
  9. Krishnan K (1963) The Raman spectrum of boric acid. Proceedings of the Indian Academy of Sciences, Section 57: 103-108.

Economic Shockwaves and Extremist Pathways: A Dual-Perspective Analysis of the 2025 Trade War’s Psychological Impact

DOI: 10.31038/PSYJ.2025773

Abstract

Trade wars, though driven by economic objectives, had repercussions extending beyond the economy into social and political spheres. Using a qualitative research design, this study examines the connection between the 2025 trade war and the potential rise of violent extremism by interviewing two key groups: former terrorist offenders, who provide insider perspectives, and terrorism analysts, who offer outsider viewpoints on extremist groups. The findings reveal that contemporary extremists can be categorized by ideology, scope, generational cohort, and behavioral patterns. The study further highlights how global economic instability, which leads to local crises, can exacerbate extremism and criminal behavior, particularly within vulnerable communities. This study identifies three classifications of extremists based on their responses to economic crises: “deradicalized”, “exploiters”, and “vulnerable”.

Keywords

2025 Trade war, Economic crises, Extremism, Radicalism, Terrorism

Introduction

In 2025, the United States, under Donald Trump’s presidency, escalated trade tensions by imposing high tariffs on goods imported from major economies such as the European Union (EU), China, and several ASEAN countries [1]. While these protectionist policies aimed to bolster domestic industries, they inadvertently disrupted the global economy. Simultaneously, a surge in extremist activities worldwide sparked concerns that such economic measures might be fueling the spread of radical ideologies. The Trump administration adopted an aggressive trade policy approach in 2025, implementing tariffs as high as 50% on European products while significantly increasing import taxes on goods from China and ASEAN countries. These measures were originally aimed to address trade imbalances and protect domestic industries. However, the abrupt policy shifts created substantial market instability, strained international relations, and triggered retaliatory measures from affected nations. For instance, the EU considered imposing counter-tariffs targeting U.S. technology firms, while ASEAN nations sought to mitigate the economic impact by strengthening trade partnerships with China and members of the Gulf Cooperation Council [2]. The imposition of tariffs significantly disrupted global supply chains, leading to higher production costs and subsequent price increases for consumers. While U.S. consumer confidence showed modest improvement following the trade truce with China, broader economic uncertainty persisted. Internationally, economies such as Germany faced potential GDP contractions, while several African nations revised their growth forecasts downward due to tariff-related instability. These economic pressures exacerbated social tensions, creating conditions that extremist groups exploited to capitalize on public discontent [3,4].

Historical precedents demonstrate that economic hardships can fuel extremist ideologies. The economic fallout from the 2025 trade war appears to be replicating this pattern. In the United States, the Department of Homeland Security’s Homeland Threat Assessment 2025 emphasized the ongoing threat posed by domestic violent extremists, many of whom were motivated by anti-government sentiment and conspiracy theories [5]. Globally, regions experiencing economic downturns saw a resurgence of radical groups capitalizing on widespread public discontent, a pattern that, while complex, is supported by various studies. This is evident in the rise of Pentecostal affiliation and political representation in Brazil [6], the growth of radical nationalism in Finland amid economic uncertainty [7], and the “Age of Discontent” framework, which argues that economic crises trigger cultural discontent and fuel the rise of populism and the radical right across several countries [8]. The trade war’s transnational impacts have been particularly evident. In Southeast Asia, ASEAN nations grappling with economic challenges stemming from U.S. tariffs have pursued alternative alliances and trade agreements. These geopolitical realignments not only altered regional power dynamics but also created opportunities for extremist groups to exploit perceptions of Western economic aggression. Similarly, in the Middle East, economic destabilization caused by U.S. tariffs and declining foreign investment contributed to the revival of groups like the Islamic State, which strategically leveraged the resulting chaos to recruit members and expand their influence [9].

While empirical evidence on the direct impact of trade wars on extremism remains limited, economic crises are known to significantly influence political extremism and terrorism. Historical patterns demonstrate that economic downturns frequently correlate with increased support for far-right and anti-establishment movements. This phenomenon was evident in Europe during both the 1930s Great Depression and the recent global financial crisis. Supporting this observation, a longitudinal study across 23 EU countries (1995-2012) revealed that declining GDP and rising unemployment rates consistently corresponded with growing electoral support for extremist parties, particularly far-left groups [10]. However, the relationship between economic hardship and extremism demonstrates significant complexity. In the U.S. context, Republican donors residing in foreclosure-affected areas showed reduced support for Tea Party candidates during the housing crisis [11]. On the other hand, research on Russian terrorism reveals that economic crises may produce contradictory effects on extremist activities: while economic distress can fuel public anger and potentially increase terrorist motivations, it may simultaneously constrain operational capabilities by limiting available resources [12]. These findings collectively suggest that the nexus between economic crises and political extremism is context-dependent, with outcomes varying according to specific circumstances. This study seeks to examine the intricate relationship between the 2025 trade war and the potential resurgence of violent extremism, as there is currently no research on this connection, incorporating viewpoints from both extremist networks and external sources. This will constitute the novelty of this study. Through in-depth interviews with two key stakeholder groups—former terrorist offenders (providing insider perspectives) and counterterrorism experts (offering external analyses), this study examines whether the 2025 US trade war’s economic disruptions may catalyze extremist violence. By elucidating the potential correlation between trade-induced economic shocks and extremist escalation, this study hopes to contribute in the development of mitigation strategies during periods of global economic and geopolitical instability.

Trade Wars

Definition of a Trade War

Trade wars are economic conflicts where countries impose retaliatory tariffs or trade restrictions to protect domestic industries or address trade imbalances [13,14]. These conflicts can arise from various factors, including uneven trade benefits, technological rivalries, and protectionist policies. The US-China trade war demonstrates such conflicts, with the US seeing China’s growth as a threat to its trade supremacy [15]. Trade wars can significantly impact global trade, economic growth, and international relations. The dynamic process of trade wars involves gradual tariff rises by one country, eventually prompting retaliation from the affected nations [16]. Depending on market characteristics, retaliation may lead to liberalisation or escalate into a full-scale trade war. Economist Douglas A. Irwin’s definition of trade war is a situation in which countries attempt to damage each other’s economy, usually through the tariff’s imposition or quota restrictions. It often lead to economic inefficiencies and increased tensions between nations [17]. Trade wars emerge as a direct consequence of protectionist economic policies designed to shield domestic industries through import restrictions. These measures, which include tariffs, import quotas, and regulatory barriers, fundamentally alter global economic dynamics by creating uncertainty that affects business investment patterns, disrupts global value chains, and distorts market expectations.

According to Xu (2024), protectionist interventions not only impede international trade flows but also elevate production costs and generate inflationary pressures across economies. The Sino US trade war, initiated amid economic tensions and mutual allegations of unfair trade practices, has significantly impacted strategic industries and constrained international investment flows [18]. The resulting global economic uncertainty has transmitted through financial markets, affecting both advanced and emerging economies [19]. Although current protectionist measures have demonstrated limited economic disruption to date, potential escalation poses substantial risks to global growth prospects and the Euro area [20]. This protectionism induced uncertainty adversely affects economic sentiment and potentially undermines long term market confidence. Empirical evidence from microeconomic firm data and macroeconomic analyses confirms that heightened trade policy uncertainty consistently suppresses corporate investment activity [21].

Historical Overview of Trade Wars

1. The Anglo-Dutch Trade Wars (17th Century). One of the earliest examples of a trade war occurred between England and the Dutch Republic in the 17th century. These conflicts involved both military and economic rivalry, including naval battles and commercial competition. In 1651, England passed the Navigation Acts, which restricted the use of foreign ships for trade between England and its colonies. This legislation aimed to weaken Dutch maritime dominance and ultimately led to a series of naval conflicts known as the Anglo-Dutch Wars. The outcome of these trade wars helped England establish itself as a dominant maritime and commercial power for centuries to come [22].

2. The Smoot-Hawley Tariff Act (1930). One of the most infamous trade wars in modern history was triggered by the Smoot-Hawley Tariff Act during the Great Depression. Passed by the U.S. Congress in 1930, the act imposed steep tariffs on over 20,000 imported goods. In retaliation, many countries raised their own tariffs, leading to a sharp decline in global trade. As a result, world trade plummeted by an estimated 65% between 1929 and 1934, exacerbating the global economic downturn [23].

3. The Chicken War (1960s). In the early 1960s, a trade dispute known as the “Chicken War” erupted between the U.S. and the European Economic Community (EEC) over tariffs on American poultry exports. After the EEC imposed protective tariffs, the U.S. retaliated by levying duties on European imports, most notably a 25% tariff on light trucks, including the popular Volkswagen Type 2 van. This measure had lasting consequences, in which the light truck tariff, which remains in effect as of the 2020s, has profoundly influenced the structure of the U.S. automobile industry for decades [24].

4. U.S.-China Trade War (2018–2020). The most prominent and widely documented trade war in recent history began in 2018 under the Trump administration, as tensions escalated between the United States and China. The U.S. accused China of engaging in unfair trade practices, including intellectual property theft and forcing technology transfers from foreign firms. In retaliation, the U.S. imposed tariffs on hundreds of billions of dollars’ worth of Chinese imports, prompting China to respond with counter-tariffs on American goods. This trade conflict had far-reaching consequences: it disrupted global supply chains, increased costs for manufacturers and consumers, and amplified economic uncertainty worldwide [25]. Additionally, it sparked a reassessment of global trade dependencies and contributed to a resurgence of economic nationalism across multiple countries.

Consequences of Trade Wars

Trade wars typically result in several key consequences: 1) higher consumer prices due to increased costs of imported goods, 2) supply chain disruptions, reducing efficiency and eroding competitiveness, 3) retaliatory measures from trading partners, escalating international tensions, and 4) adverse effects on global economic growth, particularly in interconnected sectors such as technology, agriculture, and automotive industries. According to the International Monetary Fund [26], the trade tensions and tariffs imposed between 2018 and 2019 slowed global economic growth, ultimately reducing world GDP by approximately 0.8% by 2020.

1. Disruption of Global Supply Chains. One of the primary mechanisms through which trade wars trigger economic crises is by disrupting global supply chains. In today’s interconnected economy, production processes often span multiple countries before final assembly. Tariffs raise the cost of intermediate goods, increasing production costs and reducing operational efficiency. During the U.S.-China trade war (2018–2020), for instance, U.S. manufacturers faced higher input costs due to tariffs on Chinese components, while Chinese exporters experienced reduced demand for their goods. Sectors with complex supply chains, such as automotive and electronics, were particularly vulnerable. A Federal Reserve study found that U.S. tariffs led to significant cost increases for domestic manufacturers and a measurable decline in industrial output [27]. Long-term consequences included widespread corporate uncertainty. Many firms delayed investments, restructured operations, or relocated production, often at substantial expense, to mitigate political and trade risks. This reconfiguration of supply chains further strained global economic stability.

2. Consumer Price Inflation and Reduced Purchasing Power. Tariffs function as a tax on imported goods, typically leading to higher consumer prices. Research by Amiti et al. [28] revealed that during the 2018-2019 U.S.-China trade conflict, American consumers and firms absorbed most of the additional costs from tariffs. These price increases reduced household purchasing power, which is crucial for maintaining GDP growth. When consumers have less to spend, overall economic demand weakens, business revenues decline, layoffs often follow, and economic growth slows. Prolonged trade conflicts may even trigger stagflation, which is a dangerous combination of rising prices and economic stagnation that, while rare, can cause severe damage. Multiple studies have examined the economic consequences of the U.S.-China trade war and potential broader global trade conflicts. Simulation results indicate that in a scenario of widespread global trade tensions, world GDP could decline by up to 1.96% with global trade volumes falling by 17% over the medium term [29]. The immediate impact of the U.S.-China dispute alone reduced GDP by 0.1% in the United States and 0.2% in China. The long-term effects appear more substantial, with potential losses reaching 1.6% for the U.S. and 2.5% for China, primarily due to reduced capital investment and diminished technological collaboration between the two nations [30]. Both countries experienced decreased energy demand and slower economic growth, which could further disrupt global energy markets [31]. While some nations may benefit from trade diversion effects, the overall impact on the global economy tends to be negative [32]. The conflict altered relative prices, disrupting established production networks and shifting comparative advantages in key sectors including transportation, electronics, and machinery.

3. Investor Uncertainty and Capital Flight. Trade wars generate significant policy uncertainty that undermines investor confidence. When trade policies become unpredictable, businesses typically delay decisions regarding expansion, innovation, and workforce growth. This cautious “wait-and-see” approach reduces aggregate investment and slows productivity growth [33]. The financial repercussions extend further as international investors may divest from nations engaged in trade conflicts, particularly those exhibiting economic vulnerability or political instability. Such capital outflows can trigger currency depreciation, increase borrowing costs, and potentially spark financial crises—especially in developing economies dependent on foreign investment.

4. Vulnerability of Emerging Markets. Emerging markets face heightened vulnerability during trade wars. These economies typically depend on exports for growth and require imports for critical industrial inputs. When major economic powers like the U.S. and China engage in trade conflicts, the ripple effects are global. Nations across Africa, Southeast Asia, and Latin America frequently experience reduced demand for their exports, volatile capital flows, and currency depreciation. These combined factors significantly elevate the risk of economic crises [34].

5. Poverty. Trade wars may impact poverty levels in developing countries through complex and indirect mechanisms. While trade expansion generally promotes economic growth, its benefits are often unevenly distributed across societal groups [35]. Trade conflicts influence poverty through multiple channels: (1) price volatility for essential goods, (2) labor market disruptions, (3) reduced government fiscal capacity, (4) heightened economic uncertainty, and (5) constrained GDP growth [36]. The ultimate poverty effects depend on three key factors: the severity of market disruptions, institutional capacity for risk mitigation, and labor demand elasticity. Particular attention must be paid to vulnerable populations, including women, rural communities, informal sector workers, and other marginalized groups [37].

Extremism

Extremism represents a multifaceted threat to both societal cohesion and fundamental rights [38]. Defined by the use of coercive violence to impose ideological or belief systems [39], its manifestations challenge common assumptions—particularly regarding religious extremism’s prevalence, which stems from complex interplays between individual psychology and communal dynamics [40]. From a psychological perspective, extremism is viewed as a form of deviant behavior that arises when there is an imbalance in motivation, where one need becomes so dominant that it overrides other needs and behavioral norms [41]. To address violent extremism requires identifying the specific needs or motivations that contribute to it and recognizing the role of external agents influencing or managing the difficulty level in carrying out extremist activities [42].

Research suggests that extremism is motivated by several psychological factors. According to significance quest theory, there are three main causes: a strong need to feel important or meaningful, a belief system that justifies the use of violence, and support from others with the same views [43]. Relative deprivation – the feeling of being treated unfairly or having less than others – is identified as an important factor that helps to explain various forms of violent extremism. This includes actions to change or protect existing social or political systems [44]. Extremism can manifest in both destructive forms (such as terrorism) and constructive forms (such as scientific breakthroughs). It can influence different parts of culture as well as individual decision-making. Understanding the psychological factors that lead to extremism is important to develop effective interventions to reduce dangerous extremist behaviors and redirect them to more constructive directions. These psychological insights offer a clear framework for studying and responding to different forms of extremism in different cultural and social settings.

Methods

Design

This study employed a qualitative research design to examine the relationship between the 2025 trade war and violent extremism. The qualitative technique was employed to gather extensive information regarding the relationship between factors. Due to various challenges in terrorism research, including confidentiality concerns and skepticism from both authorities and terrorist perpetrator [45,46], a qualitative methodology is more suitable for investigating the connection between the 2025 trade war and violent extremism.

Participants

This study involved ten deradicalized Indonesian terrorist offenders, a foreign (American) terrorist suspect, and eleven analysts/experts on terrorism (Table 1). Their ages ranged from 30 to 75 years. The terrorist offenders faced charges that included the Bali bombing, robbery, obstruction of justice, financing terrorism, involvement in worldwide terrorist networks, espionage, recruitment, and military training for terrorism. They were affiliated with militant organizations such as Jamaah Islamiyah/JI/Al Qaeda, ISIS, and Hezbollah. The eleven experts comprised forensic psychologists/terrorist profilers, senior officers from the Special Task Force Anti-Terrorism/Detachment 88 of the National Police (Densus 88), and several American, Indonesian, Malaysian, and Singaporean government think tanks (security consultants and advisors working for anti-terrorism agencies and various ministries), all of whom possess esteemed credentials.

Table 1: Participants of this study.

Perspective

Initial Sex (M/F) Age Field of expertise/ Case

Nationality/Affiliation

Outsider (experts/)


ST

M

45

Intelligence Indonesia

N

M

62

Economics Indonesia

PI

M

63

International relations, military, and defence Indonesia

GI

M

55

Politics and religion studies Indonesia

R

M

44

Legal and human rights Indonesia

IS

M

58

Law and gender studies Indonesia

MS

M

41

Middle East Studies USA

KP

F

51

Psychology Indonesia

BS

M

75

Military and intelligence Singapore

DT

F

54

Journalism, gender, and human rights Indonesia

AA

M

47

Religious studies Malaysia
 
Insider (former terrorist offenders/ suspects in extremist network)

AN

M

48

Terrorist recruitment and training JI

AT

M

45

Obstruction of justice ISIS

AI

M

48

Bombing JI

AD

F

23

Foreign fighting in Syria ISIS

TA

F

32

Terrorism financing ISIS

TS

M

49

Military training/camp JI

GL

M

32

Terrorism financing ISIS

WT

M

53

Terrorism financing JI

MI

M

45

Robbery JI

JI

M

61

Hiding information JI

SM

M

41

Espionage (foreign fighting in Iraq) Hezbollah

The study participants were selected through purposive sampling. To mitigate bias in purposive sampling, we initially defined the experts in this study as those possessing over ten years of experience in economics, social sciences, and/or counterterrorism; whereas the former offenders/suspects as those who were already deradicalized and whose names were recommended/referenced by counter-terrorism agencies/organizations (e.g., BNPT, Densus 88, the Ministry of Religious Affairs, and others). Secondly, we utilized inter-rater assessment in coding, categorizing, and interpreting the data acquired from participant interviews.

Procedure and Materials

A review of participant names, initial outreach, and communication with potential participants was conducted, followed by organized interviews with individuals who consented to participate in this study. Before the interviews, participants who agreed to take part in the study provided verbal consent to be involved. Interviews were conducted in May and June 2025 by the principal researcher of this study in Indonesia and the United States. Each participant engaged in a single interview session lasting approximately 30 to 40 minutes. Interviews were conducted in Bahasa Indonesia or English, with the researcher recording responses manually as participants opted against digital recording. Prior to concluding each interview, the researcher verified the written notes with the participant for accuracy to prevent misunderstanding and bias.

Analysis

The participants’ answers were compiled in a table for qualitative analysis. This enabled researchers to identify key similar concepts. The researchers subsequently deliberated on the participants’ replies and coding to ensure inter-rater agreement. They subsequently analysed the data using an inductive approach to identify a general pattern.

Results and Discussion

Extremists’ Perspectives on the 2025 Trade War

The findings of this study suggest that up-to-date extremists can be classified based on their scope, gender, ideology, hierarchical position within terrorist organisations, role, occupation, motivations for joining terrorist groups, generational cohort, and behavioural changes (Table 2). Extremists can be categorised as female or male, leaders or non-leaders, entrepreneurs or labourers, economically or non-economically oriented, religion- or non-religion-based, non-deradicalized or deradicalized, and active or passive. Regarding scope, there exist both local/home-grown and global extremists. Generational classifications include non-Gen Z individuals, specifically Baby Boomers (born 1946–1964), Generation X (born 1965–1980), and Millennials (born 1981–1996), as well as Gen Z or younger (born 1997 or later). The participants emphasise the Gen Z and younger cohort to anticipate the post-Artificial Intelligence (AI) age, as Gen Z is seen as a ‘cyber/digital generation’, fundamentally differing from preceding generations in many aspects of life. Although previous studies have recommended many classifications of terrorists or extremists, the participants of this study advocate for more simplified categories for pragmatic investigative objectives following the disbandment of Jamaah Islamiyah (JI) and the ‘zero-attack’ phenomenon.

Table 2: Classifications of contemporary extremists.

Category

Type

Scope Home-ground/local vs global
Gender Female vs Male
Hierarchy in terrorist network High-ranked (e.g., leaders, commanders) vs lower-ranked (e.g., technicians, couriers)
Work Entrepreneurs vs non-businessmen/labourers
Ideology Religion vs non-religion based (e.g., separatism, socialism, communism)
Motives to join network Economic vs justice vs security vs social vs political vs adventure
Generation Gen Z vs others
Level of radicalism Low vs medium vs high
Change in behaviour Non-deradicalized vs deradicalized vs unstable
Role Active (i.e., recruiter, producer) vs passive

The findings demonstrate that local extremist networks possess a limited understanding of the 2025 trade war in comparison to their global counterparts. Furthermore, extremist leaders and businessmen possess a greater understanding of the 2025 trade war and its ramifications on the daily lives of individuals, in contrast to non-leaders and labourers. Interestingly, participants of this study explain that female extremists (umahat) lack comprehension of global trends and the conflict between nations (USA/allies and China/allies), in contrast to their male kins (husband, father, son). Moreover, Gen Z extremists comprehend global news, including the 2025 trade war and its ramifications, as they consistently engage with news and podcasts on various online.

“Terrorists might be either homegrown or global. The global ones know that big countries might use them as proxies, so they might know about trade conflicts and other global problems. They are well-informed and watch the news because they will utilize any chance they have to propagate their narratives. But the ones who are homegrown don’t know anything about trade wars or geopolitics.” (A political analyst and advisor).

“We, Gen Z, watch news and listen to podcasts on YouTube, Twitter, and other sites. We know what’s going on in the world, including the 2025 Trade War and how it will affect our economy. We even keep up with many trends and know that there are numerous layoffs and campus dropouts in Indonesia because of the economic crisis.” (A former suspect/extremist).

“Our forensic clinical examination shows that these extremists and terrorists have serious problems in two parts of their brains: the ventromedial prefrontal cortex (vmPFC) and the dorsolateral prefrontal cortex (DLPFC). This means they don’t understand global issues like the 2025 trade war between the US and China. The DLPFC is a very important part of the brain that helps with memory, decision-making, emotion management, executive functioning, and behavior that is focused on goals. The DLPFC has something to do with violent behavior and terrorism. The vmPFC is a critically important part of the brain for social and emotional functioning, like empathy, controlling emotions, and moral competence. It regulates anxiety and fear. The vmPFC mixes cognitive and affective information, which includes human values.” (A forensic clinical psychologist)

“Don’t underestimate us, we follow the news. We know what’s going on in the world. We know about the trade war and other conflicts between the US and China, which affect Indonesia’s economy in the end.” (A bombing perpetrator).

“I doubt that extremists know about this thing (trade war). Their paradigm is different unless the great powers (USA and China) attack Muslim states.” (A senior military and intelligence advisor for several governments).

“They know about the 2025 trade war because their groups have a Foreign Affairs division, meaning they always monitor developments that occur abroad, including the trade war between China and America. So, they study things like this, not only local politics but also global politics. I remember when I interviewed one of the leaders of JI, he said that his division monitors global political developments and with whom they must cooperate.” (A senior journalist and analyst for governments).

The Expected Relationship Between the 2025 Trade War and the Rise of Extremism

The findings in this study show that participants split in opinions about the impact of trade war to the rise of extremism. Most participants argue that global economic challenges resulting in crises may increase the rise of extremism and criminal behaviour, especially to at-risk communities or individuals. Many of them refer to pull and push factors in criminal studies, indicating that economic or financial crises can precipitate various societal issues. They elucidated that economic difficulties may serve as catalysts or supporting factors, among other variables such as socioeconomic disparity, injustice, political instability, and so forth, in the emergence of extremism. Nevertheless, a small contingent of four individuals argues that economic issues are irrelevant to extremism, asserting that ideology is the only driver of such behaviour. These participants were former leaders or high-ranking members of JI (Table 3).

Table 3: Participants’ opinions on economic crises’ impact to the rise of extremism.

Insider (former terrorist offenders/suspects in extremist network)

Outsider (experts/analysts)

Initial and rank

Statements Agreement that trade war can lead to extremism Initial Statements

Agreement that trade war can lead to extremism

AN (JI, high-ranked) “No, nothing to do with that. Because our actions are based on ideology.”

X

N

“It is agreed in many theories that economic inequality can lead to criminality.”

√

AT (ISIS, high-ranked) “Yes, it can, therefore it is used in violent extremist narratives.”

√

PI

“Economic hardships can stimulate the rise of extremism, because vulnerable people in such situation will go to two things: gambling or extremism.”

√

AI (JI, high-ranked) “For us, economic issues don’t affect us. But for vulnerable people, economic difficulties may increase extreme thoughts.”

√

GI

“Economic troubles can be a catalyst in the increase of extremism.”

√

AD (ISIS, lower-ranked) “Economic problems can lead to violent extremism, yet through a very long process.”

√

R

“Yes, because economic discrepancy is one of the push factors in extremism and terrorism.”

√

TA (ISIS, lower-ranked) “Yes, economic grievance can be a trigger to make someone extreme in mind.”

√

IS

“No, economic troubles don’t contribute to extremism, because the extremists witness that everyone also suffers, not only their network/ fellows. We all are suffering.”

X

TS (JI, high-ranked) “For sure, yes, it can. Just like what happened in Poso.”

√

MS

“Yes, it can lead to extremism. Just look at Yemen.”

√

GL (ISIS, high-ranked) “It can, because economic troubles can increase criminal activities.”

√

KP

“Economic factors can increase extremism, but not directly.”

√

WT (JI, high-ranked) “It can but economy is not the only factor.”

√

BS

“Economic hardships due to the trade war can enhance existing or create new grievances, hence increase extremism.”

√

MI (JI, high-ranked) “There is a possibility that trade war between USA and China and other countries will cause global economic crises, and lead to the rise of extremism everywhere.”

√

DT

“Extremists will do the acts of terror when they have monetary resources, regardless the circumstances.”

X

JI (JI, high-ranked) “No, economic issues have nothing to do with us. We act based on ideology.”

X

AA

“Global economic crises because of the 2025 trade war between the great powers can be used by terrorists and extremists to recruit more people into extremist groups.”

√

SM (Hezbollah, sympathiser) “Economic difficulties for sure can increase the level of extremism in people.”

√

ST

“Yes, it can, that’s why economic crises is effectively used by them for their propaganda to recruit more people.”

√

The present findings reveal a divergence in participant perspectives regarding the potential impact of the 2025 trade war on extremism. A majority of participants posit that global economic instability may exacerbate extremism and criminal behavior, particularly among vulnerable populations. Drawing upon criminological frameworks, respondents highlighted how economic crises may function as both push and pull factors, interacting with other psychosocial variables—including socioeconomic disparities, systemic injustice, and political instability—to facilitate radicalization. Notably, a minority subset (n=4) of former Jemaah Islamiyah (JI) leaders and high-ranking members maintained that economic factors bear no significant relationship to extremism, asserting ideological commitment as the sole determinant of such behavior (see Table 3). This dissenting perspective underscores the ongoing theoretical debate regarding the relative weights of material deprivation versus ideological conviction in radicalization processes.

“People in underdeveloped regions who are still struggling, poor, and starving are more likely to commit terrorist attacks and become radicalized. For example, Poso. That’s the fact. It’s not easy to get people to do violent things while their tummies are full.” (A high-ranked JI member).

“Everywhere, it has become a premise that the greater the socioeconomic inequality, the higher the crime rate.” (A senior economic advisor of the Indonesian government.

“We are really offended when our acts are linked to money issues. Not all poor individuals in developing nations become terrorists. Our acts were based on our beliefs and ideology.” (A bombing perpetrator, former JI member).

“Trade wars and economic crises cannot turn individuals into extremists, but tensions between India and Pakistan can, due to India’s attacks against Muslims in Pakistan. There is a growing argument right now among Afghanistan ex-combatants over how to get to Pakistan from Indonesia to help our brothers and sisters there.” (A former leader of JI).

“Economic crises can turn people to be extreme in mind. Financial issues are not the main driver, but can increase extremism – indirectly maybe, along with other issues such as injustice, discrepancy, and other grievances.” (A senior JI member).

“Economic crises can lead to the rise of extremism as these can enhance existing or create new grievances.” (A senior military and intelligence advisor for several governments).

“The worse the economy in a country, the higher the extremism in its people. When people have nothing to lose – poor and starving, it’s easier to provoke them and escalate extremism in them. Just look at Yemen.” (An American analyst).

This study reveals a typology of psychological responses to economic crises among individuals with extremist affiliations. The findings demonstrate three distinct patterns of reaction and adaptation. First, there are individuals who have undergone significant belief system modification, having disengaged from violence. These individuals exhibit marked affective distress when confronted with economic crises, including inflation, rising prices, increased poverty, and heightened taxation. Their distress extends beyond personal circumstances to encompass broader societal impacts, and they maintain a determined commitment to peace advocacy regardless of external conditions.

In contrast, the study identifies a second category of extremist actors who occupy leadership or senior positions within their organizations and display high levels of radicalization. These “exploiters”-typed extremists individuals strategically exploit economic difficulties, turmoil, and chaos to advance their ideological objectives. They actively disseminate propaganda and recruit new members by framing economic crises as divine punishment for societies that fail to adhere to their prescribed religious practices. This exploitative behavior reflects sophisticated cognitive framing techniques and deliberate manipulation of in-group/out-group dynamics.

A third, more passive group emerges from the findings – individuals who are ‘muted’ members on the periphery of extremist networks while experiencing significant economic hardship. These members demonstrate increased susceptibility to radicalization during periods of economic distress, though they typically refrain from active participation in organizational activities. Their vulnerability appears rooted in the intersection of material deprivation and pre-existing network affiliations.

The study’s typological framework contributes to our understanding of how economic crises function as psychological stressors that interact differentially with individuals’ positions within extremist hierarchies and their stages of radicalization. The findings suggest that economic instability does not produce uniform effects across extremist populations, but rather activates distinct psychological and behavioral patterns depending on individuals’ organizational roles, belief systems, and personal circumstances. Thus, the study has identified three classifications of extremists according to their reactions to economic crises: 1) disengaged from violence/’deradicalized’ individuals who persistently promote peace, 2) ‘exploiters’ who use economic challenges as a means to disseminate extremist narratives and recruit more followers, and 3) ‘vulnerable’ silent individuals who may adopt more radical ideologies in response to economic hardships.

“These economic issues are exploited by recruiters to spread their ideology. They argue that the crises happen because the government is secular or not applying certain religious practices across many aspects.” (A high-ranked JI member).

“Historically proven, economic crises can cause discontentment and anger against authorities which can lead to resistance, fighting, and expressions of dissatisfaction against governments. The extremists use the issue of economic crises to blame the small group of minorities, the top 10%, the capitalists who own all the land and resources, and to promote hate-filled narratives or propaganda to get more people to join them.” (A scholar of Islamic studies, high-ranked counselor to governments).

“High prices, low purchasing power of the people, and various manifestations of economic crises cause two things in vulnerable communities: 1) online gambling due to frustration, or 2) extremism as a means to transcend existence in this world and go to the afterlife.” (An eminent professor in International Relations, Military, and Defense).

“Economic crises can cause someone to become extreme, but this is a very long process. Economic motives are not the only ones; they interact with other factors that can eventually cause people to become extreme. I am one example.” (A young former ISIS member).

Urgent Policy Measures Needed to Mitigate Risks During the 2025 Trade War

The findings of this study reveal several threats that governments must confront following the 2025 trade war, based on perspectives from both internal and external extremist groups. Former terrorist offenders/suspects and experts in various fields highlight current threats/risks, including significant economic and social disparities, political instability, poverty, and the escalation of tensions between India and Pakistan into a religious conflict (Table 4).

Table 4: Current threats according to participants.

Insider

(extremist networks)

Outsider

(experts)

Initial and rank

View on current risks Initial

View on current risks

AN (JI, high-ranked) The escalation of tensions between India and Pakistan into a religious conflict

N

Governments’ uncertainty in responding to the USA-China trade conflict
AT (ISIS, high-ranked) A new growing wave of violent extremism

PI

Poverty
AI (JI, high-ranked) Injustice, corruption, oppression and economic disparities

GI

Governments’ lack of empathy to their own people
AD (ISIS, lower-ranked) Economic, politic, and social instability

R

Social Inequality (grievance/hatred)
TA (ISIS, lower-ranked) People’s frustration and distrust in administrations of governments globally

IS

Radical narratives, such as those about India vs Pakistan war which are often linked to religion
TS (JI, high-ranked) Hunger and safety issues

MS

Economic inequality within and across nations
GL (ISIS, high-ranked) Poverty and welfare issues

KP

Crimes and terrorism
WT (JI, high-ranked) Disinformation, hoax, and dangerous radical narratives

BS

The consequences from the Israeli genocide against Palestinians
MI (JI, high-ranked) Inequality and perceived injustice in society

DT

The birth of new cells of extremist groups post-2025
JI (JI, high-ranked) Economic instability, poverty and sharp decline of people’s purchasing power

AA

Economic inequality, disinformation, and extremist narratives are thriving during economic crises and are used to manipulate public sentiment
SM (Hezbollah, sympathiser) Socio-economic discrepancies and injustice

ST

Recruitment of extremist groups

“The current threat, in my opinion as an economist, is the governments’ confusion and uncertainty in responding to BRICS versus the USA. This confusion stems from a lack of capacity.” (A senior economic advisor to the Indonesian government).

“The current threat to handle is that the fallout from the Israeli genocide against Palestinians has radicalized several Salafi groups. Although the violence has not yet happened, a new leader or coalition could trigger future jihadi attacks.” (A senior military and intelligence advisor for several governments).

“I think the current risks now are people’s frustration and distrust in their governments’ administrations. In many countries, governments have failed to win people’s hearts. They fail us. People around the world feel ignored and disrespected by their governments. Governments see their people as stupid, but actually they are not.” (A young former female ISIS member).

“Terrorism financing is now a real threat. Extremist narratives and propaganda on social media are often sponsored by terrorist groups. These groups frequently pay to spread extremist stories and propaganda online. Indonesians are generally kind and generous people, which is why these organizations collect money by tricking or manipulating ordinary citizens. They also utilize digital or cryptocurrency to transfer funds to locations like Syria.” (A forensic clinical psychologist).

This study found recommended government responses and strategies to address current threats, as proposed by former terrorist offenders and experts. These include good governance, poverty eradication, effective counternarratives and deradicalization programs, and improvements in education and healthcare systems (Table 5).

Table 5: Participants’ opinions on prompt improvement by governments globally.

Insider (former terrorist offenders/suspects in extremist network)

Outsider (experts/analysts)

Initial and rank

Strategies to Overcome Current Threats (Governments’ Areas for Improvement) Initial

Strategies to Overcome Current Threats (Governments’ Areas for Improvement)

AN (JI, high-ranked) Deradicalization and counter-narratives programs to vulnerable people

N

Educating people and focusing on strategic resources and commodities
AT (ISIS, high-ranked) Continue deradicalization and counternarrative programs, maintaining the level of defence and security, and eradicating corruption in governments’ administration

PI

Erasing poverty by: 1) eliminating corruption, 2) promoting socioeconomic equality, 3) enhancing welfare through the creation of employment opportunities, among other measures
AI (JI, high-ranked) Implementing good governance, reducing inequality, as well as performing effective deradicalization and counter-narratives against extremism

GI

Constructing positive narratives through various ways, such as legislation, politics and community empowerment, that cultivate empathy; and improve the education curriculum
AD (ISIS, lower-ranked) Strengthening all key sectors, including ending corruption, improving the quality, affordability, and accessibility of education, and enhancing healthcare

R

Countering radical narratives
TA (ISIS, lower-ranked) Demonstrating respect and empathy to people and addressing public frustrations, especially in education and healthcare

IS

Suppressing radical narratives and educating vulnerable communities
TS (JI, high-ranked) Enhancing societal safety as well as increasing employment opportunities to ensure that people can fulfil their basic needs

MS

Reducing economic disparities inside and across nations
GL (ISIS, high-ranked) Improving general welfare, especially for individuals vulnerable to radicalisation, offering employment to disengage individuals from violence, as well as maintaining deradicalization efforts

KP

Establishing a banking and non-banking framework that inhibits the financing of terrorists, alongside media counternarratives to mitigate extremism
WT (JI, high-ranked) Adopting a persuasive and inclusive approach and avoiding aggression and repression to people

BS

Ceasing the Israeli genocide against Palestinians
MI (JI, high-ranked) Implementing good governance which is full of integrity and transparency

DT

Monitoring to religious parties, new cells of extremist groups, and social media propaganda, and making effective programs to address extremism
JI (JI, high-ranked) Improving law enforcement, legal system, and economic opportunities

AA

Addressing economic inequality, countering extremist narratives, and monitoring emerging extremist group that may arise during times of economic turmoil
SM (Hezbollah, sympathiser Addressing socio-economic inequality

ST

Fixing governments’ communication which promote empathy and reduce tension

“Governments everywhere should adopt a persuasive and inclusive approach, like those successfully used with Jemaah Islamiyah in Indonesia, which led to its disbandment, and should reduce counterproductive actions such as aggression and repression toward people.” (A senior former member of JI).

“The state should enhance all sectors, including eradicating corruption, advancing education to make it more affordable and accessible to the populace, and enhancing healthcare. Avoid creating frustration among people because frustration can lead to turbulence, chaos, criminality, extremism, and terrorism.” (A young former female member of ISIS).

“The dissolution of JI does not mean the end, because there is potential for new cells to emerge from those who disagree with JI’s dissolution. There are also internal dynamics within JI post-dissolution that could lead to dissatisfaction and the emergence of new cells. Additionally, JI could change its name and strategy, and infiltrate government or non-government agencies to influence policy. Regarding ISIS, it’s crucial to monitor overseas instructions, as they are still consolidating and actively recruiting at this time.” (A senior journalist and analyst for governments).

Conclusion

While trade wars may appear politically advantageous in the short term, they typically incur significant economic costs. These include disruptions to global supply chains, increased consumer prices, erosion of investor confidence, and destabilization of developing markets. The 2025 U.S. trade war, though economically motivated, produced effects extending beyond financial systems into social and political domains. The resulting economic deterioration not only exacerbated international tensions but also created conditions conducive to the proliferation of extremist ideologies. Employing a qualitative research design, this study examines the complex relationship between the 2025 U.S. trade war and potential escalations in violent extremism, incorporating both internal (terrorist group) and external (analytical) perspectives. Through in-depth interviews with former terrorist offenders (insider perspectives) and counterterrorism experts (outsider perspectives), the research investigates whether the 2025 trade war may intensify violent extremism by creating favorable sociopolitical conditions for radicalization.”

The findings have revealed that current extremists are categorised based on their role, scope, ideology, hierarchical position within terrorist organisations, occupation, drives for joining terrorist groups, generational cohort, gender, and behavioural changes. A key revelation concerns the demonstrable secondary effects of the 2025 U.S. trade war on extremism dynamics. The economic disruptions disproportionately impacted vulnerable populations, creating identifiable psychosocial conditions that facilitated radicalization among at-risk communities and individuals. This economic shock appeared to operate as both a structural enabler and psychological accelerant for extremist mobilization. Particularly salient was the emergence of three distinct behavioral phenotypes in response to economic crises. The first group comprised disengaged/“deradicalized” individuals who actively promoted peaceful alternatives despite economic hardships, representing persistent anti-violence voices. In contrast, a second category of strategic actors – termed “exploiters” – systematically leveraged economic distress to amplify extremist narratives and recruitment efforts. Perhaps most concerning was the identification of a third, “vulnerable” silent cohort characterized by heightened vulnerability to radicalization when facing economic deprivation, suggesting a latent risk pool requiring targeted intervention.

The study’s findings yield important implications for evidence-based policymaking informed by psychological principles of radicalization. Drawing on first-hand accounts from former extremists and counterterrorism specialists, the research underscores how multidimensional interventions addressing both socioeconomic conditions and individual psychological vulnerabilities may effectively counter extremist recruitment. At the core of these recommendations lies the need for poverty alleviation programs that target the sense of relative deprivation known to fuel grievances, combined with counter-narrative campaigns that apply principles of cognitive dissonance to disrupt extremist messaging. The findings further highlight the psychological importance of governance reforms that address fundamental human needs for system justification and fairness, alongside improvements to education and healthcare systems that can foster secure attachments and hopeful future orientations. These policy priorities emerge as particularly crucial in light of the socioeconomic disruptions caused by the 2025 U.S. trade war, which appear to have created fertile ground for extremist narratives targeting vulnerable populations.

From a research perspective, the study reveals critical gaps in our quantitative understanding of how macroeconomic shocks interact with known psychological risk factors for radicalization. Future investigations employing longitudinal designs and multilevel modeling could help disentangle the complex relationships between trade-induced economic indicators, individual-level radicalization processes, and community-level transmission of extremist ideologies. Such research would benefit from incorporating both behavioral measures of extremist engagement and emerging neurocognitive markers of vulnerability to radicalization, potentially yielding more precise predictive models for preventive intervention. This integrated approach, combining psychological theory with economic policy analysis, offers a promising framework for developing more effective counter-extremism strategies that address both the structural conditions and individual pathways that facilitate radicalization.

References

  1. Reuters (2025) Trump’s trade whims strengthen EU’s hawkish camp.
  2. AP News (2025) ASEAN opens summit with Persian Gulf nations and China as US threatens tariffs.
  3. Axios (2025) Consumer sentiment jumps after U.S.-China trade truce.
  4. The Guardian (2025) IMF lifts UK growth forecast for 2025; markets welcome US delay to EU 50% tariffs – as it happened.
  5. Department of Homeland Security (2024) Homeland threat assessment 2025. U.S. Department of Homeland Security.
  6. Costa FJM, Junior AM,Rocha R (2019) Stop suffering! Economic downturns and pentecostal upsurge.
  7. Silvennoinen O (2016) But – Where do these people come from? (pp. 173–178)
  8. Rhodes-Purdy M, Navarre R,Utych S (2023) The age of discontent. Cambridge University Press.
  9. Control Risks (2025) Rising political violence.
  10. Doležalová J (2015) Economic crisis and growth in vote share for extreme left and extreme right parties. Review of Economic Perspectives 15: 269-290.
  11. Li Z (2023) When do campaign donors reject extremists? Evidence from the US foreclosure crisis. The Journal of Politics 85: 1548-1561.
  12. Omelicheva M,Webb C (2021) Economic crises and terrorism: Analyzing competing economic pressures on terrorism in Russia. Journal of Global Security Studies 6: 3.
  13. Adegboye FB, Odularu G,Matthew OA (2020) The US-China trade war: What is Africa’s gain? In G. Odularu, M. Hassan, & M. Babatunde (Eds.), Fostering Trade in Africa .153-170. Springer, Cham
  14. Batyrkanov BT,Kharlanov AS (2024) The impact of trade wars on the global economy: Analysis of the consequences of trade conflicts on the global market and economic growth of different countries in Post-Covid recovery. Economics and Entrepreneurship 9: 229-232.
  15. Mishra RK, Karthik M (2020) Understanding the US-China trade war: Causes, consequences and economic impact. Global Trade and Customs Journal 15: 580-591.
  16. Gould DM, Woodbridge GL (1993) Retaliation, liberalization, and trade wars: the political economy of nonstrategic trade policy.
  17. Irwin DA (2017) Clashing over commerce: A history of US trade policy. University of Chicago Press
  18. Xu J (2024) The impact of trade wars and protectionism on the global economy: A Sino-US perspective. Highlights in Business, Economics and Management 46: 203-208
  19. Yilmaz D (2020) From protectionism to trade wars: Their effects observed through financial markets. Yönetim ve Ekonomi Araştırmaları Dergisi 18: 1-19.
  20. Gunnella V,Quaglietti L (2019) The economic implications of rising protectionism: a euro area and global perspective. ECB Economic Bulletin. 3.
  21. Caldara D, Iacoviello M, Molligo P, Prestipino A, Raffo A (2019) The economic effects of trade policy uncertainty. International Finance Discussion Papers. 1-49.
  22. Israel J (1995) The Dutch Republic: Its rise, greatness, and fall, 1477–1806. Oxford University PressOxford
  23. Eichengreen B,Irwin DA (2010) The slide to protectionism in the great depression: Who succumbed and why? The Journal of Economic History 70: 871-897.
  24. Bown CP (2011) The WTO and antidumping in developing countries.
  25. Bown CP,Kolb M (2019) Trump’s trade war timeline: An up-to-date guide. Peterson Institute for International Economics.
  26. International Monetary Fund (2019) World economic outlook, October 2019: Global manufacturing downturn, rising trade barriers.
  27. Flaaen A,Pierce J (2019) Disentangling the effects of the 2018-2019 tariffs on a globally connected U.S. manufacturing sector. Finance and Economics Discussion Series.
  28. Amiti M, Redding S,Weinstein D (2019) The impact of the 2018 trade War on U.S. prices and welfare.
  29. Bekkers E,Teh R (2019) Potential economic effects of a global trade conflict.
  30. Tsutsumi M (2019) The economic consequences of the 2018 US-China trade conflict: A CGE simulation analysis.
  31. Xia Y, Kong Y, Ji Q,Zhang D (2019) Impacts of China-US trade conflicts on the energy sector. China Economic Review 58: 101360.
  32. Bekkers E,Schroeter S (2020) An economic analysis of the US-China trade conflict.
  33. Handley K,Limão N (2017) Policy uncertainty, trade, and welfare: Theory and evidence for China and the United States. American Economic Review 107: 2731–2783.
  34. World Bank (2020) Global economic prospects: Slow growth, policy challenges.
  35. Mamoon D (2015) How may international trade affect poverty in a developing country setup? The inequality channel. International Journal of Economics and Empirical Research (IJEER) 3: 230-244
  36. Winters LA (2020) Trade, trade policy and poverty: What are the links?
  37. Johns MB, Brenton P, Cali M, Hoppe M,Piermartini R (2015) The role of trade in ending poverty (No. 97607)
  38. Zinchenko YP (2014) Extremism from the perspective of a system approach. Psychology in Russia: State of the Art 7: 23–33
  39. Baqai, H (2011) Extremism and fundamentalism: Linkages to terrorism Pakistan’s perspective. International Journal of Humanities and Social Science 1: 242-248.
  40. Liebman CS (1983) Extremism as a religious norm. Journal for the Scientific Study of Religion 22: 75.
  41. Kruglanski AW,Moskalenko S (2024) Psychology of the Extreme. Routledge.
  42. Kruglanski AW, Jasko K, Chernikova M, Dugas M,Webber D (2017) To the fringe and back: Violent extremism and the psychology of deviance. American Psychologist 72: 217-230.
  43. Kruglanski A, Jasko K, Webber D, Chernikova M, Molinario E (2018) The making of violent extremists. Review of General Psychology 22: 107-120.
  44. Kunst JR, Obaidi M (2020) Understanding violent extremism in the 21st century: the (re)emerging role of relative deprivation. Current Opinion in Psychology 35: 55-59.[crossref]
  45. Bhui KS, Hicks MH, Lashley M,Jones E (2012) A public health approach to understanding and preventing violent radicalization. BMC Medicine 10: 16.[crossref]
  46. Shepherd J (2007) The rise and rise of terrorism studies.

Integrated Vocational Education for Maternal Care-Insights from an Empirical Study in Underserved China

DOI: 10.31038/PSYJ.2025771

Abstract

This commentary critically evaluates the empirical study An Empirical Study of Integration Models and Mechanisms for Maternity Care in Innovative Vocational Education Systems, which addresses maternal health disparities in underserved China through an integrated vocational training model. Using a mixed-methods design combining PLS-SEM and NVivo analysis, the study reveals both the promise and limitations of integrating simulation-based learning, structured supervision, and early clinical immersion. Key findings include significant improvements in patient satisfaction but no measurable impact on student engagement or maternal complications, highlighting systemic barriers to translating training into clinical outcomes. This commentary discusses the study’s methodological innovations, practical implications for vocational education reform and health policy, and identifies future research directions to enhance the model’s effectiveness.

Introduction: Background and Core Issues

Maternal health disparities persist in underserved regions of China, complication rates remain significantly higher than the national average [1]. A critical underlying factor is the fragmentation of vocational education for maternal care, characterized by three key pain points: (1) a disconnect between theoretical instruction and clinical practice, with delayed exposure to real-world scenarios; (2) fragmented simulation training, often limited to video observations rather than hands-on practice; and (3) inadequate structured supervision, leading to passive student engagement [2]. These gaps contribute to poor emergency response skills among graduates and inconsistent care delivery, exacerbating maternal health risks. Against this backdrop, the empirical study (hereafter referred to as the Study) aims to evaluate an integrated training model combining simulation-based learning, structured clinical supervision, and early clinical immersion. This commentary analyzes the Study’s contributions, limitations, and implications for addressing maternal care challenges in underserved settings.

Innovative Methodology: Mixed-Methods Design

The Study’s strength lies in its rigorous mixed-methods approach, which overcomes the limitations of single-method research:

Quantitative Analysis

Partial Least Squares Structural Equation Modeling (PLS-SEM) was used to analyze data from 300 participants (students, nurses, patients, instructors) across experimental (integrated training) and control (traditional training) groups. This allowed the assessment of causal relationships between constructs (e.g., Staff Training → Patient Satisfaction) and multi-group comparisons to identify intervention effects.

Qualitative Analysis

Thematic analysis using NVivo 14 was applied to 14 semi-structured interviews, exploring implementation barriers and stakeholder experiences. This provided contextual depth to explain quantitative findings.

Triangulation

Convergent validation of quantitative results (e.g., patient satisfaction improvements) with qualitative insights (e.g., staff communication quality) enhanced the credibility of conclusions.

This mixed-methods design is innovative in the Chinese vocational education context, as it links training inputs to both patient-centered outcomes and institutional implementation mechanisms (Luo, 2025).

Key Findings: Promise and Limitations

The Study’s findings reveal a nuanced picture of the integrated model’s effectiveness:

Quantitative Insights

The integrated training significantly predicted higher patient satisfaction (β = 0.863, R² = 0.743), aligning with Kolb’s Experiential Learning Theory. However, no significant relationships were found between student interaction and patient satisfaction, or between patient satisfaction and maternal complications. Critically, the Staff Training construct exhibited weak psychometric validity (Composite Reliability [CR] = 0.337; Average Variance Extracted [AVE] = 0.126), indicating fragmented implementation of training components.

Qualitative Insights

Interviews highlighted key barriers: inconsistent use of simulation tools (e.g., control group students only watched videos), unclear student roles in clinical settings (“We just stood back and watched; we never practiced ourselves”), and systemic constraints like emergency delays and staffing shortages. These insights explain why patient satisfaction improvements did not translate into reduced maternal complications—perceived care quality does not address structural gaps in healthcare delivery.

Together, these findings suggest that while integrated training enhances patient perceptions, it fails to improve clinical outcomes due to poor implementation fidelity and institutional readiness.

Practical and Policy Implications

The Study offers actionable insights for vocational education reform and health policy:

Vocational Education Reform

Standardize simulation training: Mandate high-fidelity simulation实操 with structured checklists to ensure consistent implementation.

Clarify student roles: Develop guidelines for student engagement in clinical care (e.g., assisting with routine tasks under supervision) to reduce role ambiguity.

Strengthen supervision: Allocate dedicated supervisory hours and implement real-time feedback mechanisms to enhance student learning.

Health Policy

Resource allocation: Prioritize funding for simulation equipment and staff training in underserved regions to address resource scarcity.

Cross-sector collaboration: Foster partnerships between education and health sectors to align training curricula with clinical needs (e.g., joint development of maternal care training standards).

Accreditation and audit: Include implementation fidelity metrics (e.g., simulation usage rates, supervision quality) in vocational college accreditation to ensure model adherence.

These measures can bridge the gap between training inputs and clinical outcomes, enhancing maternal care quality in underserved areas.

Limitations and Future Directions

The Study has several limitations that future research should address:

Construct Measurement

The Staff Training construct requires refinement (e.g., splitting into sub-dimensions like simulation quality and supervision intensity) to improve validity.

Outcome Measurement

Maternal complication data were self-reported; future studies should use electronic medical records (EMR) to obtain objective clinical outcomes (e.g., postpartum hemorrhage rates).

Generalizability

The single-institution sample limits external validity; multi-site randomized controlled trials (RCTs) are needed to test the model’s scalability.

Longitudinal Design

A longitudinal approach can track the long-term impact of integrated training on student competence and maternal health outcomes over time.

Addressing these limitations will strengthen the evidence base for integrated vocational education models in maternal care.

Conclusion

The Study provides valuable insights into the potential of integrated vocational education to improve maternal care in underserved China. While the model enhances patient satisfaction, its clinical impact is constrained by implementation gaps and systemic barriers. To realize its full potential, reforms must focus on standardizing training, clarifying student roles, and addressing structural healthcare deficits. Future research should build on these findings to develop more robust, context-adapted models that translate training into tangible improvements in maternal health outcomes. This commentary underscores the importance of rigorous mixed-methods research in evaluating vocational education interventions and the need for systemic collaboration between education and health sectors to advance maternal health equity.

References

  1. LI Y, Zhang Y, Yuan B, Wang H (2023) Analysis and thoughts on the settings of sub-campus of public hospitals directly under the National Health Commission of China. Chinese Journal of Hospital Administration, 399-403.
  2. Luo W (2025) An empirical study of integration models and mechanisms for maternity care in innovative vocational education systems.

The Virus and Sociology: A History of an Organic Relationship

DOI: 10.31038/AWHC.2025842

Abstract

The present paper is an attempt to study the hypothesis according to which the outbreak of viruses has triggered in-depth responses and research in the field of sociology. Such unprecedented interest aims at enabling the discipline to elaborate both its epistemological and methodological perspectives and therefore assert its DNA within the sphere of the so-called “hard sciences”, and more particularly that of biology. The outbreak of the Corona virus pandemics has undoubtedly disrupted people’s attitudes towards life, illness and death. In this context, sociology has to reconsider its views and stances towards the virus in order to provide an insightful understanding of such new crisis-related attitudes.

Keywords

Sociology, Virus, Organicism, Positivism, Pandemic crisis

Introduction

As a starting point, let us raise question of how sociology enables us to understand the meaning of a virus. In other words, how does sociology as an autonomous discipline contribute to thinking through and understanding virus?

Studying and dealing with Viruses is widely and traditionally believed to belong to the field of epidemiology. Any sociological attempt to embark in such a task will be a challenging and risky adventure. However, the health crisis, which is widely known as the macabre COVID-19 that has affected countries worldwide, has proved to raise great interest and appeal among scholars in sociology. A wide range of questions has been advanced and brought under study by sociologists in order to deal with issues related to prevention measures that can help combat or limit this fast spreading virus:

  • How to urge people to respect both social and physical distancing.
  • The various steps to take in order to reduce people’s interactions to their minimum and strict level.
  • Lockdown measures as a way to restrict communities’ mobility.
  • Obliging people to weak masks in public areas.

Within this health crisis context, due attention is also given to how people conceive of health, sickness and the idea of death. In fact, such interesting questions have to be handled from a sociological perspective. We have to admit that sociology is supposed to advance its findings about social mechanics during normal everyday life as well as during crises or urgent situations. Switching between such opposing contexts is so gratifying for the sociologist since it enables them to observe facts within a temporality they will be able to master. Urgent situations usually compel these scholars to make compromises and work under stressing circumstances since when one “knows he is to be hanged in a fortnight, it concentrates his mind wonderfully.” [1]

Urban Areas: A Hotspot for Viruses

Relationships, bonds and ties are thought of as organic as long as they present a certain degree of intricate complexity. The epistemological complexity stems not only from the city population density and its deeply rooted individualism but also from the complexity of its labor division. That is why these areas are the first to fell under the spell of globalization phenomena for the best and for the worst. When it comes to harmful and fast spreading viruses, cities are the first to be affected since they do not enjoy enough and adequate facilities and efficient rules and regulations. Nobody lays the blame on cities lacking adequate equipments to face such unpredictable outbreaks. Nobody attributes the cause of such effects to an uncontrolled globalization. Environment scientists point out, among other factors, the dominance of air transportation because of their speed. Thus, they overshadow or even eclipse the other modes of locomotion since they consider them time- consuming. Yet, one can’t deny the major role they contribute in slowing down the spread of air imported viruses such as COVID 19.

In the context of globalization, the spread of COVID 19 is accelerated because of the frequent recourse to air transportation as one of the favorite means of bringing people close to each other. Cities are also home for clustered economic activities as well as industrial districts that foster proxemics leading to an active and continuous spreading of the virus. The Italian case best illustrate such an uncontrolled propagation of the virus when the pandemic first broke out. Highly industrial and commercial areas, slaughterhouses, textile and garment factories and mass food services are the areas that are most exposed to the heaviest rates of contamination.

The unlimited greed of capitalism for a global city and for a huge available reserve army has pushed the city to assume roles it is well prepared to. It has to host an unqualified labor force usually living in ghettos and slums lacking proper sanitation and where viruses proliferate fast. Globalized capitalism has made of profit its main creed. Therefore, global cities’ ecosystems have undergone its destructive effects even if they stand as ramparts against viruses against which our immune system is not well equipped.

Rediscovering the benefits of the boundaries within a sovereign State Nation, protecting cities within the same national territory and restricting the flow of people and goods are among the major measures that most states took in order to control the spread of the virus. The implementation of such measures is a way to recognize the assets of sovereignty that both the global consensus and the different walks of liberals have denied so far. In other words, and to express it in sociological terminology related to the process of globalization, this context of health crisis has shown that the methodological nationalism has gained more ground over methodological cosmopolitism. Yet, if we base our assessment on the increasing number of contaminated people and the resulting panic, it will be evident to presume that governments are unable to control and contain the disease and therefore protect their citizens.

The Ambivalence of the State Response to the Global Health Crisis

When confronting uncertain and urgent situations, decision makers, standing for the dominant legitimate violence holder, usually rely on a security based approach to handle and deal with such crises: (community lockdown, compulsory masks and obligatory negative COVID 19 tests for travelers). Thus, if governments proceeded with their borders control, what was the cost to pay and what were the procedures to implement above all if the main lever is held by family owned business powers? Without focusing on cosmopolitism, this question is really worth exploring unless there is lack of data. The economic crisis following the health crisis is the worst that humanity went through. It is more likely that it has led to radical change and even to a departure from previous modes and paradigms.

Mass media have largely covered the pandemic and its subsequent effects. Yet, globalized capitalism is certainly endowed with enough resources leading to model of society. This new social configuration will be so challenging to the sociologist’s gaze. The hypothesis that a wave globalism is taking shape in a world largely controlled by the world of Finance/ Financial oligarchy disdaining peoples and having conflicting attitudes towards the Nation State. Permeated with a political and ideological note, the globalist doctrine strives to impose a new terminology and make it widely understood and accepted within academic spheres. That is to say, global governance aspires to place the notion of sovereignty at the heart of a hardline neoliberal framework expressed through symbols that ends up in a kind of a global city. Hence, the apostles of globalism clearly denigrate the principle of People’s Sovereignty, which is based on sovereignty by and for peoples.

The Health Crisis as a Total Social Fact

In overpopulated urban areas, domestic space has also been the focus of scholars, especially during the high pic periods of community lockdown. Large families living together in overcrowded shanties have certainly gone through hard times because of that deterioration in social relationships. The repercussions of such a hard and difficult situation can be summed up as follows:

An increase in the rate of urban domestic violence, children in distress, an increasing and chaotic feeling of apprehension about the future. In terms of skills and knowledge transmission, illiterate families have suffered the stress and the exhausting effects of distance learning.

Nevertheless, being locked down in a luxurious villa having different facilities such as a swimming pool and located in a gentrified neighborhood looks like spending an enjoyable holiday. This health crisis has clearly revealed the stark inequalities prevailing among the different walks of life in urban areas. Other level of segregation lies in the economic domain. As far as the private sector is concerned, employees were forced to non-paid holidays or even sacked. Both sexes were compelled to telecommuting. So professional life commitment tend to influence and overshadow intimate family life. For underground economy, substantial segments and groups, relying on resourcefulness have been considerably impoverished. The stakeholders involved were obsessed with this pandemic lest they should catch the virus and then contaminate their family members.

One of the other issues is related to paradigmatic considerations. That is, trying to establish an articulated link between the city, the health crisis and the process of globalization. The aim is to provide an insightful understanding of how fragile our common universe is. It is also a way to explain that our global society model is doomed to exhaustion because it is mainly based on the sacrosanct excessive human rights model. Instead, it should stand on a more pragmatic ground rather than relying on more ideological positions respecting Nature and maintaining an environmental balance. Commodification of wild animals living in jungles better illustrates human idiocy and their flagrant transgression of the natural order. It is admitted that bats are infected with viruses that belong to the family of RIBOVIRUSES known as “corona”. Their shape is similar to that of a crown. According to official reports and records, this virus appeared in China on December 8th, 2019. It is argued that this pandemic is so familiar among the family of bats, which plays a major role in its transmission. This scientific fact was proved by Shi ZHENGLI, a reputed Chinese scholar in virology at the Institute of virology in Wuhan (the starting point of the virus). He declared, “There are different bats and wild animal species. The unknown viruses that we have discovered stand only for the visible part of the iceberg. To protect human beings from the upcoming epidemic of infectious diseases, we should progress in research and have a deep insight into the nature of these unknown viruses that wild animals spread in nature. Therefore, we will be able to warn people in advance and incite them to take prevention measures. If we don’t study them thoroughly, we will be running the risk of suffering from further epidemics” [2]. The way people conceive of such creatures (a kind of hybrid ones with multiple virtues) living closely to them is a harbinger of a social and health cataclysm. Therefore, sociology will have to conduct more research with more findings on human animal nature and animal humanity. The perspective according to which such a task should be achieved should take into consideration the logic of the market as well as the healthcare chaos that can lead to a kind of incestuous relations between humans and animals. To sum up, commodification of animals, environmental balance disturbance and consumerism have considerably paved the way for the virus to cross the borders.

The Virus, Possible Lessons for Sociology

Our social world universe is so intricate and complex, especially when it suffers from a pandemic. Any attempt to approach it solely from the perspective based on human encroaching on animal territory will be oversimplifying and even incomplete. Instead, the CORONA virus should be dealt with according to a sociological perspective that can reflect and reveal human weaknesses and vulnerabilities. Our planet is continuously threatened by the irresponsible egoistic short-term actions of its inhabitants. Because of its omnipotence, The Corona virus, a kind of influenza that has not revealed all its secrets yet, can reach our unconsciousness and dominate our daily talks and interactions. It can also make us more worried about an uncertain future. In short, this unexpected intruder has broken out in the daily life of communities all over the world. It has acquired a global dimension through compulsory lockdowns and quarantines and the surprisingly high number of deaths it has caused.

Few observers and researchers were able to fully understand the initial scenario of the pandemic outbreak as we can infer from the parts included in a diagnosing prospective report. At the core of it lies the complexity that characterizes the practice of our “living together”. A situation that is so difficult to grasp as is the case for most of the conclusions delivered by the regularly established report of “the World in thirty years ‘time”. Such reports are one of the American central Intelligence Agency favorite activities. Empirically speaking, the virus is undoubtedly devastating since it causes both physical and psychological sufferings. It also provides regular signals about the unhealthy state of our societies via alerts that reflect the sense of life and History. The context of the pandemic as a morbid event has intensely contributed to our body and soul lockdown.

Quarantine, Lockdown or containment: macabre terms that have popped up out of the dictionary and that show how both our body and spirit have been got hold of. Discipline, manipulation and restricting people mobility by exposing them to containment areas are examples of what Michel Foucault called quarantine corollaries. Yet, the lesson to learn as previous experiences usually have shown is that the threat of a surprisingly unexpected virus is a reminder of an ontological and existential fragility. Broadly speaking, what does the virus mean?

In the next part, we will attempt to provide a sociological interpretation of the virus, considered as an intruder, without having to revisit laboratories and medical bodies or agencies. Taking into account the scope of the present paper, our analysis will be more cursory. As its founding father, Emile DURKHEIM strongly believed that sociology is similar to human body. That is to say, it is considered as a holistic whole based on a kind of solidarity among its members. Functionalism and “organicism” are theories that view social entities as organic and akin to living bodies. The core idea is that the social order and its interconnected functioning modes derive from the biological model. Before his death, DURKHEIM published his famous book on The Rules of the Sociological Method where he largely drew on C. Bernard’s findings included in his manual “Introduction to the Study of Experimental Medicine” [3]. In doing so, the French sociologist wanted to show that experiments are the basis on which this new emerging social science stands. According to this perspective, every pathology is a threat to the stability of a society. To make the difference between the normal and the pathological, DURKHEIM stated, “For societies and individuals, health is good and desirable. Illness is harmful and should be avoided. Inherent to social facts themselves, the choice of objective criteria will enable us to scientifically distinguish between health and disease throughout the different scales of social phenomena. Science can improve practical and field studies without departing from its own method” [4].

Conclusion

The virus is the intruder that nobody wishes to have at home. Yet, we end up by getting used to it. It bursts into an organism willing to set its members apart. Apart from the anatomy of a sick body, the social impacts of the virus are so frightening: a series of continuous social dramas deteriorated social bonds, the crumbling of family foundations, the collapse of the civilization based on that relative human serenity etc. That was DURKHEIM’s obsession even if he recognized the regular occurrence of all the ills that affect society. Suicide, a crime that he considers as a normal social fact, will not increase without resulting in a general impotence. The virus, as a sign that every society is subject to irregular functioning, causes anomie. This breakdown in social values and order reveals how difficult it is for institutions to assume their roles in improving the destiny of Humanity. A curious sociological premonition: during the uncertain lockdown periods, solidarity has gained more ground after having been stifled by a hegemonic world economy that promotes egoistic individualism. The virus is that intruder that nobody accepts, but once at home and looming around, everyone ends up getting used to it!

A large number of essays have stressed the fact the colonial experience would not have been possible if the colonized States had been resistant enough. Standing against the colonial virus becomes inert when a society suffers from social ills and divisions. Once compared to [5] forged the concept of “colonisability” to justify and reinforce this assertion. Due to its invisible nature, the virus mutates and attacks in a surprising and unpredictable way. It can take new forms. So, sociologists are expected to bring it under study in order to be able to provide an insightful knowledge and understanding of its propagation. The General Mc ARTHUR once said “It’s too late. These are the two words used to sum up lost battles.” [6]

What about if sociologists become crises experts?

References

  1. Samuel JOHNSON quoted by one of his best biographers, James BOSWELL (1952) in « The life of Samuel JOHNSON, Vol. III)
  2. https://www.frs-fnrs.be/docs/Lettre/lettre119.pdf p.30
  3. Bernard C (1865) Introduction à l’étude de la médecine expérimentale, Paris, Baillière.
  4. DURKEIM made a distinction between what is normal and what is pathological in The Rules of Sociological Method, chap. 3
  5. Benabi M (1954) Vocation de l’Islam, Paris, Seuil.
  6. Cited in https://www.forbes.com/sites/deloitte/2024/01/08/every-tool-in-the-toolbox-ai-regulations-that-arent-being-talked-about/?sh=1999cb6a76a3: “The history of failure in war can almost always be summed up in two words: ‘Too late.’ Too late in comprehending the deadly purpose of a potential enemy. Too late in realizing the mortal danger. Too late in preparedness. Too late in uniting all possible forces for resistance.”

Developing a Sexuality Education Survey for Women Living with HIV

DOI: 10.31038/AWHC.2025841

Abstract

Background: Advances in antiretroviral therapy have transformed HIV into a chronic condition, shifting care priorities beyond viral suppression toward quality of life and well-being. Sexual health is a central component of health; however, sexuality education for women living with HIV (WLH) has historically emphasized risk reduction and fertility control, often neglecting pleasure, sexual agency, and reproductive autonomy. The absence of tools to assess sexuality education experiences among WLH limits the ability to identify gaps, evaluate interventions, and deliver equitable, patient-centered HIV care.

Objective: To describe the development of a sexuality education assessment tailored for women living with HIV, informed by women’s lived experiences and grounded in sexual health and reproductive justice frameworks.

Methods: Between March and May 2024, two qualitative focus groups were conducted with WLH recruited from the Miami site of the Multicenter AIDS Cohort Study/Women’s Interagency HIV Study Combined Cohort Study (MWCCS). Participants reviewed and provided feedback on two existing instruments: the HIV-Positive Primary Prevention (HIV-PPP) Survey and the Student Sex Survey. Guided discussions focused on item relevance, language appropriateness, and identification of missing content domains. Audio recordings were transcribed verbatim and reviewed for accuracy. A multidisciplinary research team used a consensus-based analytic approach to determine item retention, modification, removal, and addition.

Results: Participants identified substantial limitations in existing sexuality education measures, including stigmatizing language, heteronormative assumptions, and an overemphasis on risk. Assessment refinement resulted in expanded domains addressing sexual pleasure, desire, intimacy, HIV-related counseling experiences, disclosure, U=U education, aging and menopause, and relational and structural influences on sexual agency. Women emphasized the importance of evaluating not only whether sexuality education occurred, but how it was framed; specifically whether it supported autonomy, dignity, and informed choice.

Conclusions: This study addresses a critical measurement gap by developing a sexuality education assessment tailored to the experiences of women living with HIV. Grounded in reproductive justice principles, the assessment moves beyond behavior-focused metrics to capture empowerment, agency, and well-being. This tool has the potential to inform research, clinical practice, and interventions aimed at integrating comprehensive, rights-based sexual health education into HIV care for women.

Introduction

Advances in antiretroviral therapy have transformed HIV into a chronic, manageable condition, allowing women living with HIV to experience near-normal life expectancy [1,2]. As a result, HIV care has expanded beyond viral suppression to encompass quality of life, mental health, and overall well-being, consistent with World Health Organization definitions of sexual health as a fundamental aspect of human health and human rights [3]. Despite this shift, sexuality remains insufficiently addressed within HIV research and clinical care, particularly for women.

Women living with HIV (WLH) experience sexuality at the intersection of biomedical, psychosocial, relational, and structural forces, including HIV-related stigma, gender norms, trauma histories, aging, and reproductive health transitions [4,5]. Historically, sexuality education for women with HIV has focused primarily on transmission prevention and fertility regulation, often excluding discussions of pleasure, desire, sexual functioning, intimacy, and sexual agency [6,7]. From a reproductive justice perspective, defined by the right to bodily autonomy, the right to have or not have children, and the right to parent and live with dignity in safe and sustainable communities, this narrow approach constrains women’s ability to make fully informed and self-determined decisions about their sexual and reproductive lives [8,9].

Empirical evidence demonstrates that many WLH report unmet needs related to sexual functioning, body image, menopausal changes, and communication with partners and healthcare providers [10,11]. Fear of HIV transmission and internalized stigma persist even in the context of robust evidence supporting Undetectable = Untransmittable (U=U), which has been shown to eliminate sexual transmission risk when viral suppression is maintained [12,13]. These challenges are disproportionately experienced by women who face intersecting structural inequities, including women of color, women aging with HIV, and women experiencing socioeconomic marginalization [14,15].

Despite increasing recognition of sexual well-being as integral to health, the extent to which WLH receive comprehensive, affirming, and rights-based sexuality education remains poorly characterized. This gap reflects, in part, the absence of assessment tools designed specifically for women living with HIV. Existing sexual health and HIV-related measures often prioritize risk behaviors and clinical outcomes, with limited attention to sexual pleasure, agency, power dynamics, reproductive decision-making, and trauma-informed care [16,17].

The lack of tools to assess sexuality education among WLH represents a critical limitation for advancing patient-centered, equity-oriented HIV care. Without such measures, it is difficult to identify educational gaps, evaluate interventions, train providers, or inform policy and program development. Importantly, assessment is a prerequisite for accountability and aligns with reproductive justice principles by centering bodily autonomy, informed choice, and dignity rather than fear-based or restrictive messaging [3,8].

The purpose of this study is to describe the development of a sexuality education assessment tailored for WLH. Grounded in women’s lived experiences and informed by contemporary sexual health and reproductive justice frameworks, this research aims to provide a foundational measurement tool to support holistic HIV care, guide intervention development, and advance the equitable integration of sexual well-being into HIV services.

Methods

Study Design and Participants

This qualitative study employed focus group methodology to inform the development of a sexuality education assessment tailored for women living with HIV (WLH). The study was approved by the University of Miami Institutional Review Board. Between March and May 2024, two focus groups were conducted with WLH to review existing sexuality education assessments and provide feedback to ensure relevance, appropriateness, and cultural responsiveness for the target population.

Participants were recruited from the Miami site of the Multicenter AIDS Cohort Study/Women’s Interagency HIV Study Combined Cohort Study (MWCCS), the largest and longest-running observational study of people living with HIV in the United States. Recruitment flyers were posted in areas where routine MWCCS study visits occurred. Interested individuals were referred to the study coordinator for screening and enrollment. Eligibility criteria included being an adult woman living with HIV and currently enrolled in MWCCS.

Instrument Identification and Review

A comprehensive review of the literature was conducted to identify existing sexuality education and sexual health assessments relevant to capturing women’s educational experiences across the life course. Although no single validated instrument adequately captured sexuality education experiences among WLH, two complementary tools were identified by the Principal Investigator (PI) as foundational for adaptation:

  1. The HIV-Positive Primary Prevention (HIV-PPP) Survey, which assesses HIV-related knowledge, sexual behaviors, and prevention practices before diagnosis, at the time of infection, and following diagnosis.
  2. The Student Sex Survey, which assesses exposure to school-based sexuality education, including curriculum type, duration, and perceived adequacy.

Together, these tools provided a starting framework to capture both formal sexuality education and HIV-specific sexual health experiences.

Focus Group Procedures

Two in-person focus groups were conducted in a private conference room within the same facility where MWCCS study visits occurred, enhancing participant familiarity and comfort. All participants provided written informed consent prior to participation. Each focus group was audio recorded and facilitated by the PI, with a research associate present to take handwritten notes and observe group dynamics but not participate in discussion.

Each focus group lasted approximately 90 minutes. Participants were guided through a systematic, item-by-item review of both instruments. Consistent with the study’s measurement development objectives, discussion focused narrowly on three domains:

  1. Relevance: Whether each item was appropriate and meaningful for WLH.
  2. Language: Whether wording was clear, respectful, inclusive, and non-stigmatizing.
  3. Content gaps: Identification of missing domains or questions necessary to capture women’s sexuality education experiences.

At the conclusion of each focus group, participants received $25 compensation for their time. Audio files were uploaded to the University of Miami’s secure, cloud-based server.

Analyses

Audio recordings were transcribed verbatim by two medical students completing a supervised research practicum. Following transcription, each medical student and a Master’s-level clinical research coordinator independently reviewed the transcripts against the audio recordings to ensure accuracy and completeness.

Using a consensus-based analytic approach appropriate for instrument development, the research team reviewed transcripts and summary notes to evaluate each survey item. Discussions focused on whether items should be retained, revised, or removed, and on identifying new items warranted based on participant feedback. The PI facilitated iterative team meetings to resolve discrepancies and finalize decisions regarding item inclusion and wording.

Rather than formal thematic coding, analyses emphasized pragmatic content validity, clarity, and alignment with reproductive justice and sexual health frameworks. This approach is consistent with early-phase measure development aimed at refining relevance and acceptability prior to psychometric testing.

Outcomes

Assessment Refinement and Content Expansion

Nine women participated across both focus groups (five in focus group #1, 4 in focus group #2). Focus group feedback resulted in substantial refinement of both source instruments. Participants consistently emphasized that sexuality education experiences extended far beyond school-based instruction and were shaped by healthcare encounters, HIV diagnosis, aging, relationships, and sociocultural context.

Key outcomes of the assessment development process included:

  • Removal or revision of stigmatizing or heteronormative language, particularly terminology perceived as outdated, judgmental, or male-centered.
  • Expansion of items addressing sexual pleasure, desire, and satisfaction, domains participants noted were rarely addressed in prior education yet central to quality of life.
  • Inclusion of HIV-specific educational experiences, such as counseling received at diagnosis, discussions of U=U, disclosure guidance, and provider communication about intimacy.
  • Addition of life-course perspectives, including menopause, aging, and changes in sexual identity or partnerships over time.
  • Integration of relational and structural factors, including power dynamics, partner communication, and experiences of stigma within healthcare settings.

Participants strongly endorsed the importance of assessing not only whether education occurred, but how it was delivered, including tone, framing, and whether it supported autonomy versus fear.

Alignment with Reproductive Justice Principles

Across both focus groups, participants articulated themes closely aligned with reproductive justice, including bodily autonomy, informed choice, and dignity. Women emphasized the need for education that affirmed their right to desire, intimacy, and self-determination, regardless of HIV status. These perspectives directly informed the inclusion of items assessing whether sexuality education was empowering, neutral, or restrictive.

Discussion

This study describes the development of a sexuality education assessment specifically tailored for women living with HIV, addressing a critical gap in HIV research and care. Although sexual well-being is widely recognized as integral to health, women’s sexuality, particularly in the context of HIV, remains under-measured and under-prioritized. Findings from this qualitative assessment development process underscore the inadequacy of existing tools to capture the complexity of WLH’s educational experiences.

Consistent with prior literature, participants reported that sexuality education was frequently framed through risk, fear, and restriction, rather than pleasure, agency, and well-being [10,16]. Importantly, women identified HIV diagnosis as a pivotal moment of sexuality education, yet noted substantial variability in the quality and content of counseling received. These findings highlight the need for tools that assess sexuality education across clinical, relational, and life-course contexts, not solely in adolescence or school settings.

By grounding assessment development in women’s lived experiences and reproductive justice principles, this study advances a rights-based approach to sexual health measurement. The resulting assessment moves beyond behavior-focused metrics to capture autonomy, dignity, and empowerment, dimensions essential for equitable, patient-centered HIV care.

Limitations

Several limitations warrant consideration. First, participants were recruited from a single MWCCS site, which may limit generalizability to WLH not engaged in longitudinal research cohorts or HIV care. Second, the sample size was intentionally small, consistent with qualitative focus group methodology, but not intended to capture the full diversity of WLH experiences. Third, this study focused on content development rather than psychometric validation; reliability and validity testing are needed in future research.

Next Steps and Future Directions

The revised assessment is currently being piloted among 30 WLH. Future work will involve pilot testing the refined sexuality education assessment in a larger and more diverse sample of WLH to evaluate feasibility, reliability, and construct validity. Subsequent analyses will explore associations between sexuality education experiences and outcomes such as sexual satisfaction, stigma, mental health, relationship quality, and engagement in care.

Ultimately, this assessment has the potential to inform intervention development, provider training, and policy by making women’s sexuality education experiences visible and measurable. Incorporating such tools into HIV research and clinical practice represents a critical step toward holistic, reproductive justice–aligned HIV care that affirms not only longevity, but pleasure, dignity, and self-determination.

Sexual Wellness, Education, Experiences, and Treatment in Positive Women (SWEET P)

Please fill out the below questions to the best of your ability. All answers are anonymous, so please be as honest as possible.

Demographics:

Age: _____________

  1. Are you Hispanic or Latino
    A. Yes
    B. No
  2. Which one or more of the following would you say is your race? (Check all that apply)
    A. White
    B. Black or African American
    C. Asian
    D. Native Hawaiian or Other Pacific Islander
    E. American Indian or Alaskan Native
    F. Other
  3. Which of the following best represents how you think of yourself
    A. Straight
    B. Gay or Lesbian
    C. Bisexual
    D. Other
  4. What is your annual household income from all sources?
    A. Less than $10,000
    B. $10,000 – $25,000
    C. $25,000 – $35,000
    D. $35,000 – $50,000
    E. $50,000 – $75,000
    F. $75,000 – $100,000
    G. More than $100,000
    H. Don’t Know/Unsure
  5. What is your living situation today?
    A. I have a steady place to live
    B. I have a place to live today, but I am worried about losing it in the future
    C. I do not have a steady place to live (I am temporarily staying with others, in a hotel, in a shelter, living outside on the street, on a beach, in a car, abandoned building, bus or train station, or in a park)
  6. What is your highest level of school completed?
    A. No schooling completed
    B. Some school-no diploma
    C. High School Diploma or GED
    D. Some college-no degree
    E. Trade/Technical School or Associates Degree
    F. Bachelor’s Degree
    G. Advanced Degree (Masters, Doctorate, or Professional Degree)

About Your Sex Education:

Note: This survey uses the term “sex education” to mean instruction about anything relating to preventing pregnancy and sexually transmitted infections, HIV/AIDS, abstinence from sexual activity, healthy decision-making around sexuality, and other sexual health topics.

  1. Did you receive you sex education before or after diagnosis
    A. Before
    B. After
    C. Both
    D. Don’t Know/Unsure
  2. Where were you first taught sex education (sex ed)?
    A. School
    B. Home
    C. Community outreach/program
    D. Healthcare setting (hospital, clinic, doctors office, etc.)
    E. Other (personal experience, movie/media……):
    F. I have never learned about sex education
  3. Were you ever taught sex education in school
    A. Yes
    B. No
    C. Don’t Know/ Unsure
  4. If you didn’t have sex education in school, why? (Only answer if 9 is ‘No’ or ‘Don’t Know/Unsure’)
    A. Parents didn’t want me to learn sex ed in school.
    B. Parents forgot to sign the consent form.
    C. Instructions were not offered.
    D. Other ___________
  5. If you have been taught sex education in school, when did you have it?
    A. Elementary school
    B. Middle school
    C. High school
    D. College
    E. Don’t Know/Unsure
  6. In what type of school system did you receive your sex education:
    A. Public school
    B. Private school
    C. Religious school
    D. Charter school
    E. Other: _________________________________________________________________
  7. Was the class mandatory?
    A. Yes
    B. No
    C. Don’t Know/Unsure
  8. How long did your instructor spend on sex ed in school?
    A. Less than a day
    B. 1 Day
    C. 3-4 Days
    D. 1 week
    E. More? Specify: ________
  9. Which topics did the sex education instruction cover? (Choose all that apply)
    A. No Sex/Abstinence
    B. Condoms
    C. Contraception (birth control)
    D. How to make healthy decisions
    E. Body image
    F. Gender roles
    G. Gay and Lesbian relationships (LGBTQ+)
    H. Sexual abuse/Healthy Relationships
    I. Local resources for sexual health (where to get STI testing)
    J. Consent
    K. Reproductive health (menstrual cycle)
    L. Sexual pleasure
    M. Reproduction (how pregnancy happens)
    N. STI prevention
    O. How to approach conversations about safe sex with a partner
    P. Other: __________________________________________________________________
  10. Which of the following best describes what you were taught about preventing STD’s and unintended pregnancy?
    A. Abstinence (don’t have sex) was the only thing discussed.
    B. Condoms and birth control mentioned, but most time was spent on abstinence.
    C. Abstinence and condoms/birth control were both discussed fully.
    D. Abstinence mentioned, but most time was spent on condoms/birth control.
    E. Abstinence was not discussed.
  11. Which statement most accurately reflects what you were taught about condoms?
    A. “When used properly, condoms are effective in preventing unintended pregnancy, sexual transmitted infections (STDs), and HIV.”
    B. “Condoms are not effective in preventing unintended pregnancy, STDs, or HIV.”
    C. I was not taught about condoms.
  12. In sex ed class, I generally felt: (Choose all that apply).
    A. Comfortable
    B. Uncomfortable
    C. Accepted for who I am
    D. Judged for who I am
  13. To what extent were you satisfied with your sex ed class?
    A. Very satisfied
    B. Satisfied
    C. Neutral
    D. Dissatisfied
    E. Very dissatisfied

The Sex Education You Want:

  1. Do you think your school should have spent more or less time on sex ed?
    A. More
    B. Less
    C. Fine how it is
  2. At the time, did you feel comfortable asking your parent(s) or guardian(s) about these topics (e.g. safe sex, healthy relationships, etc.)?
    A. Yes
    B. No
    C. Sometimes
    D. Don’t Know/Unsure

Factors in Becoming HIV Positive:

  1. Check the MAJOR behavior(s) you believe led to you becoming HIV positive:
    A. Vaginal sex without a condom
    B. Vaginal sex with a condom
    C. Receptive anal-penis sex without a condom
    D. Anal-penis sex with a condom
    E. Oral (mouth-penis) sex
    F. Oral (mouth-vagina) sex
    G. Sharing needles
    H. Blood transfusion
    I. I do not know
    J. Other: ___________________________________________________________
  2. Please describe your relationship (at the time of transmission) to the person(s) who may have passed HIV to you:
    A. Spouse, husband/wife, life partner, significant other
    B. Non-spouse but longstanding friend and/or longstanding sex/needle partner
    C. Casual acquaintance, casual sex partner, and/or one-night stand
    D. Sex worker
    E. Blood transfusion
    F. Needle
    G. Mother-to-baby (born with it)
    H. Nonconsensual sex
    I. I have no idea who may have passed HIV to me
    J. Other: ______________________________________________________________
  3. Where do you think you became infected with HIV?
    A. In Miami-Dade County
    B. Outside of Miami-Dade County, but in Florida
    C. Outside of Florida, but in the US
    D. Outside of the US
    E. Don’t Know/Unsure
  4. When you became HIV positive, what was your living situation?
    A. I had a steady place to live
    B. I had a place to live, but was worried about losing it
    C. I did not have a steady place to live (I was temporarily staying with others, in a hotel, in a shelter, living outside on the street, on a beach, in a car, abandoned building, bus or train station, or in a park)
    D. Don’t Know/Unsure
  5. Which of the following statements, if any, were true for you when you became HIV positive?
    A. I didn’t know the person was HIV positive
    B. I was feeling depressed, lonely, just not caring
    C. I was feeling like I really needed to have sex
    D. I was drunk or high at the time
    E. I didn’t know about safer sex and/or safer needles
    F. I was feeling in love
    G. S/he was so good-looking, health-looking, clean-looking
    H. I did not like condoms, so I didn’t use them
    I. Neither of us had condoms with us
    J. I didn’t feel assertive enough to insist on safer sex
    K. I was trying to get or keep my partner
    L. I was sexually abused as a child/adolescent
    M. The person told me s/he was HIV negative
    N. I was feeling like I really needed to get high (inject drugs)
    O. I thought my partner was only having (unsafe) sex with me
    P. The condom broke
    Q. My partner(s) refused to practice safer sex
    R. I did not have access to clean needles
    S. I hated/was conflicted about my sexual attractions and desires
    T. I was feeling damned by God
    U. I needed money or other things
    V. I wanted to become infected
    W. My partner(s) refused to practice safer needles
    X. Other_________________________________________________

Concerns of Persons with HIV Postdiagnosis:

  1. Since you were diagnosed with HIV, which of the following statements were true for you even once:
    A. I have engaged in safer sex (sex with condoms) with at least one other person
    B. I avoided sex, chose not to have sex, or shut down sexually
    C. I have had sexual contact with other(s) without disclosing my HIV status
    D. I have engaged in unprotected anal/vaginal sex (without condoms) with another person(s) who I knew was HIV positive
    E. I have engaged in unprotected anal/vaginal sex (without condoms) with another person(s) who was HIV negative or whose HIV status I did not know
    F. I have engaged in unprotected oral sex (mouth-penis/vagina without condoms) with another person(s) who was HIV negative or whose HIV status I did not know
    G. I have shared needles with another person(s) who I knew was HIV positive
    H. I have shared needles with another person(s) who was HIV negative or whose HIV status I did not know
    I. I have engaged in other risk activities that could pass on HIV
    J. I have given serious thought to having a baby
    K. On at least one occasion, I have thought seriously about ending my life
    L. On at least one occasion, I have tried to kill myself
  2. Since you were diagnosed, which of the following issues, if any, have been problems or challenges for you:
    A. Practicing/maintaining safer sex
    B. Practicing/maintaining safer needle use
    C. Alcohol and/or other drug use
    D. Feeling confident that I will not infect others
    E. Knowing how to tell potential sex partner(s) that I am HIV positive
    F. Being intimate with other people
    G. Experiencing sexual pleasure
  3. Since being diagnosed, which, if any, of the following topics have you received education on (check all that apply):
    A. Disclosing my HIV status to others
    B. How to talk to a sex partner(s) about PrEP
    C. How to experience sexual pleasure
    D. How to practice safe sex
    E. How to prevent HIV transmission (regarding sexual contact, sharing needles, mother to child, blood transfusion)

Future Sexual Education:

  1. What topics, if any, do you think should be implemented in sex education classes in schools?
    A. Abstinence
    B. Condoms
    C. Contraception (birth control)
    D. How to make healthy decisions
    E. Body image
    F. Gender roles
    G. Gay and Lesbian relationships (LGBTQ+)
    H. Sexual abuse/Healthy relationships
    I. Local resources for sexual health (where to get STI testing)
    J. Consent
    K. Reproductive health (menstrual cycle)
    L. Sexual pleasure
    M. Reproduction (how pregnancy happens)
    N. STI prevention
    O. How to approach conversations about safe sex with a partner
    P. Sexual Pleasure
    Q. Other: __________________________________________________________________
  2. Do you think adults could benefit from taking a sex education class?
    A. Yes
    B. No
    C. Don’t Know/Unsure
  3. Do you think adults living HIV could benefit from taking a sex education class?
    A. Yes
    B. No
    C. Don’t Know/Unsure

Sexual Pleasure

  1. Have you ever learned about sexual pleasure?
    A. Yes
    B. No
    C. Don’t Know/Unsure
  2. If so, where did you learn about sexual pleasure
    A. School
    B. Personal experience
    C. Media (movies, tv shows, social media, etc.)
    D. Friends
    E. Family
    F. Other __________________________________________________________________
  3. Did you ever learn about the female sexual response cycle
    A. Yes
    B. No
    C. Don’t Know/Unsure
  4. Have you ever learned about female sexual dysfunction (a persistent or recurrent problem with sexual response, desire, arousal, orgasm, or pain during intercourse that causes distress or interpersonal difficulty)
    A. Yes
    B. No
    C. Don’t Know/Unsure

References

  1. UNAIDS. Global HIV & AIDS statistics—fact sheet. UNAIDS.
  2. Centers for Disease Control and Prevention. HIV Surveillance Report. CDC.
  3. World Health Organization (2006) Defining sexual health: report of a technical consultation on sexual health. WHO.
  4. Logie CH, James L, Tharao W, Loutfy MR (2011) HIV, gender, race, sexual orientation, and sex work: a qualitative study of intersectional stigma experienced by women living with HIV in Ontario, Canada. PLoS Med 8(11): e1001124. [crossref]
  5. Turan B, Budhwani H, Fazeli PL, et al. (2017) How does stigma affect people living with HIV? The mediating roles of internalized and anticipated HIV stigma in the effects of perceived community stigma on health and psychosocial outcomes. AIDS Behav 21(1): 283-291. [crossref]
  6. Higgins JA, Hirsch JS (2007) The pleasure deficit: revisiting the “sexuality connection” in reproductive health. Perspect Sex Reprod Health 39(4): 240-247. [crossref]
  7. Sobo EJ (1995) Choosing unsafe sex: AIDS-risk denial among disadvantaged women. University of Pennsylvania Press.
  8. Ross LJ, Solinger R (2017) Reproductive Justice: An Introduction. University of California Press.
  9. SisterSong Women of Color Reproductive Justice Collective. Reproductive justice brief. SisterSong.
  10. Bhatta DN, Liabsuetrakul T, McNeil EB (2017) Social and behavioral interventions for improving quality of life of women living with HIV. Health Quality life outcomes 15: 80. [crossref]
  11. Nappi RE, Cucinella L, Martella S, Rossi M, Tiranini L, et al. (2018) Sexual dysfunctions in women living with HIV. Climacteric 21(4): 371-377.
  12. Rodger AJ, Cambiano V, Bruun T (2016) Sexual activity without condoms and risk of HIV transmission in serodifferent couples when the HIV-positive partner is using suppressive antiretroviral therapy (PARTNER study) JAMA 316(2): 171-181. [crossref]
  13. Cohen MS, Chen YQ, McCauley M, et al. (2011) Prevention of HIV-1 infection with early antiretroviral therapy. N Engl J Med 365(6): 493-505. [crossref]
  14. Crenshaw K (1991) Mapping the margins: intersectionality, identity politics, and violence against women of color. Stanford Law Rev 43(6): 1241-1299.
  15. Bowleg L (2012) The problem with the phrase women and minorities: intersectionality—an important theoretical framework for public health. Am J Public Health 102(7): 1267-1273. [crossref]
  16. Tolman DL (2002) Dilemmas of desire: teenage girls talk about sexuality. Harvard University Press.
  17. Ford JV, Barnes R, Rompalo A, Hook EW (2013) Sexual health training and education in the U.S. Public Health Rep 128(Suppl 1): 96-101. [crossref]

Obesity, Socioeconomic Transitions, and the Evolving Social Gradient of Non-Communicable Diseases in Low- and Middle-Income Countries

DOI: 10.31038/AWHC.2025835


Non-communicable diseases (NCDs) are now the leading cause of premature mortality in low- and middle-income countries (LMICs), accounting for more than 80% of early NCD deaths worldwide. As LMICs undergo rapid demographic, nutritional, and epidemiological transitions, obesity has emerged as a central driver of cardiometabolic risk—particularly among women. Although NCDs have long been characterised as “diseases of affiuence” in developing country settings, accumulating evidence suggests that this social gradient is weakening. New longitudinal evidence from India provides timely insights into how rising obesity may be reshaping the distribution of NCD risk across socioeconomic groups [1].

Using two waves of the nationally representative panel data from the India Human Development Survey (IHDS) 2004-05 & 2011- 12, which followed more than 24,000 women of reproductive age over seven years, Barik(2025) assessed the risk of developing non- communicable disease (NCDs) like hypertension, diabetes, or heart disease among the overweight/obese women. The study demonstrates that overweight and obesity significantly increase the likelihood of subsequent NCD onset, independent of age, education, caste, and household economic status. Crucially, the analysis shows that the rich–poor gap in NCD risk narrows sharply once women become overweight or obese, indicating that excess body weight acts as a powerful leveller of disease risk across socio-economic strata.

This finding resonates with emerging evidence from other LMICs. In Bangladesh, analyses of Demographic and Health Survey data have documented rapid increases in overweight and obesity among urban women across both wealthy and poorer households. While NCD prevalence remains higher among richer women, obesity- related metabolic risk factors—such as hypertension and raised blood glucose—are increasingly observed among women from lower wealth quintiles, particularly in urban settings [2]. Studies from Bangladesh suggest that once high BMI is established, socioeconomic advantage offers limited protection against cardiometabolic risk, mirroring the convergence observed in India.

Similar patterns are evident across sub-Saharan Africa, where obesity prevalence—especially among women—has risen sharply over the past two decades. In countries such as Ghana, South Africa, and Kenya, obesity is no longer confined to affiuent urban elites. Nationally representative surveys show that overweight and obese women from poorer households face risks of hypertension and diabetes comparable to those of wealthier women once BMI is accounted for. In several African settings, the association between socioeconomic status and hypertension weakens substantially after adjusting for adiposity, indicating that obesity increasingly mediates NCD risk across income groups [3].

Together, these findings point to a broader global shift: obesity is progressively eroding traditional socioeconomic gradients in NCDs across LMICs. While absolute disease burden often remains higher among wealthier populations—owing to better diagnosis and longer survival—the marginal effect of obesity on NCD risk appears strikingly similar across economic strata. This has profound implications for public health policy, which in many LMICs continues to implicitly prioritise affiuent or urban populations in NCD prevention strategies.

The Indian evidence is particularly valuable because of its longitudinal design, which overcomes a major limitation of much LMIC research that relies on cross-sectional data. By tracking changes in BMI over time, the study shows that women who remain chronically overweight have the highest risk of developing NCDs, while those who return to normal BMI experience a significantly lower risk. This dynamic perspective reinforces the importance of mid-life and reproductive-age interventions, a finding that aligns with cohort evidence from South Asia and Africa showing that weight gain during early adulthood strongly predicts later cardiometabolic disease.

The policy relevance of these results extends beyond India. Across LMICs, reproductive years represent a critical but underutilised window for obesity and NCD prevention among women. Pregnancy- related weight gain, declining physical activity, and changing diets contribute to sustained overweight, yet health systems often disengage once maternal and child health goals are met. Integrating weight management, nutrition counselling, and routine screening for hypertension and diabetes into maternal and primary care services could yield long-term benefits in India, Bangladesh, and sub-Saharan Africa alike.

At the same time, the study underscores persistent challenges in NCD surveillance. Reliance on self-reported diagnoses likely underestimates disease prevalence among poorer women with limited access to screening—a concern echoed in African and South Asian contexts. If underdiagnoses disproportionately affects disadvantaged groups, the observed convergence in NCD risk across wealth strata may in fact understate the true extent of inequality erosion driven by obesity.

In conclusion, longitudinal evidence from India adds to a growing body of global research demonstrating that obesity is transforming the social patterning of NCDs in LMICs. The convergence of disease risk across economic groups once overweight is established challenges outdated notions of NCDs as diseases of prosperity. Effective prevention will require population-wide strategies that prioritise healthy weight maintenance across the life course, rather than narrowly targeting the affiuent. As countries across South Asia and sub-Saharan Africa confront parallel transitions, addressing obesity among women must become central to equitable global NCD policy.

References

  1. Barik D (2025) Risk of Developing NCDs in Later Life among the Overweight and Obese Women in India: Insights from a Nationally Representative Longitudinal Margin: The Journal of Applied Economic Research 19(2): 1-18. https://doi. org/10.1177/00252921251394148
  2. Das S, Debnath M, Sarkar S, Rumana AS (2022) Association of overweight and obesity with hypertension, diabetes and comorbidity among adults in Bangladesh: evidence from nationwide Demographic and Health Survey 2017-2018 data. BMJ Open 12(7): e052822. [crossref]
  3. Yaya S, Ekholuenetale M, Bishwajit G (2018) Differentials in prevalence and correlates of metabolic risk factors of non-communicable diseases among women in sub-Saharan Africa: evidence from 33 BMC Public Health 18(1): 1168. [crossref]

Israel, Hamas and Strategy-Focused Experiments Using AI and Mind Genomics

DOI: 10.31038/MGSPE.2025524

Abstract

Using a combination of Mind Genomics thinking to structure an experiment and AI simulation of respondents, the study considered the impact of 15 different introductions of the Hamas-Israel conflict on the response to elements or messages about Hamas and Israel. Each of the studies was run with 500 synthetic respondents, created from personas, these personas in turn created from different combinations of up-front self-profiling classification questions. The results show the strategy of using ordinary least-squares (OLS) dummy variable regression model to simultaneously estimate the contribution of a basic message (element), introduction, and self-described AI-based persona.

Keywords

AI personas, Framing effects, Hamas-Israel conflict, Mind genomics, Synthetic respondents

Introduction—The Emerging Science of Mind Genomics

Mind Genomics is an experimentation-oriented, data-driven approach to understanding the way that people make decisions about the world of the ordinary. Mind Genomics treats the contents of people’s everyday thinking as a “genome” to be sequenced and analyzed, using short and concrete idea elements combined into vignettes. The experiment requires respondents to rate these vignettes on a scale. The analysis reveals which specific messages drive ratings, then uncovers potentially new-to-the-world mind-sets, defined as simple but often radically different ways people respond to these ordinary stimuli [1-3].

Rather than instructing respondents to evaluate single ideas through a questionnaire, Mind Genomics tries to emulate nature by presenting ideas in combination, with these ideas being different aspects of a topic. The respondent’s task is to react to the combination or vignette, rather than evaluate each idea in the vignette one idea at a time. The inspiration for using combinations comes from the realization that in our daily lives, we react to combinations virtually all our waking hours. The underlying rationale is that people typically spend most of their day confronting combinations of features in nature and react to them in what appears to be an automatic way. People usually have no problem navigating through many mixtures of stimuli and decisions and then moving on. Indeed, when we stop to think about our daily lives, we realize that the isolation and evaluation of single ideas or messages is the unusual, the aberrant, and the rare, if ever, experienced [4,5].

Mind Genomics evolved from the intersection of psychophysics, consumer research, and experimental design. The term Mind Genomics was borrowed from the sequencing metaphor from biological genomics, while deliberately avoiding biological reductionism.

Early instantiations of Mind Genomics used a simple experimental design in which each respondent evaluated every one of the different messages several times in various combinations of elements, these combinations called vignettes. Each respondent rated the vignettes created according to a complete experimental design, allowing the ratings from the individual respondent to be analyzed by ordinary least squares regression (OLS). OLS regression revealed the contribution of every one of the elements to the rating assigned to the vignette [6].

Mind Genomics advanced the effectiveness of OLS regression by creating many different but isomorphic experimental designs. The basic design structure was systematically modified so that each new “daughter design” comprised the same elements but in various combinations. The mathematical structure of the design was constant, so each respondent’s data could be analyzed either alone or in a subgroup of “similar respondents.” At the same time, however, the actual combinations differed from respondent to respondent. In this way, the research could cover a great deal—almost all of the possible combinations.

A key benefit of the permuted experimental design is that the researcher can cover a wide range of stimuli, which changes the research dynamic. In comparison, non-Mind Genomics researchers often spend a great deal of time discovering the most promising elements, wordsmith them, and then spend time creating the vignettes. A great deal of effort goes into polishing the final vignettes to make them “just right.” The result is a loss of time, and an increased expenditure to get to the “right answer(s).” Today’s effort spends valuable time and scarce resources to “short list” relevant ideas of a topic using judgment and afterwards spending one’s research budget for testing on a limited set of the most promising combinations. This effort could take months. In contrast, Mind Genomics tests many different combinations so quickly that the researcher gets a good idea of the strong elements, even with no prior knowledge of the topic and at the beginning of the research. The happy outcome is a process with Mind Genomics measured in hours [7].

The now “classic” structure of a Mind Genomics experiment is to create four questions that tell a story, and for each question, create four mutually substitutable answers. The respondent’s task is to read a vignette and a collection of answers, then assign a rating to the combination. Each respondent rates a unique set of 24 vignettes in the so-called 4×4 design (four questions, four answers or elements for each question). An underlying permutation structure changes the specific combinations that a respondent will. Still, in the end, each respondent evaluates every element five times, in vignettes which comprise four, three, or two elements. Each respondent appears five times across 24 vignettes and is absent 19 times. Finally, a vignette consists of either four, three, or two elements, but each question or silo can contribute at most one element to the vignette. This structure ensures that all 16 elements are statistically independent of each other. Statistical independence will play an essential role in the subsequent analysis because it allows the regression model to collect absolute coefficients. These coefficients—measures of the degree to which the element “drives” the rating—provide a numerical measure of how the respondent thinks about a topic. The Mind Genomics set-up allows for absolute values of coefficients, which means that the coefficients can be compared across time and different conditions [8].

Analyzing the data generated by a Mind Genomics experiment follows a now-standard procedure. The ratings are assigned on a labelled category or Likert scale, from a low of 1 to a high of usually 5, but occasionally 7 or 9. A labelled 5-point scale has become the most popular scale because it is easy to understand, and because each scale point can be labelled.

If we were to summarize the process from the point of communicating to management, we might use the following summary generated by Microsoft’s AI program, Co-Pilot. AI summarizes the process as follows:

Mind Genomics begins by decomposing a complex real-world situation into a small set of meaningful, researcher-defined aspects called silos. Each silo represents a distinct question about the situation such as goals, constraints, stakeholders, or emotions. For every silo the researcher writes four concise, concrete elements that capture plausible variations of that aspect. These elements are translated into short, vivid phrases that can be recombined to form many realistic micro-scenarios. The design then constructs a balanced set of vignettes, so each element appears multiple times across respondents in controlled permutations. Presenting these vignettes to respondents forces rapid, intuitive reactions rather than deliberative rationalization. The pattern of element combinations that elicit strong responses reveals how people mentally synthesize the situation from its parts. Mind Genomics therefore generates a map of which elements drive perception, urgency, intent, or preference in the synthesized scenario. This mapping preserves causal clarity because the experimental design treats elements as independent factors. The method makes explicit the common mind-sets people bring to the same situation, showing clusters of consistent responses. From these clusters, researchers can infer people’s implicit rules to combine facts into meaning. The result is a reproducible, empirically grounded synthesis of the situation as real people mentally construct it.

Applying the Approach to National Strategy—The Case of Israel and Hamas

The 15 different introductions to the Hamas-Israel situation, all crafted in a soft and non-judgmental way, sets the scene for the adding “meaning” or at least some “tonality” to the different descriptions of the elements, which are evaluated by respondents after being combined into vignettes according to an underlying experimental design. The soft description emphasizes situational facts, competing narratives, and the range of plausible civilian experiences without clearly endorsing any party [9-11].

To ensure broad coverage, the soft description highlights key dimensions such as security concerns, humanitarian impacts, territorial claims, and international reactions. The 15 different introductions function as experimental manipulation: small changes in wording can reveal whether framing shifts downstream evaluations.

The 15 Sets of Slightly Modified Instructions, Setting up Different Expectations

The study was run 15 times. The same elements were used for each of the 15 iterations. What changed was the introductions themselves, those that would be “read by the AI” as basic introduction to the issue. The objective was to determine whether changes in the orientation used at the start of the study would have any dramatic effects on the data. The only thing which changed from iteration to iteration was the specific introduction. Table 1 shows the introductions themselves. Table 2 shows a schematic of how the study’s orientation was systematically varied.

Table 1: The 15 different orientations. The orientation began with the basic introduction at the top of the table.

Table 3 presents the set of four questions or silos for the study, and the four answers or elements. When working with human respondents, the practice is to craft relative short answers, no more than 15 words or so. Beyond that, the respondent reports that it takes too much effort to read the vignettes. In contrast, when working with AI and synthetic respondents, preliminary efforts suggested that the data would be more precise when the answers are extensive, leaving little to interpret. Thus, the AI-generated answers or elements in Table 1 are longer than what would be the case were the respondents to be actual people. Such length provides a “tighter” specification of the information.

Table 2: Schematic of the differences in respondent orientation across the 15 “experiments.”

Creating Synthetic Respondents (Personas) by Combining Answers to Self-profiling Classification

Today’s research has taken a new turn with AI, and more specifically with synthetic respondents created by AI. These synthetic respondents are personas, generated from classification questions, the various answers to which lie at the basis of the persona. Today’s AI presumably can respond to test stimuli as if it were the persona. The study presented here used AI (ChatGPT 3.5) to create different personas, and then to have each created persona evaluate a complete set of 24 vignettes as if it were that person. The subsequent analysis is thus done on machines acting as a people, rather than as people themselves [12-14].

Table 3: The four questions and the four answers to each question generated by Idea Coach (ChatGPT 3.5 embedded in the Mind Genomics platform, BimiLeap.com).

Table 4 shows nine different self-profiling classification questions and answers selected by the researcher. In addition, the Mind Genomics platform automatically generates questions for age and for gender. Thus, after the analysis, the synthetic respondent—the persona—has 11 distinct statements about the respondent. It is these 11 statements of the persona used by AI to evaluate and then rate each test vignette.

Table 4: AI selected one of two genders, one of seven age groups, and one answer from each question below. The combination along with the appropriate introduction (out of 15) specified a “persona” which evaluated a vignette and assigned a rating.

Vignette Testing with Synthetic Personas

Each of the 15 experiments or studies comprised all elements and varying combinations of the groups formed from the answer in Table 3. Using an underlying experimental design, the Mind Genomics platform generated a set of 24 element combinations for each respondent. The experimental design was set up to ensure that each of the 16 elements would appear five times in 24 vignettes, that each vignette would have a minimum of two elements and a maximum of four elements, and that no vignette would ever have two elements from the same silo (viz., no vignette would ever have two different answers to the same question). Finally, each respondent would test a unique set of combinations or vignettes. The mathematical structure for each set of vignettes would be the same, but the specific combinations of elements would be different. This strategy is known as a permuted experimental design [15]. The permuted experimental design ensures that the data from each respondent can be analyzed separately using standard statistical methods, such as dummy-variable ordinary least squares (OLS) and clustering [16].

The synthetic respondent used a labelled 5-point scale to rate each vignette. Table 5 shows the scale. The scale has two sides. The first side addresses the expected response of the Gazans (do not want peace; do want peace). The second side addresses the publicly expressed desire for peace, whether from visionaries or from the public.

Table 5: The instructions for the rating scale and the 5-point rating scale.

Transforming the Ratings to Binary Dependent Variable (BDVs) to Prepare for Regression.

As it is constituted, the rating scale is an example of a nominal scale. The numbers themselves are just placeholders. To prepare for the analysis, the rating scale must be transformed. There are five key transformations shown in Table 6.

Table 6: The five key transformations to generate binary dependent variables (BDV), appropriate for analysis by ordinary least-squares (OLS) regression.

Table 7 shows the outcome from analyzing the full set of 180,000 “observations, created by AI. The numbers in the body are the coefficients for each of the four BDV’s developed by combining ratings, and then the five single BDV’s. The coefficients for the elements are “absolute” because the elements were combined by the underlying permuted experimental design. The design comprised “zero’s,” where an element would not appear, ensuring that the level of each of the 7500 synthetic respondents were statistically significant. In technical terms, the coefficients were estimated with a meaningful “zero condition.” Statistical modeling suggests that coefficients around 21 or higher are statistically significant. For these results, only two elements of the 16 approach significance (two diplomacy channels, hotline). Importantly, most of the elements do well, all with coefficients of 17 or higher. This type of result differs from what is often observed with real people, namely a longer “downwards” tail with more elements scoring in single digits and low teens. Our first conclusion is that where AI can synthesize respondents, the version used here—Chat GPT3.5—is too positive compared to what we observe with people.

Table 7: General model for 7500 simulated respondents. Strong performance is defined as a coefficient of 21 or higher for the coefficients for the 16 elements, and coefficients of 11 or higher for relative coefficients where the lowest scoring element ends up being the baseline.

The second section of Table 7 shows the contribution of each of the 15 introductions to the coefficients. Keep in mind the AI was given the introduction. In the case of the introductions, each of the 15 studies had a different introduction. When OLS regression is used, we cannot estimate the absolute coefficient, since every study had an introduction. We must choose one of the introductions to be the baseline, with that baseline introduction removed from the regression. The researchers chose introduction 15. The data from the 15 introductions suggest that only introductions 3 and 14 drive a response from AI that the Gazans want peace.

When looking at the coefficients for the self-profiling questions, the strongest (most positive coefficients) and the weakest performers (most negative) make a great deal of sense. Different coefficients would have emerged had we chosen different elements to be the reference but the differences among pairs of products would have been the same. As a result, the conclusions would end up being the same, but the size of the coefficients would have differed. Self-profiling statements which accept Israel end up generating higher coefficients for R54 and for R5 than self-profiling statements which reject Israel.

An important consideration in this analysis concerns the nature of the coefficients for the self-profiling classification. In this study, the self-profiling options were not statistically independent. Thus, one of the classification options must be the reference. It does not matter which of the options serves as the reference. The reference ends up being omitted from the large linear regression, with the unhappy consequence that the coefficients for the self-profiling question are relative values. Differences of 11 or higher approach statistical significance.

How the Orientation to AI Affects the Distribution of Ratings

Table 8 shows a summary of the 15 “experiments” run with synthetic respondents. The rows correspond to the 15 different introductions. Table 8 shows two sets of data columns. The first set (R1-R5) shows the distribution of the five ratings (R1-R5), as well as the four binary combinations of ratings (R54, R21, R52, R41).

Table 8: Distribution of rating points by each introduction.

One important observation from Table 8 is the preponderance of positive responses, especially ratings of 5 but also ratings of 4. With human respondents, the percent of “5” on a similar 5-point labelled scale is much lower. Table 8 shows that R5, the most positive response, is selected more frequently than one might assume, given a negative introduction.

Our first observation from this detailed analysis of the effect of introduction is that AI is not as discerning as a human respondent. Simply stated, AI generates ratings that are more positive than the responses that would be obtained from actual people.

Additional insights regarding the contribution of the introductions emerge when we consider the coefficients of the 16 elements. Recall that the elements were created to follow an experimental design. This design allows the estimation of absolute coefficients for each respondent. The equation is a simple linear model: BDV = R54 = k1A1 +k2A2 … k16D4. This regression model can be done for each respondent, or for any defined subgroup of respondents. The analysis was run 15 times, once for each of the 15 introductions. Each regression analysis thus involved 16 independent variables, one for each element, and 12,000 rows of data, 24 rows for each of 500 respondents.

Table 9 shows the coefficients for each of the 16 elements for each of the 15 introductions. The study generates a total of 240 comparable coefficients. The coefficient gives a sense of how much of the BDV can be traced to the contribution of the element. Parallel analysis of modeling with an additive coefficient suggests statistical significance when the coefficient is 10. The element value of 10 estimated without an additive constant corresponds to a coefficient of 20-21 when the equation is 1estimated without an additive constant, viz. regression through the origin. The strong, statistically significant elements are shown in shaded cells.

Table 9: Performance of the 16 elements for each of the 15 introductions to the problem. The dependent variable is R54 (Gazans want peace).

Discussion and Conclusions

This approach provides practical and ethical benefits for the examination of contentious conflicts within a structured framework. This approach enables researchers to analyze the ways in which framing and message components interact to generate varying levels of support, opposition, or ambivalence, all while minimizing dependence on the often-chaotic nature of field debates. The approach allows organized comparisons among segments defined by specific personas, including a general panel, pro-Israel groups, pro-Palestinian groups, and those with mixed attitudes.

Using Mind Genomics coupled with AI simulation through synthetic respondents permits swift iterations. The happy outcome is that teams can explore many soft descriptions, adjust vignette components, and re-execute simulations. This process enables them to assess the robustness of their findings prior to engaging in expensive research involving human subjects.

This approach mitigates potential harm by situating potentially distressing content within a controlled synthetic testing environment, all the while ensuring that the personas remain anchored in empirical response patterns. This approach enhances interpretability by generating parameter estimates for each individual element and their interactions. Such estimates can be utilized by policy communicators and researchers to predict potential public responses effectively. Additionally, it aids in identifying which framings inadvertently enhance polarization, as opposed to those that promote thoughtful reconsideration and discussion.

This approach does not substitute for meticulous field validation using human samples; rather, it serves as a robust tool for triage and the generation of hypotheses. This approach serves as a responsible and evidence-based strategy aimed at exploring the ways in which contextual descriptions and individual orientations collaboratively influence responses to conflict narratives. In other words, the approach provides a new way to explain topics at “scale.”

References

  1. Moskowitz HR, Gofman A, Beckley J, Ashman H (2006) Founding a new science: Mind genomics. Journal of Sensory Studies 21(3): 266-307. [crossref]
  2. Papajorgji P, Moskowitz H (2024) Mind Genomics: Origins, Evolution, Inner-Workings. In:  The Mind of Everyday:  Combining Individual and Artificial Intelligence. Dec 29 (pp. 91-143) Cham:  Springer Nature Switzerland.
  3. Porretta S, Gere A, Radványi D, Moskowitz H (2019) Mind Genomics (Conjoint Analysis): The new concept research in the analysis of consumer behaviour and choice. Trends in Food Science & Technology 84: 29-33. [crossref]
  4. Ludtke A, editor (1995) The history of everyday life: Reconstructing historical experiences and ways of life. Princeton University Press; May 21. [crossref]
  5. Naukkarinen O, Vasquez R (2017) Creating and Experiencing the Everyday Through Daily Life. Experiencing the Everyday. May: 166-85.
  6. Moskowitz HR (2012) ‘Mind genomics’: The experimental, inductive science of the ordinary, and its application to aspects of food and feeding Physiology & Behavior 107(4): 606-13. [crossref]
  7. Papajorgji P, Moskowitz H (2024) Mind Genomics: Origins, Evolution, Inner-Workings. In:  The Mind of Everyday:  Combining Individual and Artificial Intelligence. Dec 29 (pp. 91-143) Cham:  Springer Nature Switzerland.
  8. Kover A, Papajorgji P, Moskowitz H, editors (2022) Applying mind genomics to social sciences. IGI Global. May 13. [crossref]
  9. Atran S, Rodriguez-Gómez L, Yilmaz K, Gómez Á (2025) How Gaza Sees the 2023-2025 War and the Future of the Israel-Palestine Conflict. New England Journal of Public Policy 37(1): 11. [crossref]
  10. Segell G. Israel vs (2025) Hamas expands to eight fronts. InExploring the Implications of Local and Regional Conflicts. (pp. 1-26) IGI Global Scientific Publishing.
  11. Vitman Schorr A, Sasson Shoshan T, Govrin Y, Tokatly L, Kahlon D, Ghanem L, Dremer S, Plantonov V, Davidovich S, Lev-Wiesel R (2025) Is the Future Ours to See? Israelis’ Future Perception Following Hamas Massacre. Journal of Loss and Trauma. Apr 2: 1-27. [crossref]
  12. Bisbee J, Clinton JD, Dorff C, Kenkel B, Larson JM (2024) Synthetic replacements for human survey data? the perils of large language models. Political Analysis. Oct;32(4): 401-16. [crossref]
  13. Davidson T, Karell D (2025) Integrating Generative Artificial Intelligence into Social Science Research: Measurement, Prompting, and Simulation. Sociological Methods & Research. May 7: 00491241251339184.  [crossref]
  14. Shrestha P, Krpan D, Koaik F, Schnider R, Sayess D, Binbaz MS (2024) Beyond WEIRD: Can synthetic survey participants substitute for humans in global policy research? Behavioral Science & Policy. Oct;10(2): 26-45.
  15. Gofman A, Moskowitz H (2010) Isomorphic permuted experimental designs and their application in conjoint analysis. Journal of Sensory Studies. Feb;25(1): 127-45. [crossref]
  16. Gofman A, Moskowitz HR, Bevolo M, Mets T (2010) Decoding consumer perceptions of premium products with rule‐developing experimentation. Journal of Consumer Marketing 27(5): 425-36. [crossref]

Work Challenges and Adjustment among Novice Firefighters in Taiwan

DOI: 10.31038/PSYJ.2025764

Abstract

This study explored the work-related challenges and adjustment experiences of novice firefighters in Taiwan. Using a qualitative thematic analysis design, we conducted semi-structured, in-depth interviews with four novice firefighters (one woman and three men) aged 27–33 years (M = 29.75) who had 2–3.5 years of work experience. The findings revealed several salient challenge-related themes, including perceived unfairness and oppression in the workplace, ethical dilemmas in practice, organizational and interpersonal stressors, stress associated with insufficient work resources, and pressure arising from public expectations and commentary. Regarding adjustment and coping, participants expressed substantial concerns about using formal mental health resources and therefore relied primarily on personal resources to manage stress. Implications for practice and directions for future research are discussed.

Keywords

Novice firefighters, Work challenges, Work adjustment, Resilience

Work Challenges and Adjustment among Novice Firefighters in Taiwan

In recent years, global climate anomalies have contributed to increasingly complex and unpredictable disasters. In Taiwan, economic development and population concentration—together with larger, taller, and more diverse building structures—have expanded firefighters’ operational demands and increased exposure to hazardous labor conditions [1]. To address workforce shortages, the National Fire Agency launched the “Firefighting Workforce Enhancement Initiative” in 2018 and added 3,100 firefighting personnel [2]. Under these conditions, the training and development of novice firefighters becomes especially critical. Without resilience- building opportunities and a health-supportive work environment, novice personnel may experience excessive stress and maladaptation that ultimately contribute to early exit from the profession. Despite the practical significance of this issue, research on novice firefighters’ work challenges and psychological adjustment in Taiwan remains limited. Novice firefighters may face structural, systemic, and hierarchical constraints; high job demands may intensify perceived stress, while access to organizational resources may be restricted. Over time, an imbalance between excessive demands and insufficient resources may contribute to anxiety, depression, and stress-related symptoms, increasing the risk of physical and psychological burnout. Accordingly, this study aims to describe (a) the work-related challenges novice firefighters in Taiwan encounter and (b) their experiences of adjustment and coping.

Firefighters and Their Work

Firefighters’ work encompasses a broad range of duties. In Taiwan, novice firefighters commonly perform two major categories of frontline tasks: (1) disaster response and life-saving rescue, including fire suppression, rescue operations across disaster types, and the management and deployment of rescue resources; and (2) emergency medical services (EMS), including the planning, supervision, and delivery of prehospital emergency care, as well as communication and coordination with medical institutions. In this study, we use the term fire and emergency service work experience to denote frontline operational experience spanning disaster response/rescue, life-saving or technical rescue, and EMS. Firefighting is widely recognized as a high-risk occupation characterized by substantial physical demands, heavy psychological load, and high task complexity. As disaster responders, firefighters are required to enter and operate at hazardous scenes; even under life-threatening and terrifying conditions, professional responsibility typically precludes avoiding the scene or refusing assigned duties. Firefighting work is dangerous, unpredictable, and time-sensitive. Prolonged exposure to heavy workloads, shift-related strain, and traumatic events places firefighters at elevated risk for exhaustion and compromised physical and mental health [3]. Firefighters often must remain in a continuous “combat- ready” state, making firefighting a particularly high-stress occupation [4]. Long-term on-call shift systems can disrupt sleep and interfere with normal physical and psychological recovery processes [5]. Kuo [6] further noted that, driven by a sense of mission and responsibility, firefighters must meet public expectations; at disaster scenes, they may suppress physical discomfort and psychological distress in order to execute tasks calmly and courageously. When such reactions accumulate without adequate processing, firefighters may develop PTSD-related symptoms (e.g., hypervigilance, insomnia, exaggerated startle responses, irritability, and concentration difficulties). If psychological trauma is not addressed in a timely manner, symptoms may intensify over time.

Operational conditions also constrain emotional processing. During missions, firefighters often lack the time and space to process emotions and may temporarily set aside personal feelings until tasks are completed, at which point they begin to experience and interpret the impact of the event. Frequent exposure to disaster incidents may require firefighters to re-enter distressing rescue contexts before psychological equilibrium is restored, thereby accumulating negative emotions and traumatic experiences [7]. In addition, firefighters face public pressure through media coverage and public praise or criticism, which may further intensify occupational stress [8].

Novice Firefighters

Novice firefighters are commonly defined as those with 2–4 years of service [9]. They are expected to learn and perform core duties such as fire suppression and emergency medical response while adapting to the realities of frontline work. In Taiwan, however, empirical research on novice firefighters remains limited. Existing literature has primarily examined safety and training effectiveness, the influence of overall health on performance, the effects of stress, and the development of professional knowledge [10]. Because novice firefighters often serve as frontline personnel, they may experience substantial pressure associated with disaster response. Prior evidence suggests that shorter tenure is associated with stronger stress responses among firefighters [11,12]. Novice firefighters may also report higher stress than senior firefighters [13]. Moreover, they require an adjustment period to manage challenges such as the gap between training and real-world practice and the complexity of diverse duty types [14]. At the same time, they must learn to navigate bureaucratic features of the firefighting system and pressures related to obedience and hierarchical authority [15].

Job Demands and Resource Provision

Work environments shape employees’ health, well-being, and performance [16]. The Job Demands–Resources Model (JDRM) provides a useful framework for understanding how occupational conditions influence stress and adjustment [17]. Job demands refer to aspects of a job that require sustained physical and/or psychological effort and include negative factors at physical, psychological, social, or organizational levels; such demands entail specific physiological and/ or psychological costs. Examples include workload, time pressure, emotional load, and role conflict. Although moderate job demands may stimulate motivation and alertness, chronically excessive demands can initiate a health-impairment process that depletes resources and increases burnout risk, physical and mental health problems, and performance decrements.

In contrast, job resources refer to positive job characteristics at physical, psychological, social, or organizational levels. Job resources support goal attainment, reduce job demands and their associated costs, and promote personal growth, learning, and development. Resources may operate at the task level (e.g., autonomy), organizational level (e.g., career development opportunities), interpersonal level (e.g., supervisor and coworker support), and job design level (e.g., performance feedback). Adequate resources activate a motivational process, enhance engagement, and are associated with positive outcomes such as safety behaviors, job performance, and organizational commitment.

Safety-Oriented JDRM

Building on the JDRM, scholars have proposed a safety-oriented JDRM that foregrounds safety-relevant job demands and safety- relevant resources [18]. For firefighting, this model highlights four demand dimensions: (1) Workload, referring to the speed and volume of task completion under time constraints and pressure; high time pressure has been linked to increased firefighter fatality rates. (2) Physical demands, including high-intensity biomechanical activities such as running, carrying, and ladder climbing; excessive exertion contributes to fatigue that can undermine reaction time and adherence to safety procedures. (3) Emotional demands, referring to the psychological effort required to manage emotions and cope with affective reactions (e.g., fear, suppression); sustained emotional labor may deplete energy reserves and contribute to emotional exhaustion. (4) Complexity, involving cognitive demands associated with handling multiple difficult tasks, maintaining situational awareness, making rapid decisions, and conducting risk assessments—particularly in life- threatening contexts.

Structural Insufficiency of Resources

Fire service organizations may also face structural shortages of resources. Insufficient resources have been identified as a key factor undermining firefighters’ psychological health [19]. In addition, interpersonal conflict, discrimination, harassment, and negative perceptions of organizational justice can weaken resilience and are associated with anxiety, depression, and physical illness [20]. In particular, perceptions of organizational and systemic unfairness increase mental health risks and are closely tied to hierarchical stress. In such contexts, employees may engage in proactive behaviors that reshape their work conditions. These include job crafting (actively modifying one’s job or available resources) and self- undermining (stress-related mistakes that inadvertently increase one’s own job demands). Novice personnel may adjust their work behaviors in response to hierarchical pressure, or they may reduce engagement due to fear of making mistakes. When social support is limited, interpersonal resources become scarce and fragile, and this vulnerability is closely linked to trauma-related stress symptoms, depression, and emotional exhaustion [21]. Moreover, negative views of organizational systems (e.g., unfair policies or promotion practices) may further elevate mental health risks. Interpersonal conflict can also obstruct help-seeking and support access, producing a “double hit” of resource loss. Under conditions of high hindrance, high demands, and systemic resource deficiencies, job demands may substantially exceed resource provision, creating a structural imbalance that undermines job performance directly or indirectly through psychological distress.

The Buffering Effects of Resources

The JDRM also emphasizes personal resources, defined as individuals’ beliefs about their ability to control and influence their environment. Job resources can buffer strain associated with job demands and mitigate the negative effects of work stressors. This buffering function suggests that resources may be especially protective under high-demand conditions, supporting both well-being and work performance. Common personal resources include self-efficacy, optimism, and resilience. Such resources predict work engagement by strengthening confidence in one’s capacity to manage challenges and sustain involvement. Personal resources may also operate similarly to job resources by buffering the adverse effects of job demands on stress. In sum, when employees face high demands (e.g., heavy workload or emotional load), greater resources (e.g., autonomy, social support, performance feedback, and professional development opportunities) are generally associated with lower burnout and emotional exhaustion.

Organizational Culture

Organizational culture is another critical influence on firefighters’ well-being and help-seeking. A traditional culture emphasizing “toughness, silence, and self-sacrifice,” along with emotional taboo, may inhibit seeking psychological support [22]. In contrast, framing professional psychological help-seeking as a constructive form of self- care may facilitate a healthier organizational climate [23].

Resource adequacy in the fire service also matters. The quality, quantity, and suitability of personal protective equipment are central to firefighters’ sense of safety. Station facilities, vehicles, staffing, and occupational health and safety measures represent foundational resources that directly shape the safety and comfort of the work environment. Supervisor support is likewise influential: when perceived support from managers, family, or friends decreases, depressive symptoms tend to increase. Supervisors’ support, trust, and care may strengthen subordinates’ resilience. Leadership practices— such as reward and punishment systems, internal management, duty scheduling, performance evaluation, discipline, and performance demands—may function either as resources or as stressors, depending on how they are enacted and experienced.

Firefighters’ Adjustment and Coping

Carver et al. [24] developed a coping strategies inventory that categorizes coping behaviors into problem-focused coping, cognitive restructuring coping, emotional support coping, and avoidance coping. Chung and Chiou [25] suggested that firefighters who predominantly use problem-focused coping tend to recover gradually, whereas reliance on avoidance coping may increase risk for psychological disorders. Prior research indicates that firefighters often rely on individual coping strategies to manage work stress. Lee [26] and Chen [27] found that after exposure to death or major critical incidents, firefighters often cope privately; when adjustment is insufficient or support is unavailable, some may request transfer or resign. Some firefighters manage occupational stress through a passive stance (e.g., “you get used to it over time”) [28], whereas others use strategies such as active reflection for improvement or emotional detachment [29]. Firefighters may also cope by maintaining task focus and calm during operations [30] or by adopting passive coping patterns, allowing emotions to fade over time through emotional numbing, suppression, or self-isolation. Although these strategies may stabilize functioning in the short term, they may carry negative long-term consequences.

Resilience also shapes adjustment. Firefighters with higher resilience are more likely to appraise stress as a challenge rather than a threat [31]. Firefighters commonly report using conversation, exercise, leisure activities, and faith practices to reduce stress. Professional competence also increases with accumulated experience and knowledge, which can strengthen coping capacity. Individuals with stronger self-efficacy tend to believe they can control and change situations, thereby moderating the impact of perceived stress on burnout.

Peer support functions as an important buffer by enabling emotional exchange, experience sharing, mutual reminders, and opportunities for emotional ventilation. Colleagues’ competence, knowledge, and experience can enhance individual safety, and camaraderie is a strong predictor of firefighters’ mental health. Firefighters often reduce distress through peer dialogue—talking through tasks and coping approaches—and through experiential transfer from senior peers. Everyday conversations and informal gatherings may also help relieve emotional strain. In Taiwan, fire agencies have established counseling and guidance systems and offer courses and lectures. They may provide psychiatric services, psychological counseling, and consultation, sometimes combined with medication to improve sleep conditions [32]. Overall, building a comprehensive mental health support system—including accessible psychological services, effective communication channels, regular health check-ups, financial and emotional support, and health- and law-related information—may strengthen organizational support and enhance firefighters’ resilience.

Method

This study employed thematic analysis to examine the occupational experiences of novice firefighters in Taiwan. The analytic focus was directed toward describing both the substantive content and the processes embedded in their work, thereby highlighting the complexity of frontline practice and the trajectories through which participants adapted and coped.

Participants

A purposive sampling strategy was adopted. Four frontline novice firefighters were recruited through professional networks by the first author. The sample comprised one woman and three men, aged 27–33 years (M = 29.75), with work tenure ranging from 2 to 3.5 years— consistent with the career stage of novice firefighters (defined as within four years of service). Participants were drawn from brigades located in diverse service contexts: an eastern rural area, a central semi-urban area, a central rural area, and a northern metropolitan area. Two participants held certification as Emergency Medical Technicians–Paramedic (EMT-P), and one participant held Rescue Technician certification.

Data Collection

Data were generated through semi-structured, in-depth interviews. The first author conducted one individual interview with each participant, lasting approximately 60–90 minutes. Participants were invited to narrate their occupational challenges and their experiences of adaptation and coping. The interview guide encompassed questions on: motivations and expectations for entering the fire service; job tasks and sources of stress; interpersonal interactions; utilization of organizational resources; coping strategies; and perceived impacts of work on physical and mental health. Interviews were conducted in quiet, convenient locations selected by the first author. Prior to each interview, participants were informed of the study’s purpose and procedures, potential benefits and risks, and their rights. Ethical principles were observed throughout, including respect for autonomy and confidentiality. Written informed consent was obtained before interviews commenced. All interviews were audio-recorded and subsequently transcribed verbatim by the first author.

Data Analysis

Thematic analysis was conducted following Braun and Clarke’s [33] framework. The first and second authors conducted the analysis using Braun and Clarke’s thematic analysis. They engaged in repeated reading of transcripts, open coding, identification of cross-case patterns, and iterative refinement of thematic coherence. Themes were subsequently defined, named, and integrated into the analytic report. Throughout the process, the researchers maintained an open and reflexive stance, engaging in ongoing dialogue to ensure rigor. Particular attention was devoted to issues raised by participants concerning tenure, hierarchical power relations, the novice role, and work-related challenges, including organizational and structural barriers, resource utilization, and coping/adaptation processes.

Trustworthiness and Ethics

To enhance trustworthiness, multiple strategies were employed, including triangulation, reflexivity, thick description, and cross- checking. These measures ensured coherence between themes and textual evidence, strengthened descriptive appropriateness, and enhanced credibility. Ethical standards were rigorously observed: all participants signed informed consent forms and were informed of the study’s purpose, rights, and procedures for voluntary participation and withdrawal. Audio files and transcripts were de-identified and presented using pseudonyms to ensure anonymity. All study materials were securely stored by the first author, and data were used exclusively for academic purposes.

Results

Seven themes emerged from the thematic analysis. Themes are illustrated with representative participant narratives.

Unfairness and Oppression at Work

Novice firefighters characterized their work as highly complex, unpredictable, and psychologically demanding. One participant described each dispatch as opening a “mystery box,” because incidents could involve life-threatening conditions such as earthquakes, rockfalls, or fires. This uncertainty not only tested physical limits but also created substantial psychological burden.

Beyond the inherent danger of the job, participants emphasized that risk exposure was distributed unevenly across ranks. They reported that novices were frequently assigned the most hazardous roles during operations. For example, one participant noted that junior firefighters were expected to be the first to force entry into unknown environments. He also described death-related incidents in which novices could be tasked with handling particularly distressing duties (e.g., carrying severed body parts). He described this as an unspoken rule: “the most junior firefighter is expected to face unknown risks first or bear the greatest known risks.” Such expectations reflected a power imbalance between senior and novice firefighters and contributed to participants’ perceptions of unfairness and oppressive treatment.

Ethical Dilemmas in Practice

In addition to operational danger, participants reported repeated exposure to ethical and moral shocks, especially during emergency medical work. In out-of-hospital cardiac arrest (OHCA) cases, they often faced dilemmas about whether resuscitation was clinically meaningful—particularly when family members insisted on continuing resuscitation even when firefighters perceived it as futile. In these moments, participants described feeling ethically conflicted and powerless. One participant reflected: No intubation, no defibrillation… and then when we arrived at the hospital, the doctor said there was no chance—just stop resuscitation… I kept wondering… Was my CPR and oxygen meaningful?”Participants also described moral conflict from the opposite direction: even when resuscitation was successful, severe post-resuscitation outcomes could raise questions about long- term suffering and family burden. One participant stated: “Even though I brought him back—breathing, pulse—he would only survive with those machines. Sometimes I struggle inside… Should I save him or not?” Overall, participants emphasized that firefighters often confront ethically fraught situations without clear ethical guidance or standardized norms. For novices in particular, real-world emergency care required enduring ongoing tension among professional obligations, personal values, and ethical considerations.

Systemic Organizational and Interpersonal Pressures

Participants described hierarchical pressure and workplace bullying as major sources of stress. Some supervisors were portrayed as hostile toward newcomers (described as “newcomer killers”), frequently scolding, intimidating, or imposing punitive controls. One participant recalled that during the first six months he was reprimanded almost daily and received leave restrictions for minor issues: “For about the first six months, I was getting scolded almost all day… For small things—five minutes late, missing a signature—I was banned from taking leave for two months… he wrote it down and kept scolding me.” Another participant described feeling constantly monitored and scrutinized by supervisors and senior colleagues, which made his work experience “miserable.” He gave an example of being questioned for not attending activities that occurred on his scheduled days off: “There were two activities… both fell on my days off, and then I was called in and asked, ‘Why didn’t you participate?’”

Participants further reported that some senior firefighters undermined novices’ confidence through disparaging remarks. One participant described being mocked while studying for professional exams: “A senior saw me studying… and said, ‘You won’t pass,’… those sarcastic, belittling things.” They also noted that minor station-related issues (e.g., a gym not being tidied immediately or trash temporarily left) could trigger scolding, and supervisory pressure sometimes extended into rest time. Participants reported being unable to relax even during breaks; using a phone could invite suspicion, and taking leave could lead to criticism for “not helping the team” with dispatch duties. Accumulated pressure affected both physical and psychological functioning. One participant described missing a dispatch alarm due to a malfunctioning bell near his bed; fear of being reprimanded increased stress and contributed to sleep disturbance.

In addition to interpersonal dynamics, participants described institutional unfairness that amplified helplessness. One participant stated that performance evaluations were opaque and highly subjective—dependent on “the supervisor’s mood”—yet directly influenced salary and promotion. When effort was not matched by recognition or reward, participants reported frustration and demoralization. Another participant described being reassigned to another brigade despite holding strong paramedic qualifications, which he experienced as unfair and identity-undermining.

Finally, participants described rigid systems and dysfunctional equipment as chronically depleting. They reported pressure to meet unreasonable key performance indicators and to complete large volumes of administrative tasks despite inadequate staffing and limited experience. Under directives from higher-level leadership, core emergency work was sometimes displaced by unrelated activities (e.g., sports events) and could even become entangled with election- related events—at the expense of essential rescue and EMS duties. Participants also described being constrained by outdated protocols: even after learning improved clinical approaches, they were expected to follow older procedures because regulations had not been updated and senior members insisted on “the old way.” Collectively, these systemic conditions were perceived as obstructing professional development, eroding motivation for learning and innovation, and fostering high pressure, helplessness, diminished self-efficacy, and weakened professional identification.

Scarcity of Job Resources

Participants consistently emphasized that job resources were insufficient relative to the demands they faced. At the basic operational level, one participant reported chronic shortages of essential supplies and incomplete distribution of equipment. For example, ambulance gauze ran out and was not replenished for an extended period; paramedic medication kits were not fully issued, forcing firefighters to purchase supplies themselves or seek support from physicians: “Resources are very limited—equipment, gear, consumables. The gauze on the ambulance ran out… and the whole station had none because it wasn’t issued… The medication kit wasn’t provided, so I bought it myself… This affects how well I can do the job, and it affects my quality of life.”Another participant highlighted chronic understaffing. On some days, only three personnel were on duty, increasing the likelihood of station closure or even single-person dispatch, which substantially elevated operational risk. Resource scarcity also extended to compensation. One participant stated that pay was disproportionate to high risk and long working hours, estimating an hourly wage lower than that of part-time student workers. He also described institutional limits on overtime pay, whereby excess overtime was converted to compensatory leave rather than paid overtime. Additionally, leave taken across months could reduce the salary of a given month, despite leave being largely nonvoluntary in practice. Participants experienced these arrangements as discouraging and demoralizing. Participants further described resource deficits in organizational infrastructure and administrative systems. One participant reported frequent crashes in electronic systems with little improvement. Shared computers lacked internet access and could not support routine administrative tasks; outdated equipment was neither functional nor replaced. These barriers disrupted both administrative operations and professional emergency duties, increasing stress, draining energy, and undermining morale.

Pressure From Public Expectations and Commentary

Participants described substantial pressure arising from public expectations, scrutiny, and online commentary. When rescue or response efforts were perceived as inadequate, participants experienced intense criticism and what they viewed as unreasonable accusations, which increased emotional disturbance and work stress. They noted that even cautious decision-making could be judged negatively, resulting in complaints or online attacks. One participant listed common disputes, such as being criticized for driving “too slowly,” questioned for running red lights during emergency transport, reported for siren noise at night, or asked by bystanders to move hoses during active fire response. He recalled: “Once, during a fire response, I was still dealing with it, and there was a hose on the ground. Someone said he wanted to drive home and asked me to move the hose… I said, ‘I’m still fighting a fire!’”Overall, participants expressed a sense that “whatever we do, the public will criticize.” They reported that minor mistakes could be amplified, leaving them uncertain about how to respond and pressured by constant evaluation. This perceived scrutiny affected their occupational identity and sense of meaning in the work.

Personal Ajustment and Coping

In response to the imbalance between high demands and limited resources, participants described diverse coping strategies that ranged from proactive competence-building to emotional self-protection and cognitive reframing. Proactive learning and competence-building. Some participants demonstrated strong agency. One participant repeatedly volunteered for training opportunities despite low seniority and initial supervisory rejection: “I’m pretty junior, so it wouldn’t be my turn… I recommended myself… he rejected me two or three times before finally letting me go.” Another participant described enrolling in an instructor-training program to rekindle motivation: “Last year… I changed my mindset… I decided to recover my passion… I applied for instructor training, and I got in.”

Participants also described practice-based improvement, especially in EMS. One participant reported reviewing the quality of CPR and airway management after OHCA cases, requesting simulation training, and striving to improve care quality. Another described systematically refining EMS procedures— practicing operational details, adjusting workflows, strengthening competence, and promoting team improvements. He explained how training translated to smoother field performance: “When I arrived on scene, I followed the training model… and the next time, I didn’t waste time… it went smoothly, and I completed the EMS work successfully.” He further described keeping organized records, publicly noting procedural gaps, advocating updated protocols, and optimizing team workflows. These efforts increased accomplishment and self-efficacy; when improved performance was recognized during later dispatches, confidence was reinforced in a positive feedback cycle.

Self-protective Emotional Strategies

In contrast, some coping strategies emphasized denial, minimization, or emotional detachment. One participant described himself as “digesting emotions quickly,” “letting it pass,” and being “forgetful,” noting that positive events could override work-related distress: “I digest (negative emotions) pretty fast… after sleeping a few times, I’m fine… If something happy happens, it covers up the unpleasantness.” Another participant rationalized supervisory harshness by framing militarized management as something men “should” endure, interpreting survival of strict training as evidence of becoming competent.

Compartmentalization and Technical Focus

One participant described being briefly frightened at the scene but switching immediately to professional judgment and action. After returning to the station, he reviewed dispatch footage to evaluate technical execution and team communication, using procedural focus to avoid being absorbed in distress: “Back at the station, I watch the footage again… if there are problems, we discuss and improve next time. That way, I don’t think too much… or get stuck on why it happened.”

Relational Coping and Future-oriented Strategies

Some participants described selectively collaborating with reliable senior firefighters to support smoother teamwork. Others attempted to transform unfair treatment into motivation for self-improvement— strengthening training, obtaining key EMS certifications, and preparing for potential future transfers to other units.

Cognitive Reframing

One participant reduced distress by reframing EMS work as “taxi” service: complete necessary tasks without judging whether patients were misusing EMS resources and without ruminating: “We arrive a hospital and see he (the patient) is actually okay—fine, take measurements, transport him, then happily go back to rest… I imagine my work is like a taxi driver.”

In summary, across accounts, the above strategies reflect novice firefighters’ attempts to preserve functioning, maintain competence, and sustain meaning under chronic stress in work.

Concerns About Using Counseling Resources

Although participants acknowledged that fire agencies provide mental health resources (including on-site counseling), they expressed substantial concerns about using them. One participant noted that counseling appointments required taking personal leave; after exhausting shifts, he preferred to use leave for sleep and rest. Another participant expressed fear of stigma and confidentiality breaches, reporting limited trust in counseling privacy and concern that supervisors might learn about counseling use: “Privacy… If I go talk to a counselor… will my supervisor know and ‘check on’ me?… Work stress is private… Counselors keep records—are they stored somewhere? Would people know?… Would I be labeled as having a mental problem?”

One participant questioned whether counseling could address structural sources of distress—such as authoritarian supervision, unfair treatment, or outdated equipment—given that these conditions would remain unchanged after counseling: “If I’m bullied long-term… would talking to a counselor make me better?… I still have to go back, and the supervisor is the same… So is counseling useful? I have a question mark.”

Overall, participants viewed counseling as potentially providing temporary emotional ventilation but offering limited practical benefit for stressors rooted in persistent organizational and structural conditions. Consequently, they tended to rely more on personal coping resources than on formal psychological services.

Discussion

The novice firefighters in this study characterized firefighting as an occupation involving high risk, heavy physical demands, substantial psychological load, and high complexity. They also emphasized that the work environment and organizational culture strongly shape mental health and necessitate coping strategies to manage occupational stress. These findings are consistent with Bakker and Demerouti’s argument that the work environment influences employees’ health, well-being, and performance. Taken together, the results suggest that novice firefighters’ early-career adjustment is not determined solely by the inherent dangers of frontline work, but also by organizational arrangements, leadership practices, resource provision, and public scrutiny—factors that jointly produce a structural pattern in which demands often exceed available resources. Participants described having to cope with diverse operational and administrative challenges, as well as bureaucratic features of the firefighting system and hierarchical pressures requiring obedience. Their narratives also highlighted pronounced hierarchical stress, including implicit workplace rules that positioned novices to assume high-risk and high-impact tasks, and supervisory practices experienced as punitive or oppressive. In addition, the findings echo prior evidence that firefighters are exposed to societal expectations and external evaluation—including media coverage and public praise or criticism—which can intensify occupational stress.

Smith and Dyal’s safety-oriented JD–R model is particularly useful for interpreting these results, as it emphasizes both safety- related job demands and safety-related resource provision. The current findings partially converge with this framework and with the four dimensions of firefighting job demands described by Smith and Dyal. Participants repeatedly reported working under stringent time constraints and pressure, which heightened stress. They also described emotional demands, especially in emergency medical and urgent rescue contexts, where fear, shock, and emotional suppression were common. Such emotional demands can deplete psychological energy and contribute to emotional exhaustion. In addition, participants emphasized cognitive complexity: managing multiple difficult tasks in life-threatening contexts required sustained situational awareness, rapid decision-making, risk assessment, and the execution of emergency interventions.

Notably, when these demands were experienced as persistent and cumulative, participants’ accounts suggested a health-impairment process consistent with the JD–R perspective. For example, some participants described wanting only to rest during time off and reported limited capacity for additional activities, including psychological counseling. This pattern underscores that excessive demands may constrain recovery opportunities and gradually erode psychological resources, thereby increasing risks for burnout and compromised functioning over time.

In the safety-oriented JD–R model, resource provision is not a peripheral issue but a central determinant of safety and well- being. Participants in this study described a broad range of resource constraints, including shortages of supplies, malfunctioning or obsolete systems, insufficient infrastructure (e.g., computers and internet access), and understaffing that increased operational risk. They also expressed dissatisfaction with compensation and overtime arrangements that were perceived as disproportionate to workload, risk, and time demands. These findings align with Payne and Kinman’s argument that insufficient resources represent a key factor undermining firefighters’ psychological health, and with research emphasizing that adequate equipment, facilities, staffing, and occupational health and safety measures influence the safety and comfort of firefighters’ work environments.

At the interpersonal and organizational levels, participants described authoritarian supervision, frequent reprimands for minor issues, disparaging remarks, and a sense of constant scrutiny. They also reported unfair or inconsistent evaluation and managerial practices, leaving them uncertain about behavioral standards and concerned that outcomes depended on supervisors’ subjective judgments. These experiences are consistent with prior literature identifying interpersonal conflict and low organizational justice as critical risk factors that erode resilience and increase vulnerability to anxiety, depression, and physical illness. They also reinforce the importance of supervisory support: deficiencies in managerial support have been linked to elevated depressive symptoms, whereas supervisors’ trust, care, and support may strengthen resilience. In the present study, perceived unfairness and hierarchical oppression appeared to operate as chronic “hindrance demands,” increasing stress while simultaneously restricting access to key resources such as psychological safety, guidance, and professional recognition.

A salient contribution of this study is the centrality of ethical dilemmas, particularly in OHCA cases. Participants described moral conflict when family requests for resuscitation diverged from firefighters’ assessment of futility, and they also described ambivalence when resuscitation succeeded but survival implied severe impairment and long-term dependence on life-sustaining equipment. These experiences suggest that novice firefighters may be exposed to moral distress—ethical discomfort arising when one’s professional judgment conflicts with external demands or constrained options—yet they may lack clear norms, ethical guidance, and structured opportunities to process these conflicts. Accordingly, ethical strain should be considered a meaningful component of job demands in EMS-related duties, not merely an emotional byproduct of trauma exposure.

Participants’ coping strategies reflected both active and avoidant patterns. Some described relatively active coping approaches, including cognitive reframing, transforming frustration into motivation for professional development, pursuing training and certifications, and strengthening technical competence. These strategies appeared to enhance self-efficacy, a key personal resource within the JD–R framework, and are consistent with evidence that believing one can control or change situations may mitigate the impact of stress on burnout. Participants also described drawing on interpersonal resources, such as selectively collaborating with supportive senior colleagues, which partially supports the safety-oriented JD–R proposition that social support buffers the psychological impact of high-demand work. At the same time, several participants reported passive or self-protective coping—emotional suppression, compartmentalization, denial, replacement, and self- isolation—used to maintain immediate functioning. These patterns align with prior research suggesting that some firefighters use passive stances or emotional detachment to cope, while others engage in active reflection and improvement. Although avoidant strategies may provide short-term stabilization and enable continued performance, they may carry longer-term risks. Lin similarly noted that passive coping can temporarily stabilize psychological states but may yield adverse long-term consequences for health and work functioning.

Participants also indicated that rescue and EMS work often involves immediate shock, but firefighters must rapidly regain composure to complete tasks according to standard procedures. This aligns with evidence that firefighters cope by focusing on the task and maintaining calm during operations. It also echoes Yeh’s observation that firefighters often lack time and space to process emotions during missions and must temporarily set aside feelings until tasks are completed. However, in the present study, novices did not clearly report structured post-mission emotional processing; instead, they tended to rely on compartmentalization, suppression, or redirection of attention. This suggests that novice firefighters may have limited awareness of cumulative trauma risks and may underestimate the potential harm of unprocessed emotional and psychological impact. If distress is repeatedly ignored, cumulative strain may contribute to psychological depletion, emotional exhaustion, intrusive re- experiencing, and triggered recall, with trauma-related symptoms becoming more pronounced over time.

Although participants were aware that fire agencies provide mental health services (including counseling), they tended to perceive such services as offering only temporary emotional relief and limited practical utility for problem solving. They also reported concerns about privacy and the confidentiality of counseling records, which reduced willingness to seek help. These findings imply that existing governmental and organizational mental health resources may not fully match novice firefighters’ needs. Importantly, participants’ skepticism was not solely attitudinal; it reflected a perception that counseling cannot resolve structural sources of distress (e.g., authoritarian supervision, institutional injustice, and equipment/resource deficits). Thus, improving service uptake likely requires both strengthened confidentiality safeguards and organizational reforms that address upstream stressors and demonstrate institutional accountability.

In summary, the findings indicate that novice firefighters’ job demands arise not only from the inherent danger of frontline tasks, but also from organizational oppression and institutional injustice— manifested as hierarchical pressure, workplace bullying, and opaque managerial practices—combined with structural resource deficits (e.g., shortages of supplies, malfunctioning systems, and insufficient interpersonal support). Under such conditions, personal coping and adaptation may help individuals maintain day-to-day functioning but remain insufficient to compensate for systemic problems. Novice firefighters in this study appeared to operate in a structural imbalance in which demands substantially exceeded available resources, highlighting the need for multi-level interventions that extend beyond individual resilience.

Implications

Fire service organizations should prioritize novice development by ensuring reasonable work allocation and adequate resources, supported by a constructive work environment, healthy organizational culture, and fair performance evaluation systems. Providing sufficient equipment and accessible psychological resources may foster a more supportive workplace and reduce the risk of work-related psychological harm. More specifically, leaders and supervisors should establish transparent and equitable assessment mechanisms, acknowledge and address resource shortages, and ensure stable provision of emergency medical supplies and other essential materials. Institutional protections for novice personnel should be strengthened to prevent unfair or oppressive treatment arising from hierarchical differences. Supervisors should proactively attend to novices’ needs and shift their role from “monitor” to a buffering resource—providing guidance on professional values, emotional support, and tangible resources, and helping novices navigate supports for processing distress and potential trauma-related reactions. Future research may examine the effectiveness of different coping strategies in response to specific challenges (e.g., hierarchical oppression and ethical dilemmas) and investigate how organizational resources and culture shape novice firefighters’ adjustment over time.

Conclusion

Within highly hierarchical fire service organizations, novice firefighters may experience a structural pattern of high demands and low resources, including hierarchical pressure, institutional injustice, resource scarcity, prolonged high-risk work, and compensation perceived as disproportionate to workload and risk. Despite these conditions, novice firefighters strive to adapt and often demonstrate resilience and commitment to professional practice. However, they primarily rely on individual coping strategies—such as emotional suppression, compartmentalization, and attentional redirection— to manage stress and emotional reactions, strategies that may carry hidden risks of long-term psychological depletion and escalation of trauma-related symptoms. Accordingly, supporting novice firefighters’ sustainable adaptation requires coordinated efforts that combine individual- and peer-level supports with organizational reforms in leadership practices, procedural justice, resource provision, and the design and credibility of mental health services.

References

  1. National Fire Agency (2024) Manpower in Fire Agency. Report from National Fire Agency, Ministry of the Interior, Taiwan.
  2. National Fire Agency (2018) Manpower supplementation in Fire Report from National Fire Agency, Ministry of the Interior, Taiwan.
  3. Chang CM (2009) A study on occupational safety and health management of firefighters-An example of Taipei National Chiao Tung University.
  4. Kuo NC (2014) The study of work stress turnover intension job satisfaction emotion regulation- for example of fire-fighter. I-Shou University.
  5. Yeh TC (2021) Research on mental health of firefighters and psychological impact after rescue disaster: A case study of Yilan County Fire Bureau. Southeast University of Science and Technology.
  6. Kuo CW (2015) A survey study of firefighters’ stress and PTSD. Report from National Fire Agency Ministry of the Interior Taiwan.
  7. Lin CH (2023) The study to explore the vicarious trauma experiences and mental adjustment process of polices and firefighters participated in the disaster incident. National Taipei University of Education.
  8. Chen, W. H (2001) Stress coping of firefighters. Extinguishing and Protection Monthly 4: 17-24.
  9. Lewis A, Hall TE, Black A (2011) Career stages in wildland firefighting: implications for voice in risky International Journal of Wildland Fire 20: 115-124.
  10. Choudhury NA, Saravanan P (2025) Mapping critical decisions and cues in firefighting: A structured analysis using the critical decision Journal of Cognitive Engineering and Decision Making.
  11. Goh KK, Jou S, Lu ML, Yeh LC, Kao et al (2021) Younger, more senior, and most vulnerable? Interaction effects of age and job seniority on psychological distress and quality of life among firefighters. Psychological Trauma: Theory Research Practice and Policy 13: 56-65. [crossref]
  12. Heydari A, Ostadtaghizadeh A, Ardalan A, Ebadi A, Mohammadfam I.(2022) Exploring the criteria and factors affecting firefighters’ resilience: A qualitative study. Chinese Journal of Traumatology 25: 107-114.
  13. Liao SC (2017) A comparison of perceived stress heart rate variability respiratory function and standing balance in firefighters with different seniority. University of Taipei.
  14. Hsiao TC (2020) Novice firefighters’ task features stressors and stress coping: A team in New Taipei Fo Guang University.
  15. Lin CK (2023) The impact of subordinate voice behavior on subordinate resilience under authoritarian leadership: A case study of firefighters. National Tainan University.
  16. Bakker AB, Demerouti E (2017) Job Demands-resources theory: Taking stock and looking Journal of Occupational Health Psychology 22: 273-285. [crossref]
  17. Demerouti E, Bakker AB, Nachreiner F, Schaufeli WB (2001) The job demands- resources model of Journal of Applied Psychology 86: 499-512. [crossref]
  18. Smith TD, Dyal M (2016) A conceptual safety-oriented job demands and resources model for the fire service. International Journal of Workplace Health Management 9: 443-460.
  19. Payne N, Kinman G (2019) Job demands, resources and work-related well-being in UK firefighters. Occupational Medicine 69: 604-609. [crossref]
  20. Igboanugo S, Bigelow PL, Mielke JG (2021) Health outcomes of psychosocial stress within firefighters: A systematic review of the research Journal of Occupational Health 63: e12219. [crossref]
  21. Wang L, Chen F, Zhang Y, Ye M (2023) Association between social support, and depressive symptoms among firefighters: The mediating role of negative Safety and Health at Work14: 431-437.
  22. Schuhmann B (2022) The assessment of burnout and resilience in firefighters. Nova Southeastern University.
  23. Eryılmaz İ, Dirik D, Öney T (2024) A phenomenological study on psychological resilience of aircraft rescue and fire fighting professionals. Current Psychology 43: 20286-20308.
  24. Carver CS, Scheier MF, Weintraub JK (1989) Assessing coping strategies: a theoretically based Journal of Personality and Social Psychology 56: 267-83. [crossref]
  25. Chung YY, Chiou JJ (2013) The relationships of post-traumatic stress disorder and coping behavior among first-line firefighters. Journal of Crisis Management 10: 69-78.
  26. Lee SF (2012) The study of the strikes and learning needs facing death events for firefighters in Chiayi County. National Chung Cheng University.
  27. Chen TY (2019) A narrative analysis about pressure adjustment of rescuers participating in major disasters: A case study of firefighters. National Taina University.
  28. Hsu CW (2022) A Study of work stress and the needs of psychological counseling system of firefighters-Taking the Fire Department of New Taipei City as an example. Ming Chuan University.
  29. Blaney L, Brunsden V (2015) Resilience and health promotion in high-risk professions: A pilot study of firefighters in Canada and the United International Journal of Interdisciplinary Organizational Studies 10: 23-32.
  30. Paterson C, Leduc C, Maxwell M, Aust B, Amann et al (2021) Evidence for implementation of interventions to promote mental health in the workplace: a systematic scoping review protocol. Systematic Reviews10: 41. [crossref]
  31. Ogińska-Bulik N, Kobylarczyk M (2016) Association between resiliency and posttraumatic growth in firefighters: The role of stress International Journal of Occupational Safety and Ergonomics 22: 40-48. [crossref]
  32. Gao PT (2025) A narrative study on the resilience of frontline firefighters: Experiences from disaster and emergency response. National Changhua University.
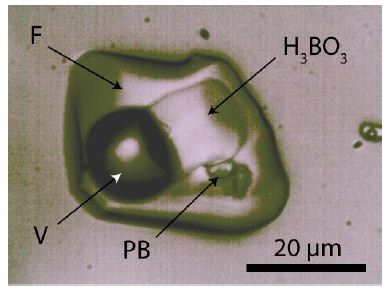
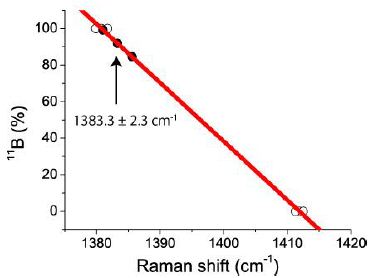
The Development of Oppositional Defiant Disorder(ODD) in Youth: A Review of Risk, Protective, and Ameliorating Factors

DOI: 10.31038/PSYJ.2025763

Abstract

Oppositional Defiant Disorder (ODD) is a disruptive behavioral condition characterized by persistent patterns of angry, irritable mood, argumentative behavior, and vindictiveness (APA, 2022). This comprehensive review explores the diagnostic criteria, prevalence, and developmental trajectory of ODD in youth, with a focus on the interplay of risk, protective, and ameliorating factors. The article examines the distinctions between medical and educational diagnoses, including the implications of DSM-5-TR and special education law in the United States (IDEIA). It highlights the disorder’s comorbidity with ADHD, mood disorders, and conduct disorder, and discusses how cultural, gender, and socioeconomic factors influence diagnosis and symptom presentation. The review also delves into dispositional, genetic, cognitive, neurobiological, and environmental risk factors, emphasizing the importance of early intervention and strong familial and peer relationships as protective mechanisms. Evidence-based treatments are presented as effective strategies for managing ODD symptoms. The article underscores the critical role of educators and psychologists in identifying, evaluating, and supporting students with ODD through informed assessment and intervention practices.

Oppositional Defiant Disorder

Oppositional Defiant Disorder (ODD) is a complex externalizing behavioral condition characterized by persistent patterns of angry or irritable mood, argumentative and defiant behavior, and vindictiveness in children and adolescents [1]. Understanding ODD requires a comprehensive, multidisciplinary approach that considers its diagnostic criteria, prevalence, and developmental trajectory, as well as the interplay of dispositional, genetic, cognitive, neurobiological, and environmental risk factors. In clinical settings, psychiatrists and licensed psychologists typically provide a medical diagnosis of ODD, while in educational contexts, school psychologists, particularly those trained in clinical assessment and diagnostic frameworks, are responsible for evaluating students for special education eligibility under the classification of emotional disability (ED) [2]. This review will provide a comprehensive overview of ODD and present the developmental trajectory of risk and protective factors for youth with ODD. The article will also explore the distinctions between medical and educational diagnoses, with particular attention to the implications of DSM-5-TR criteria and special education law in the United States (IDEIA). The article will examine how comorbid conditions such as ADHD, mood disorders, and conduct disorder complicate both identification and intervention. Additionally, it will highlight how cultural, gender, and socioeconomic factors influence symptom presentation and diagnostic outcomes, and provide a review of effective early intervention and evidence-based treatments, such as Parent-Child Interaction Therapy (PCIT) and Teacher-Child Interaction Training (TCIT), in equipping educators and psychologists to support youth with ODD effectively.

Overview of ODD

Diagnostic Features and Criteria

Oppositional Defiant Disorder (ODD) poses distinct challenges across both healthcare and educational systems. In clinical settings, professionals use standardized diagnostic tools to identify and manage the disorder. In contrast, educators must assess whether a student’s behavioral patterns meet the criteria for special education services. It’s important to distinguish between a clinical diagnosis and an educational classification: the DSM-5-TR provides the framework for diagnosing ODD in medical contexts, while eligibility for school- based support is determined by federal legislation such as the Youth with Disabilities Education Improvement Act (IDEIA) and state- specific guidelines like Indiana’s Article 7. Together, these systems help ensure that children with ODD receive comprehensive support that addresses both their behavioral health and academic needs.

DSM-5-TR

According to DSM-5-TR, ODD is characterized by a persistent pattern of angry/irritable mood, argumentative/defiant behavior, or vindictiveness lasting at least six months (APA, 2022). Diagnosis requires the presence of at least four symptoms from these categories, exhibited during interactions with at least one individual who is not a sibling). Regarding angry/irritable mood, an individual may experience symptoms where they often lose their temper, are touchy or easily annoyed, and/or are often angry and resentful. An individual may also experience symptoms of argumentative/defiant behavior where they often argue with authority figures, defy or refuse to comply with requests from authority figures or with rules, deliberately annoy others, and/or often blame others for their mistakes or misbehavior. The individual may have also been spiteful or vindictive at least twice within the past six months. The disturbance in behavior must be negatively impacting their social, educational, occupational, or other important areas of functioning, and the behaviors cannot be better explained by other mental health conditions (e.g., psychotic, substance use, depressive, or bipolar disorder). Finally, the DSM-5-TR includes three specifiers: mild (symptoms are confined to one setting); moderate (symptoms are present in at least two settings); and severe (symptoms are present in three or more settings).

IDEIA and State Laws

Youth with ODD, and disruptive behaviors, are often considered for special education services under the classification of Emotional Disorder (ED). IDEIA, the federal law that governs special education in the United States, broadly defines ED as a condition that exhibits at least one of the provided characteristics for a long period of time and to a marked degree that adversely affects a child’s educational performance [3]. Characteristics include: an inability to learn that cannot be explained by intellectual, sensory, or health factors; an inability to build or maintain satisfactory interpersonal relationships with peers and teachers; inappropriate types of behavior or feelings under normal circumstances; a general pervasive mood of unhappiness or depression; and/or a tendency to develop physical symptoms or fears associated with personal or school problems. While IDEIA provides a general overview of ED, it does not provide guidelines for how to evaluate the category.

Although IDEIA outlines the general criteria for ED, it does not provide detailed procedures for how to assess or determine eligibility. Each state in America is responsible for developing its own evaluation standards. For instance, in the state of Indiana, Article 7 serves as the state’s special education framework and builds upon the federal definition by adding further clarification. Indiana’s criteria include episodes of psychosis and emphasize the need for a comprehensive evaluation process. This process must include assessments of academic achievement and emotional functioning, a thorough developmental and social history, a functional behavior assessment, and relevant medical or psychological information. The goal is to ensure that the student’s learning challenges are not better explained by other factors such as cognitive or sensory impairments [4].

Prevalence

While there are limited population- or national-level data on the prevalence of Oppositional Defiant Disorder (ODD) in the United States, current estimates suggest a prevalence rate of approximately 3.3%, with most community samples ranging from 3% to 6% [5]. This variability may be influenced by differences in diagnostic practices, sample demographics, and access to mental health services across regions. Boys are slightly more likely than girls to develop and be diagnosed with ODD during childhood, possibly due to more overt behavioral symptoms that draw attention in educational and clinical settings. However, research indicates that gender differences in prevalence tend to diminish during adolescence and adulthood, with similar rates observed across sexes. These findings highlight the importance of early identification and culturally sensitive assessment practices to ensure accurate diagnosis and appropriate intervention.

Comorbidity

Youth with ODD are at risk of having internalizing and externalizing comorbidity. Youth with ODD have higher rates of comorbidity with attention deficit hyperactivity disorder (ADHD) and mood and anxiety disorders [6,7]. Youth who develop ODD during childhood and adolescence are at an increased risk for developing conduct disorder (CD) and/or antisocial personality disorder (APD). There is also evidence of comorbidity between posttraumatic stress disorder (PTSD) and ODD [8]. Youth with ODD are also more likely to use tobacco, alcohol, and drugs [9].

Factors Associated with ODD

Cultural Factors

Cultural differences in the diagnosis of Oppositional Defiant Disorder (ODD) may stem from misdiagnosis or overdiagnosis among youth from marginalized backgrounds. African American youth, for example, have been reported to exhibit higher rates of defiant behaviors and conduct problems in some research samples [10,11]. In special education settings, Black males are disproportionately identified as having Emotional Disturbance (ED), often due to elevated reports of behavioral concerns compared to their white peers—even when the actual intensity and frequency of behaviors are similar across racial groups. This overrepresentation may reflect systemic biases in behavioral interpretation and referral practices rather than true differences in symptom severity. As a result, culturally responsive assessment and intervention practices are essential to ensure accurate identification and equitable support for students with behavioral challenges.

Gender Differences

While the prevalence of ODD is similar among boys and girls during adolescence and adulthood, boys and girls may present differently in symptomology, severity, and associated comorbidity [12]. Boys may be found to experience symptoms that include annoying others, blaming others, being aggressive, and they may present with greater functional impairments at school and in the community than girls. Girls may demonstrate less observable oppositional characteristics, including more relational aggression (e.g., refusing to talk to someone, being malicious, avoiding blaming, spreading rumors, attempting to harm someone’s relationships with others, etc.). Additionally, boys may be more likely to have externalizing comorbidity (e.g., ADHD) while girls may be more likely to have internalizing comorbidity due to significantly diminished self-regulation skills compared to boys with ODD (e.g., anxiety, depression, and somatic complaints) [13].

Socioeconomic Differences

Children and adolescents from low-income households are more frequently identified as exhibiting symptoms associated with Oppositional Defiant Disorder (ODD) [14]. Environmental stressors common in economically disadvantaged neighborhoods, such as exposure to community violence, can contribute to the development or intensification of oppositional behaviors. Limited access to mental health resources and safe recreational spaces may further exacerbate these challenges. Additionally, lower levels of parental education are often linked to inconsistent or harsh disciplinary practices, which can influence the emergence of ODD symptoms. Factors such as food insecurity, chronic stress, and reduced access to supportive peer networks also play a role in shaping behavioral outcomes in these populations.

Developmental Pathway of ODD

Overview of Developmental Course

The first symptoms of ODD are typically present as early as preschool but rarely later than early adolescence. If left untreated, the severity of the symptoms could gradually escalate to the development of Conduct Disorder (CD) and even to the severity level of Anti-social Personality Disorder (APD) [15]. A typical developmental progression of disruptive behavior may begin with severe hyperactivity and impulsivity in early childhood, followed by the emergence of ODD symptoms during the preschool years. As the child enters elementary school, these behaviors may intensify and evolve into conduct disorder. During adolescence, the individual may begin to engage in substance- related issues, and if left untreated, these patterns can culminate in antisocial personality disorder in adulthood. Children and adolescents with ODD may experience a variety of problems in adulthood, including relational problems, lower educational attainment, and workplace stress. School psychologists and other providers should be familiar with the risk factors and the developmental trajectory of ODD when evaluating and designing interventions for students with ODD.

Dispositional Risk Factors

Emotional/Temperamental Factors

Numerous emotional risk factors have been associated with the development of ODD. Children who experience difficulties regulating their emotions are more likely to exhibit irritability and vindictiveness [16]. For example, children who have higher levels of emotional reactivity and/or have a low frustration tolerance are at risk for developing ODD. Children and adolescents who have low self-control due to ADHD may also possess issues with emotional regulation making them vulnerable to developing comorbid ODD. Callous-unemotional traits (CU), a cluster of traits of psychopathic youth that include a lack of empathy and indifference toward the feelings of others, have been seen in children and adolescents whose ODD symptoms begin to exacerbate to CD or APD. Youth who have CU traits likely have characteristics of neuroticism that cause them to demonstrate lower levels of fear and anxiety – also increasing the likelihood of their symptoms exacerbating.

Genetic Factors

The heritability estimate for ODD is around 50%. Significant levels of CU traits may be a result of genetic influences (e.g., excess methylation in the OXTR gene predisposes adolescents to CU) [17]. AVPR1A, a gene located on chromosome 2 that plays a significant role in social behavior and interaction, may be associated with aggression in early and middle childhood. Epigenetic research demonstrates that both environmental influences and additive genetic effects, where multiple genes contribute to a single trait, may be involved in the development of Oppositional Defiant Disorder (ODD). Through gene-environment interactions, environmental exposures can either enhance or suppress the expression of genetic predispositions, thereby influencing the likelihood that ODD-related traits will manifest.

Cognitive Vulnerabilities

Youth with ODD may show cognitive deficits in executive functioning (EF) and low verbal intelligence, especially if they possess CU traits. The classification of EF into ‘hot’ and ‘cool’ is a critical element of etiopathological research on externalizing disorders. “Hot” EF involves affective, motivational, and emotional aspects of cognition, whereas “cool” EF focuses on planning, cognitive flexibility, working memory, and inhibition. Children with ODD may have characteristics of greater reward-seeking behaviors and problems with emotional self-control [18]. Regarding “cool” EF, children with ODD have lower behavioral inhibition, which mixed with poor emotional control may exacerbate impulse aggression. School-referred children with disruptive behavior symptoms are associated with poor motivational and cognitive control (also referred to as executive control), and they may be incapable of cognitively processing the negative consequences of their victim’s distress.

Neurobiological Factors

Children with ODD may have neurobiological abnormalities in the amygdala and prefrontal cortex – areas responsible for reasoning, judgment, impulsecontrol, andemotionalprocessing. Morespecifically, reduction in the left amygdala, anterior insula, frontal gyrus, cingulate cortex, and/or medial prefrontal cortex might be associated with ODD. Brain regions such as the amygdala, anterior cingulate cortex, insula, and orbitofrontal cortex are primarily involved in emotional or “hot” executive functions, while the dorsolateral prefrontal cortex and cerebellum are more associated with logical, “cool” executive functions and areas, such as the precuneus, control both types of functioning. Additionally, heart rate, serotonin levels, and basal cortisol levels are often reduced in adolescents with aggressive behaviors.

Environmental Risk Factors

Familial Factors

A variety of family risk factors, including low socioeconomic status (SES), parental separation, and maternal depression, have been associated with the development of ODD. Aside from parental pathology, other family factors that could lead to symptoms of childhood/adolescent-onset of ODD include exposure to poor disciplinary practices (e.g., forms of hostility or aggression), maltreatment and neglect (e.g., sexual, physical, or psychological abuse), single parenthood, and family disharmony (e.g., argumentative parents). A combination of surrounding oneself with deviant peers and having poor parental supervision with low involvement are predictors for adolescents to engage in rebellious and/or defiant behaviors. Children who are exposed to high levels of dysfunctional parenting and maternal depression are also at a higher risk of developing symptoms of defiant and antisocial behaviors. Finally, children who are frequently emotionally dysregulated are at risk of experiencing higher child-parent conflict that could enhance ODD symptomology.

Interpersonal Vulnerabilities

Children and adolescents often face a range of interpersonal challenges, particularly when it comes to initiating and sustaining positive relationships with peers. Those who are consistently rejected by their peers—such as being disliked or excluded—and those who associate with deviant or antisocial peer groups are at increased risk for developing oppositional defiant disorder (ODD). In some cases, youth with ODD may engage in bullying behaviors themselves, contributing to a hostile social environment. However, these individuals may also be targets of bullying, which can intensify symptoms of vindictiveness, especially when they feel compelled to retaliate against those who have harmed them. This cycle of aggression and retaliation can further complicate their social interactions and emotional regulation, reinforcing the behavioral patterns associated with ODD.

Early Adverse Experience

There is a relationship between childhood externalizing problems, including ODD, and exposure to traumatic events. Interpersonal trauma, referring to harmful experiences directly inflicted by another person (e.g., physical abuse, emotional neglect, witnessing domestic violence, etc.), and non-interpersonal trauma, referring to events not involving direct human interaction (e.g., severe accident, natural disaster, loss of a loved one, etc.), are predictive of ODD symptomology in boys, while only interpersonal trauma is a predictor in girls. Children who experience interpersonal trauma are more likely to develop problems with anger, emotional regulation, and disruptive behavior. Children and adolescents who are exposed to community violence in impoverished neighborhoods have an increased risk of developing antisocial attitudes and behaviors.

Protective Factors

There are a variety of protective factors that reduce the likelihood of developing or worsening symptoms of Oppositional Defiant Disorder (ODD). Early intervention is especially important, as it can prevent ODD symptoms from escalating into more severe conditions such as Conduct Disorder (CD) or Antisocial Personality Disorder (APD). One key protective factor is the presence of high-quality relationships, both within the family and among peers. These relationships are often supported by living in safe neighborhoods, having strong family support systems, and being surrounded by prosocial peers who model positive behavior. Additionally, strong executive functioning and emotional regulation skills serve as internal protective mechanisms that help children manage impulses and navigate social challenges more effectively.

Treatment of ODD

Clinical Treatment

Because parental factors are highly associated with ODD, clinical treatments should consider strengthening the relationships between caregivers and their children. Parent-Child Interaction Therapy (PCIT) is an evidence-based therapeutic technique originally developed for children with disruptive behaviors that focuses on strengthening familial relationships by altering parent-child interactions [19]. PCIT involves having a parent and child together in a playroom while a therapist remains on the other side of a one-sided mirror where they coach the parent (by talking to them through a headset of some form) on how to positively interact and build a healthy rapport with their child. This verbal rapport is typically developed through praise, positive reinforcement, and overall parental involvement by the parent. If implemented with fidelity, PCIT is an effective treatment for decreasing ODD symptoms and preventing the development of CD by helping parents quit certain behaviors (e.g., unhealthy discipline responses) while starting other behaviors (e.g., more parental involvement) [20].

School Intervention

Similarly, school psychologists who possess the appropriate training should consider facilitating Teacher-Child Interaction Training (TCIT) with the teacher and student. In general, TCIT is a “classroom-based program designed to provide teachers with behavior management skills that foster positive teacher-student relations and to improve student behavior by creating a more constructive classroom environment” [21]. In general, there are teaching sessions that encompass learning about positive reinforcement through praise, modeling, and various classroom management strategies to decrease disruptive behaviors [22,23]. These sessions typically involve the clinician, teacher, and child, and it may also require the teacher to practice their skills in small and large group settings.

Conclusion

This review article explored Oppositional Defiant Disorder (ODD) in youth, emphasizing its diagnostic criteria, prevalence, developmental trajectory, and associated risk and protective factors. The article distinguishes between clinical and educational diagnoses in the United States, highlighting the roles of DSM-5- TR and IDEIA in shaping assessment and intervention practices. It identifies a range of dispositional, genetic, cognitive, neurobiological, and environmental risk factors that contribute to the onset and progression of ODD, while also underscoring the importance of early intervention and facilitating strong interpersonal relationships as protective mechanisms. Evidence-based treatments such as Parent- Child Interaction Therapy (PCIT) and Teacher-Child Interaction Training (TCIT) are presented as effective strategies for managing symptoms and preventing escalation into more severe disorders like Conduct Disorder (CD) or Antisocial Personality Disorder (APD). Psychologists, therapists, and educators should possess a deep understanding of the psychopathology underlying Oppositional Defiant Disorder (ODD) and be equipped with evidence-based strategies to support affected students. This includes conducting informed evaluations, implementing targeted interventions, and fostering collaborative efforts among school staff and families to address behavioral and emotional challenges effectively.

References

  1. American Psychiatric Association [APA]. (2022) Disruptive, impulse-control, and conduct disorders.
  2. Tobin RM,House (2016) DSM-5 diagnosis in the schools. The Guilford Press
  3. S. Department of Education. (2004) Youth with Disabilities Education Act.
  4. Indiana State Board of (2024) Special Education Rules. Article 7.
  5. Aggarwal A,Marwaha (2024) Oppositional defiant disorder. StatPearls – NCBI Bookshelf.
  6. Boat TF, Wu J T, Disorders T. E. T. S. S. I. D. P. F. C. W. M., Families, B. O. C. Y. A., &Education, D. O. B. a. S. S. A. (2015) Prevalence of oppositional defiant disorder and conduct disorder. Mental Disorders and Disabilities Among Low-Income Children – NCBI
  7. Halldorsdottir T, Fraire MG, Drabick, D AG, Ollendick TH. (2023) Co-occurring conduct problems and anxiety: Implications for the functioning and treatment of youth with oppositional defiant disorder. International Journal of Environmental Research and Public Health 20: 3405
  8. Mikolajewski AJ,Scheeringa MS. (2022) Links between Oppositional Defiant Disorder Dimensions, Psychophysiology, and Interpersonal versus Non-interpersonal Trauma. Journal of psychopathology and behavioral assessment 44: 261-275.
  9. Leadbeater BJ, Merrin GJ, Contreras A,Ames (2023) Trajectories of oppositional defiant disorder severity from adolescence to young adulthood and substance use, mental health, and behavioral problems. Journal of the Canadian Academy of Child and Adolescent Psychiatry 32: 224-235
  10. Mash EJ,Barkley (Eds.) (2014) Child psychopathology (3rd ed.) New York: Guilford Press. (ISBN: 978-1-4625-1668-1)
  11. Lambert MC, Katsiyannis A, Epstein MH,Cullinan D. (2022) An Initial Study of the Emotional and Behavioral Characteristics of Black Students School Identified as Emotionally Disturbed. Behavioral Disorders 47: 108 117.
  12. Trepat E, Ezpeleta (2011) Sex differences in oppositional defiant disorder. Psicothema 23: 666–671.
  13. Zhang W, Qiao L, Wang M, Liu Z, Chi P.et al.(2025) Bidirectional relation of self- regulation with oppositional defiant disorder symptom networks and moderating role of gender. Development and Psychopathology 37: 1616–1627.
  14. Hawes DJ, Gardner F, Dadds MR, Frick PJ, Kimonis ER, et (2023) Oppositional defiant disorder. Nature Reviews Disease Primers 9: 31.
  15. Steinberg (2022) Psychosocial problems in adolescence. In Adolescence . New York, NY: McGraw-Hill
  16. Nobakht HN, Steinsbekk S,Wichstrøm (2024), Development of symptoms of oppositional defiant disorder from preschool to adolescence: the role of bullying victimization and emotion regulation. Journal of Child Psychiatry 65: 343-353
  17. Ghosh A, Ray A, Basu (2017) Oppositional defiant disorder: current insight. Psychol Res Behav Manag,10: 353-367
  18. Anning KL, Langley K, Hobson C, et (2024) Cool and hot executive function problems in young children: linking self-regulation processes to emerging clinical symptoms. European Child and Adolescent Psychiatry 33: 2705-2718.
  19. Bjørseth Å,Wichstrøm (2016) Effectiveness of Parent-Child Interaction Therapy (PCIT) in the Treatment of Young Children’s Behavior Problems. A Randomized Controlled Study. PloS one 11: e0159845.
  20. Fooladvand M, Nadi MA, Abedi A,Sajjadian (2021) Parenting styles for children with oppositional defiant disorder: Scope review. Journal of education and health promotion 10: 21
  21. Fernandez MA, Adelstein JS, Miller SP, Areizaga MJ, Gold DC, et (2015) Teacher- Child Interaction Training: A Pilot Study with Random Assignment. Behavior Therapy 46: 463-477.
  22. Stankus, Jaclynn S, Jancart Karl L,McGoey, Kara (2022) “The Effect of Teacher- Child Interaction Training (TCIT) on Children who are Exhibiting Disruptive Behaviors within the Classroom Setting,” Perspectives on Early Childhood Psychology and Education.6: 2.
  23. Barker C, de Lugt (2022) A review of evidence-based practices to support students with oppositional defiant disorder in classroom settings. International Journal of Special Education 37: 85-98.

Talking to Patients: Part 2 – Mind Genomics Cartography of Reactions to Messages Pertaining to Patient Experience with COVID-19

DOI: 10.31038/MGSPE.2025523

Abstract

In a Mind Genomics experiment, 101 respondents each evaluated unique sets of 24 vignettes pertaining to interactions with a medical professional concerning the personal experience with COVID-19. The focus was to determine which messages made the respondents feel “comfortable” communicating. The results suggest two clearly different mind-sets, those responsive and comfortable with communication about the “facts” of COVID-19, versus those comfortable with communication about emotional support of the patient. These two mind-sets transcend gender, age, and previous experience with COVID-19. A simulation of the same topic by AI revealed that AI picked up these two mind-sets but suggested even deeper subgroups within each mind-set. The paper shows the value of incorporating Mind Genomics and AI into the education of medical professionals to provide deeper knowledge of how to communicate with patients.

Keywords

Artificial Intelligence, COVID-19, Empathy in healthcare, Medical education, Mind Genomics, Patient communication

Introduction

Healthcare professionals can improve their communication skills with patients by actively listening, demonstrating empathy, using clear language, and adopting a patient-centered approach. By involving patients in decision-making processes, providing comprehensive information, and collaborating on treatment decisions, healthcare providers can build trust and rapport. Measurement of communication strategies can be done through patient surveys, feedback forms, focus groups, and patient outcomes data. Common barriers to effective communication include time constraints, language barriers, cultural differences, health literacy limitations, and emotional or psychological challenges. Addressing these barriers can lead to more effective patient-provider interactions and improved health outcomes.

Mind Genomics is an emerging science that studies how people behave and respond to different messages on important topics, such as COVID. This method helps experts understand what people like or dislike about certain messages and how they react in various situations. By using AI, healthcare workers can create personalized texts about COVID in the Mind Genomics app to see how comfortable patients are with them. This approach is based on facts and aims to help healthcare workers establish deeper connections and have more effective conversations with their patients.

Mind Genomics differentiates itself from standard consumer research techniques by taking a unique approach to gathering insights on consumer preferences. Instead of asking respondents to directly rate the importance of various aspects, Mind Genomics presents them with combinations of messages and analyzes their responses to determine the impact of each message. This method avoids forcing people to intellectualize and allows for a more natural, intuitive understanding of consumer preferences. Using statistical techniques such as regression modeling, Mind Genomics identifies which messages most strongly communicate the desired messages. The pattern of strong performing messages provides insights on consumer behavior and preferences, doing so in a fashion which is robust, rapid, and designed for exploration in areas that may be as yet “terra incognita,” viz., unknown lands. This approach not only improves patient satisfaction but also makes training medical professionals more effective by giving them real-world feedback on their messaging strategies.

Mind Genomics has been used in topic areas ranging from medicine (focus of the current paper), to food, law, social issues, and matters of the everyday). The methods have been explicated in a variety of papers [1-6]. This paper adds to the corpus of knowledge created by Mind Genomics, doing so with the focus on COVID, and specifically on the communication between patient and medical professional, e.g., doctor or nurse practitioner.

Step 1: Create the Raw Materials

The Mind Genomics technique asks the user to provide four questions, each with four answers. The four questions and four answers to each question were developed using AI, as discussed in the accompanying paper. Table 1 shows the four questions and four answers to each question (elements), generated by AI, but edited by the researchers to make the answers succinct and easy to understand. For each question and each answer, the AI was instructed to make the text 15 words or less, to write in the way people talk, and to make the text understandable to a 12-year-old.

Table 1: The four questions and the four answers to each question.

Step 2: Create the Test Stimuli

The test stimuli consist of message combinations from an experimental design. The experimental design specifies the combinations as follows:

  1. Each element appears five times in 24 vignettes and is absent from 19 vignettes.
  2. A vignette must contain at most one answer to a question.
  3. A vignette must have a minimum of two elements and a maximum of four This requirement means that in some cases a vignette does not have an element (answer) from one of the four questions, and in some other cases a vignette does not have an element from two or the four questions. This approach ensures that vignettes do not contain contradictory information from the same question.
  4. The 16 elements appear independently, enabling OLS regression to assess the strength of each element in driving the response.
  5. Each respondent assesses a distinct set of 24 A permutation scheme ensures uniqueness while preserving the mathematical properties of the experimental design, altering only the combinations. This leads to greater coverage of potential combinations. The permutation scheme allows research to explore various ideas and combinations, rather than relying on prior knowledge of what will work best. This shift from experimental confirmation to exploration is central to the Mind Genomics perspective [7].

Step 3: Execute the Study

Mind Genomics studies are conducted online through the BimiLeap.com platform. Luc.id, now Cint, supplies respondents based on user specifications. Participants were adults aged 25-54 living in the United States. Email invitations were sent to the respondents. Participants were directed to an orientation page about the study. The study was not labeled that way. The respondents were informed they would read a set of phrases and rate them as a single idea.

The orientation began with a self-profiling questionnaire that collected the respondent’s age and gender, followed by their answers to seven profile questions in Table 2. BimiLeap.com uses this information to form subgroups of respondents based on their self-identification.

Table 2: Self-profiling questions for classification questionnaire (top) and rating scale for the 24 vignettes (bottom).

The respondents did not receive extensive orientation. The goal was to show them the vignettes and capture their immediate reactions, without creating any expectations. This brief introduction is typical for most Mind Genomics studies, except those related to the law, where case background is pertinent. A brief introduction will suffice for most issues.

Step 4: Create the Database and Estimate the Regression Equation for the Total Panel

Each respondent assessed a unique set of 24 vignettes in random order. The respondent initially assessed vignette #1 as a training vignette. The rating for the first vignette was discarded. The respondent assessed all 24 vignettes. The 24th vignette was a repeat of the training vignette.

The respondent scored the vignette on a 5-point scale. The analysis focused on ratings 4 and 5, which indicate “patient feels comfortable with what the patient has heard.” They were transformed into a new binary variable, R54x. When the respondent rates a vignette a 4 or 5, R54x become 100. When the respondent rates a vignette 3, 2, or 1, R54x become 0. As a prophylactic measure to ensure some variation in the binary variable R54x (necessary for regression analysis) a tiny random number (<10-5) was added to the new binary variable.

The Mind Genomics platform recorded both the rating that the respondent assigned, then the transformed value (R54x), as well as the response time. The response time was the number of seconds (to the nearest 100th second) elapsing between the time the vignette appeared on the screen to the time that the respondent assigned a rating. Response times of 8 seconds or longer were automatically transformed to 8 seconds under the assumption that the respondent was multi-tasking.

The platform’s database included 2424 records, one for each vignette per respondent among 101 participants. Each record included a respondent ID, self-profiling data, vignette order in the 24-set, 16 columns for coding element absence, and the rating, response time, and transformed binary rating R54x.

For the OLS regression, the 16 columns for the elements were coded “1” if present in the vignette and “0” if absent. This is known as dummy coding. The coding indicates the predictor’s state: absent (0) or present (1).

The analysis occurs twice: first for groups, then for individuals. Groups are defined by the self-profiling questionnaire. All 24 vignettes from each respondent were compiled for analysis. The analysis involved the OLS regression without an additive constant, represented as: R54x = k1A1 + k2A2 … k16D4

The regression equation shows the impact of each factor. Parallel analyses showed at statistic of about 2.0 corresponding to a coefficient close to 11 in the regression model with an additive constant. The coefficient of 11 in a model or equation is equivalent to a coefficient of about 20 for a model without an additive constant, estimated on the same data. Given the foregoing argument, it appears that one could make an argument for coefficients of 21 or above as show strong performance when the model or equation is estimated without an additive constant

Table 3 presents the model parameters estimated for 101 respondents. Five elements are statistically significant (coefficient > 20), indicating that AI effectively generated strong, inspiring elements. These elements use informal language.

Table 3: Coefficients for the total panel for the equation relating R54x (comfortable) to the elements.

Step 5: Estimate Regression Equations for the Self-defined Subgroups

Recall that at the start of the Mind Genomics session the respondent completed a self-defining questionnaire, shown in Table 2.  The regression analysis for each group comprising 10 or more respondents generates a great deal of data. In order to make the analysis easier, Table 4 (age, gender) and Table 5 (self-defined attitudes and behavior) show only those coefficients of 25 or higher.

Table 4: Coefficients for gender and for age for the equations relating R54x (comfortable) to the elements.

Table 4 shows only four strong performing elements, suggesting that if there are group differences, the groups are probably not defined by gender nor by age. Table 5 shows that the elements “resonate” for the 11 respondents who have defined themselves as having had Long COVID, but otherwise the pattern is once again elusive

Table 5: Coefficients for the four subsets of respondents based on COVID experience for the equation relating R54x (comfortable) to the elements.

Step 6: Create Mind-Sets by K-means Clustering

Variability among individuals derives from the “human condition,” which is the inescapable reality that people differ from each other on issues, even on the same issues of the world of everyday. Perhaps this variation is an intractable inconvenience? That would be acceptable, of course, and dealt with by oversampling people until the real average emerges out of the intractable variation. But what if this variation represents various ways of thinking about things, rather than random differences? What if there are basic distinctions in cognitive patterns that are not always related to a person’s identity or previous experiences?

A recurrent theme in Mind Genomics is that individuals vary in their daily lives but that this variation at the level of the everyday experience can be traced to mind-sets, patterns of thinking. The mind-sets emerge from the world of the granular and are descriptive rather than normative. The mind-sets “make sense” of the variation by showing that the variation can be generated by parsimonious set of groups. Furthermore, these groups are discoverable by simple studies such as the study presented here. Furthermore, one cannot always anticipate how a person would think based on their demographics, or even their actions. As of this writing (Winter 2024-2025), the mind- sets must be retrieved via an examination of reaction patterns to the vignettes. The method is simple: use the individual coefficients from a research, such as ours, to determine what individuals react to in terms of inspiration.

Reducing this tumultuous inter-person variety to well-behaved, explainable, parsimonious number of mind-sets is one way of using clustering—a well-accepted statistical procedure. Clustering reduces a seeming random cloud of different objects into a few interpretable groups, clusters, or mind-sets in the language of Mind Genomics. The processes are strictly mathematical, Mind Genomics uses k-means clustering [8]. People in a cluster think and respond similarly to the elements (viz., feel comfortable with the message as conveyed by the medical professional).

The particular strategy used by k-means clustering follows these simple steps:

  1. Using the data from the 24 vignettes evaluated by one respondent, compute the 16 coefficients which emerge from relating the binary dependent variable, inspire (R54x) to the 16 The equation is the same as that above, viz., R54x = k1A1 + k2A2… k16D4
  2. Although each respondent evaluated a different set of 24 vignettes, the original set-up ensured that each of the 101 respondents would evaluate a proper set of vignettes, permitting regression modeling at the level of the individual respondent.
  3. The result of the analysis is a matrix of 101 rows, one row per respondent, and 16 columns one column for each of the 16 The number in the cell is the coefficient for that respondent for the specific element.
  4. The k-means process computes the “distance,” D, between every pair of respondents, by the expression (1-R). The “R” is the Pearson linear correlation between two sets of When R is 1, the two sets of numbers are perfectly related to each other. In our case, this means that the two respondents react identically to the elements. The distance is 1-1 or 0. In contrast, when the two respondents are opposites, R = -1. The distance is (1- -1) or 2.
  5. The k-means algorithm puts the 101 respondents first into two groups, so that the distances of people in each group are small, but the distances of the two group centroids are large. Then the k-means algorithm does the same thing for three groups, and so forth.
  6. The process is entirely objective.
  7. Once the k means algorithm finishes, we end up with two and then with three We can create the equations for the two groups and then create the equations for the three groups. In each case, we look at the strong performing elements.
  8. The remaining effort moves from objective mathematics to subjective We want to make sure that we have easy- to-interpret clusters (interpretability) and as few clusters as possibility (parsimony)
  9. For this study, two clusters ended up providing the better Three clusters ended up having many of the same elements in common.

Table 6 compares the two mind-sets emerging from the k-means clustering. To make the patterns easier to distinguish, the tables show the very strong performing coefficients (25 and higher) in shade. The choice of a cut-off of 25 was made subjectively, to provide a way to distinguish between these two mind-sets. When we use this cut-off, we end up with Mind-Set 1 feeling comfortable by “information-rich messages,” and Mind-Set 2 feeling comfortable with “emotion-rich messages.”

Table 6: Coefficients of two mind-sets (MS1 of 2, MS 2 of 2) emerging from k-means clustering.

It is important to keep in mind that it would be impossible for the respondents to “game” the system. Each respondent saw 24 vignettes in rapid order, and essentially ended up judging each vignette intuitively. Yet, it is striking how clear the mind-sets are. The results of this study support the “insight productivity” emerging from the seemingly “impossible” Mind Genomics task of judging so many vignettes so rapidly.

Step 7: Estimate the Regression Models Using Response Time as the Dependent Variable

Table 7 shows the estimated number of seconds in the response time attributed to each element. The table shows three columns, one column for Total Panel, and then the two remaining columns for the two mind- sets. Long response times are operationally defined as 1.3 seconds or longer. Short response times are operationally defined as 0.3 seconds or shorter. The data suggests no response times meeting the criteria for “long response times.” The absence of long or short response times suggests a lack of deep interest in the topic of COVID-19 [9,10].

Table 7: Response times attributable to individual elements for the Total Panel and for the two mind-sets.

How AI Summarizes the Two Mind-Sets

After the analysis is completed by the Mind Genomics platform, BimiLeap.com, the program is instructed to review the coefficients for each subgroup and answer a variety of prompts. Those prompts are based on the elements 21 or higher for the subgroup. Table 8 shows how the AI “summarizes” these subgroups.

Table 8: AI summarization of the two mind-sets.

What Would AI Have Uncovered Had It Been Prompted to Look for Mind-Sets?

Our final analysis returns to AI, to determine whether or not AI would have uncovered these mind-sets [11-13]. Table 9 (top) shows the instructions given to the AI. Table 9 (bottom) shows the five different mind-sets emerging from the AI, AI-generated Mind-Sets A and B are similar to the empirical Mind-Set 1, AI-generated Mind-Sets D and E are similar to the empirical Mind-Set 2, and AI-generated Mind-Set C is similar to both empirical mind-sets.

Table 9: Using AI to simulate possible mind-sets in the populations regarding communicating with the patient about COVID-19.

Discussion and Conclusions

Mind Genomics experiments improve medical communication by understanding patient mind-sets and preferences. By analyzing patterns in patient responses to different types of communication, healthcare professionals can tailor their approach to better meet individual needs. This personalized approach can lead to improved patient satisfaction, adherence to treatment plans, and overall health outcomes.

AI can further enhance the understanding of patient communication preferences by analyzing large amounts of data and identifying patterns that may not be immediately apparent to human researchers. By developing a corpus of knowledge based on Mind Genomics experiments, medical students and nurse practitioners can learn about the diverse mind-sets of patients and how to effectively communicate with them. This knowledge can help healthcare professionals provide more personalized care and support ongoing professional development.

The value of Mind Genomics experiments goes beyond improving patient satisfaction; it can also lead to better health outcomes. When patients feel heard, understood, and cared for, they are more likely to follow treatment plans and adhere to medical advice. By analyzing patterns in patient responses to different types of communication, healthcare providers can tailor their communication style to better connect with and engage their patients.

Incorporating the findings of Mind Genomics experiments into training can help young medical professionals develop the communication skills needed to excel in their clinical practice and provide more personalized care to their patients. Empathy plays a crucial role in effective communication between doctors and patients, as it allows them to understand and connect with their emotions, concerns, and perspectives.

Mind Genomics experiments can be used to enhance the communication skills and patient-centered care of organizations. By incorporating these findings into training and practice, healthcare providers can better understand patient communication preferences and tailor their communication strategies to meet their unique needs. This can lead to better patient understanding, adherence to treatment plans, and overall satisfaction with care.

Acknowledgment

The authors gratefully acknowledge the ongoing support and encouragement of Dr. Rizwan Hamid of the Global Healthcare Management Forum in Brooklyn. Dr. Hamid is a continuing source of encouragement for young medical professionals to create a more patient-focused, knowledge-driven healthcare system. The authors are grateful to Vanessa A. and Angela A. for their ongoing help in preparing these and other manuscripts for publication.

References

  1. Moskowitz HR, Porretta S, Silcher M (2008) Concept research in food product design and John Wiley & Sons. [crossref]
  2. Moskowitz HR, Reisner M, Lawlor JB, Deliza R (2009) Packaging research in food product design and development. John Wiley & Sons. [crossref]
  3. Moskowitz HR, Gofman A, Beckley J, Ashman H (2012) Mind Genomics®: A Systematic Consumer Research. InRule Developing Experimentation: A Systematic Approach to Understand & Engineer the Consumer Mind. Bentham Science Publishers. [crossref]
  4. Moskowitz HR, Wren J, Papajorgji P (2020) Mind genomics and the Mauritius: LAP Lambert Academic Publishing. [crossref]
  5. Kornstein B, Rappaport S, Moskowitz H (2023) Communication styles regarding child obesity: investigation of a health and communication issue by a high school student researcher, using mind genomics and artificial intelligence. Mind Genom Stud Psychol Exp. [crossref]
  6. Mendoza CL, Mendoza CI, Braun M, Deitel Y, Rappaport S, et (2023) Empowering Young Researchers: Searching for What to Say to Young People to Avoid Becoming Obese. Endocrinol Diabetes Metab J. [crossref]
  7. Gofman A, Moskowitz H (2010) Isomorphic permuted experimental designs and their application in conjoint Journal of sensory studies. [crossref]
  8. Dubey A, Choubey AP (2017) A systematic review on k-means clustering Int J Sci Res Eng Technol (IJSRET, ISSN 2278–0882). [crossref]
  9. Azuma T, Van Orden GC (1997) Why SAFE is better than FAST: The relatedness of a word’s meanings affects lexical decision Journal of memory and language. [crossref]
  10. Chumbley JI, Balota DA (1984) A word’s meaning affects the decision in lexical Memory & Cognition. [crossref]
  11. Moskowitz HR, Rappaport SD, Saharan S, Wingert S, Anderson T, Mulvey T, Mulvey M (2024) Mind-Sets for Prescription Weight Loss Products That Are Advertised Directly to Consumers: Using Mind Genomics Thinking with AI for Synthesis and Acta Scientific Pharmaceutical Sciences (ISSN: 2581-5423). [crossref]
  12. Viswanathan S, Omidvar-Tehrani B, Renders JM (2022) What is Your Current Mindset?: Categories for a satisficing exploration of mobile point-of-interest InProceedings of the 2022 CHI Conference on Human Factors in Computing Systems. [crossref]
  13. Moskowitz HR, Rappaport SD, Saharan S, Mulvey T. Envisioning the World STEM Teaching Organisation: Combining AI with Mind Genomics to Map a Sustainable InNon-Profit Organisations, Volume III: Society, Sustainability and Accountability 2024 Aug 13 (pp. 151-175) Cham: Springer Nature Switzerland. [crossref]