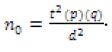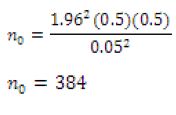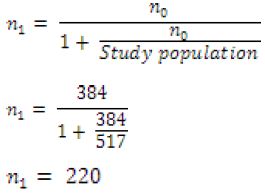Author Archives: admin

Smaller and Small: Strategies to Iterate to Knowledge about the Granular Aspects of Donations

Abstract

The paper presents the use of an emerging science, Mind Genomics, to understand a practical aspect of daily life: what motivates a person to donate to a specific charity. Beyond the knowledge of specific messages which are deemed to be potentially effective as a stimulus to donation, the paper shows how knowledge of a specific end-use can inform us about the mind of a person for a more general problem—how understanding the messages for donation drives a deeper understanding of human motivation. The paper moves from inexpensive pilot tests, through an affordable experiment, and onto the creation of a tool to assign new people worldwide to the proper groups, so they can receive the appropriately targeted messages.

Introduction

Knowing What to Say to Donors to Encourage Giving

In today’s world, departments of development for various organizations have become increasingly important and active. One is inundated daily by requests for donations for all sorts of causes, ranging from simple letters from individuals to sophisticated outreach including brochures and other presentations with information intended to tap one’s emotions and open one’s wallets. Most appeals from organizations appear to be ‘on point,’ with the proper phrases, the proper images, and so forth [1-3].

Approaches to Science – Idiographic versus Nomothetic

Today’s culture of science drives research towards large samples and well-defined stimuli. Despite the fact that a great deal of science is exploratory, the majority of studies published would have us believe that the studies are following the hallowed dicta of philosopher of science Karl Popper, invoking the hypothetico-deductive system, creating a hypothesis, and then falsifying it. The editors of major journals look for breakthrough work, combining a robust combination of novelty and familiarity. Such work is not common, although it occasionally surfaces. The evolving culture of science focuses on extensions of today’s state of knowledge as represented in the existing scientific literature. The typical phrase is ‘plugging holes in the literature,’ or ‘answer a call from the literature.’ Scientific rigor is as much rigorous statistics as rigorous thinking. The published work must convince by virtue of statistical differences, not by daring challenges which advance science. Despite what is promoted as scientific ‘doctrine,’ today’s scientific world frowns upon these new directions, however, when the content of journals and the reactions of reviewers are studied in detail. A quandary arises when the research is meant to explore a topic rigorously with good underlying design but with affordable samples, with the goal to be used for practical ends while truly adding to knowledge of a topic. Can this effort be called science? Typically, these problems emerge in the social and behavioral sciences, but less frequently in the harder sciences.

The focus of this paper is how one can quickly, inexpensively, and rigorously uncover the nature of the donor’s mind for a specific end recipient, that recipient being Children’s Cancer Center (name disguised to preserve confidentiality). The objective is to support children with cancer by addressing their medical, social, and psychological needs, as well as their family’s challenges. The problem is to discover what type of messages are likely to drive a person to donate. The problem is a practical one with a limited scope, specifically Children’s Cancer Center’s donations, but the learning which emerges from the study is relevant to an understanding of other communications driving support for a given charity. The empirical part of this paper shows the two steps followed to discover what to say to potential donors about Children’s Cancer Center. The combination of the two studies may be viewed as a discussion of ‘method,’ so-called methodological research. The specific findings of the second study, which is larger, but still small in terms of general practice, show what can be discovered for practical use.

About Children’s Cancer Center

Data from the World Health Organization (WHO) and the National Cancer Institute reveal that, in the United States, cancer is the leading cause of death by disease past infancy and will lead to the deaths of approximately 1,190 children in the U.S. in 2021. Further, As of January, 2015, the most recent data readily available, The National Cancer Institute reports that there are 429,000 survivors of childhood and adolescent cancer (diagnosed at ages 0 to 19 years) alive in the United States, and these survivors face serious medical problems during and after the acute phase of their disease (National Cancer Institute, 2018, 2020) [4,5].

Childhood cancer is a global issue. According to St. Jude Children’s Research Hospital’s website, cancer is diagnosed each year in about 175,000 children ages 14. The World Health Organization reports that more than 300,000 new cases are diagnosed annually in children ages 0-19. The number of actual cases is probably greater, because children in low-income countries are not likely to be included as part of the count. As Alex’s Lemonade website points out, “globally, cancer stole 11.5 million years of healthy life away from children in 2017.” This is because of life years taken away from kids who die, as opposed to a 90-year-old adult who dies of cancer and has very few life years left (Alex’s Lemonade, 2020) [6].

Despite the global prevalence of childhood cancer and the death rates associated with it, now 80% survival rates for US children but only 20% globally, only 4% of US government funding in the cancer sector is directed towards pediatric cancers. This has been challenged by pediatric cancer activists for years. A 2015 article by Kristin Connor in the Washington Examiner sheds light on the logic behind why our government doesn’t increase funding for childhood cancer:

“…cancer research funds are driven by the number of people — of any age — who have the disease. And, of course, adults, with decades of exposures and behaviors, experience cancer in much greater numbers than young children. This approach therefore seems like the “democratic” way to distribute federal money. Yet it doesn’t do much for the more than 15,700 children diagnosed each year with cancer, and the more than 40,000 children undergoing cancer treatment each year all across the United States. But instead of looking at the number of annual diagnoses, perhaps we should consider the number of life-years potentially saved. For each child with cancer, on average, as many as 71 potential life years might be saved. That’s an important factor that is not being considered when funding allocation decisions are made.” [7].

Despite great progress in US survival rates (84% of children diagnosed with cancer are alive at least five years after diagnosis), 16% are still dying AND those who do survive for five years are not necessarily cured, and many of them suffer from long-term side effects from their illness and associated treatments. According to Alex’s Lemonade, “Children who were treated for cancer are twice as likely to suffer chronic health conditions later in life versus children without a history of cancer.”

Some reason for optimism comes from the WHO: “most childhood cancers can be cured with generic medicines and other forms of treatments including surgery and radiotherapy. Treatment of childhood cancer can be cost-effective in all income settings.” Early intervention is critical to improving pediatric cancer outcomes. The WHO also calls for childhood cancer data systems, which are “needed to drive continuous improvements in the quality of care, and to drive policy decisions.” Donating to organizations like Children’s Cancer Center supports those factors that will lead to improved outcomes around the world. With the WHO’s statement that “the most effective strategy to reduce the burden of cancer in children is to focus on a prompt, correct diagnosis followed by effective therapy,” supporting an organization like Children’s Cancer Center is critical to reducing death rates of children worldwide [8].

The Mind Genomics Approach

Mind Genomics is an emerging science with roots in experimental psychology, sociology, consumer research, and statistics, respectively. The objective of a Mind Genomics study is to understand the messages for a topic which drive a specific response, such as ‘Dislike/Like,’ ‘Not interested/Interested,’ ‘Will Not donate/ will donate,’ ‘Will pay a certain amount,’ ‘expected to feel a certain way,’ and so forth. The purview of Mind Genomics is everyday life and the expected decisions that people make when they are presented with messages about a specific, granular, situation, of the type that would confront them daily. The process of Mind Genomics, the intellectual underpinnings, the statistics, and business-relevant patents have been documented extensively, and need not be repeated in their specifics. The reader is directed to a representative list [9-11]. Mind Genomics grew out of the need to create a new vision of science, one studying the behavior of the everyday, from the viewpoint of experimentation, rather than observation. Anthropology already studied individual cultures and behaviors in depth, with recent efforts attempting to move from purely descriptive to quantitative [12]. Sociology already studies everyday behavior but does not conduct experiments, and looks for general rules in everyday behavior, rules which are ‘nomothetic,’ dealing with generalities. Social psychology moves more closely into the world of the mind but again deals with issues of nomos. Social psychology is not experimental, and while it may deal with ordinary daily behavior, it attempts to provide a broad sweep of the behavior of people, rather than focusing on the topic itself. The topic of the study is only a means to understand the person. In the above disciplines, researchers focus on the person, using the normal situation to understand the person.

In contrast to other disciplines, Mind Genomics focuses on the specifics of the situation, using the person and the rules of judgment to understand. Thus, the learning is about the specifics of daily life, and less so about the person himself or herself. Indeed, one might use the metaphor that Mind Genomics focuses on the situation, with the situation ‘illuminated’ through the lights of different sources. These ‘lights,’ these different forms of illumination, are the people. The ultimate objective of Mind Genomics is to create a ‘Wiki of daily experience,’ a virtual encyclopedia of daily life and the different aspects of that daily life, dimensionalized into specifics, with the data being the aspect and numbers representing the way the ordinary person feels about that specific, on some type of scale. The problem for the ‘project of science’ is what type of information is acceptable for science? That is, the project discussed has a specific objective. Does the fact that there is such an objective invalidate the science, simply because the results pertain to a specific end-user, the Children’s Cancer Center charity? Furthermore, are the results not ‘valid’ because the base size is low? Finally, what is the status of the preparatory study—a small preliminary study to identify whether there are messages which resonate? Do preparatory studies deserve a place in the research report, because they illustrate the way towards making the larger discovery, by one or a set of small, ‘trial’ experiments?

Illustrating the Process of Mind Genomics Applied to Donations

Mind Genomics has already been used to study the nature of effective communication for donations [10,13]. The objective of the study is to understand the most productive and effective way to communicate to a prospective donor to Children’s Cancer Center. The relevance of the topic, donation, and the relevance of Children’s Cancer Center in the world of charity organizations for children with cancer will become obvious from the review of today’s information about children and cancer. Thus, anything helping to understand WHAT to communicate, and to WHOM, can play a major role in the world of health care and fundraising. The ordinary process for understanding what to communicate does not invoke science, nor does it invoke foundational experiments bridging the world of science and application. The ordinary process might be either to select previous messages that ‘worked’ to drive donations, or perhaps to classify the prospective donors into different groups, based upon WHO they are, WHAT they have done in the past, or how they THINK about general topics. The short case presented here shows how a rigorous scientific approach to understand how the mind of the donor can be applied to situations where guidance is needed, rather than where one wishes to establish for a scientific proposition with reasonable certainty. The underlying world view is that even within the world of application, one can create knowledge which informs the greater science. In the case study presented here, we show how a small pair of studies, one with four respondents and a succeeding one with 50 respondents, informs the world of charitable donations, establishing patterns that can used later on as springboards either for more application or for theory building. We now move to the science of Mind Genomics, following the process, not so much to establish general rules, but rather to investigate a specific, defined situation: donation to Children’s Cancer Center Hospital. We follow a series of steps, whether the Mind Genomics study is designed to understand charitable donations in general, or to understand charitable donations to a specific cause.

Our presentation of the process shows the results from two iterations. The first iteration, with the very small base size of four respondents (n=4), will show how Mind Genomics extracts information at virtually the level of one or a few individuals, in a manner similar to the way the anthropologist or the consumer researcher extracts information from in-depth interviews with one or two people or from focus groups of three or more people. The second iteration will move on with a more quantitative study of the responses from 50 individuals, after building on the learning from the first iteration, changing some of the material, and then testing. It is important to note that the process need not be restricted to one small study followed by one larger one, but might comprise several small studies, until these sequences of ‘iterations’ provide the information which seem to be most appropriate to answer the applied question, and to provide the structured knowledge for a ‘wiki of the mind’ with respect to the topic.

Step 1: Choose a Topic

This step sounds simple, but it requires the researcher to focus on a specific topic. Choosing the specific topic is the start of critical thinking required by Mind Genomics, whether the topic is a general one of daily behavior (what makes a person donate to a charity?) or a specific one (what makes a person want to donate to Children’s Cancer Center Hospital?).

Step 2: Create Four Questions Which ‘Tell a Story,’ Pertaining to the Topic

The iterative nature of Mind Genomics ensures that the researcher need not worry that the questions are correct. Indeed, part of the underlying world view of Mind Genomics is that science should be exploratory.

Step 3: Create Four Answers to Each Question

Again, these answers need not be the correct answers. The ability to iterate, to run a number of these small experiments, generate data which guide the researcher to better questions and better answers.

Step 4: Select a Rating Scale

The rating scale can be 5, 7 or 9 points. The actual number of scale points is left to the discretion of the respondents, as is the rating scale. There is no right or wrong scale. The topic of questions and scales has been a focus of researchers for a century. The pragmatic side of Mind Genomics is that the scale should be simple. The scale for this type of question (not donate vs. donate) should be simple to understand, anchored at both ends. An odd number of scale points is easier to work with when there is the possibility of a neutral point.

Step 5: Launch the Study and Get the Results Fully Analyzed within 90 Minutes

The process obtains respondents through a panel service (Luc.id), with the Mind Genomics platform automatically analyzing the data and returning a complete report, the entire process typically taking less than one to one and a half hours.

Step 6: Present the Appropriate Vignettes to the Respondent, Vignettes Created for That Respondent by the Permuted Experimental Design

Record the rating on the anchored 1-9 scale, and record the response time (consideration time), operationally defined as the number of seconds from the appearance of the vignette on the screen to the actual rating assigned by the respondent. Each respondent evaluates the appropriate set of vignettes to constitute an experimental design, allowing subsequent powerful analyses. Each respondent evaluates a unique set of combinations of messages, so that across the set of respondents the evaluations cover many of the possible combinations, rather than covering a few combinations, but with precision. The learning will be in the stimuli, not in the precision of the measurement.

Step 7: Obtain Data Analyzable Both at the Level of the Individual and at the Level of the Group, Respectively

Each respondent evaluates a full experimental design, analyzable at the level of the individual respondent. For the design comprising four questions and four answers (elements), the design prescribes 24 combinations (vignettes). Each vignette comprises 2-4 elements, no more than one element or answer from any question. The design ensures that each element appears 5x, uncorrelated with any other element; The experimental design is maintained, but the combinations are changed according to a permutation scheme [14,15]. Thus, the combinations cover more of the ‘design space’ than the usual approach using experimental design. The underlying rationale is that it is more productive to test many possible combinations with underlying variability (noise) in each measurement than to limit oneself to a few combinations, measuring each point in the design with many replicate measures to average out the variation. In short, the argument by Mind Genomics is that knowledge emerges from scope with modest precision at each point (the big pattern emerges), rather than from precision with narrow scope. This is the key tenet of Mind Genomics: scope is better than precision, at least in the early explorations of a topic.

Step 8: Convert the Rating Scale in Two Ways

The first transformation is ‘Top 3’ defined as a transformed value of 0 when the original rating was 1-6, defined as 100 when the original was 7-9. The first transformation focuses on what ‘drives’ a person to select ‘donate.’ The second transformation is ‘Bot 3’ defined as a transformed value of 0 when the original rating was 4-9, defined as a transformed value of 100 when the original rating was 1-3. The second transformation focuses on what ‘drives’ a person to select ‘will not donate.’ To all transformed ratings a small random number was added (<10-5) to ensure variation in the transformed rating, and thus to ensure that the OLS (ordinary least-squares regression) will ‘work,’ and not ‘crash.’ OLS regression requires variation in the dependent variable. The addition of the small random number ensures that variation without materially affecting the results.

Step 9: Cluster the Individual Respondents Based Upon the Pattern of Their 16 Coefficients for Top3

The clustering is done using k-means clustering with the measure of distance being (1-Pearson Correlation), viz., [16]. The Pearson correlation coefficient shows the strength of a linear relation between two sets of measures. When the relation is perfectly linear, increases in one measure correspond to precise increase in the other measure. There is no scatter, the Pearson correlation is +1, and the distance is 0 (1-1=0). In contrast, when the relation is perfectly inverse, increases in one measure correspond to precise decreases in the other measure. Again, there is no scatter, the Pearson correlation is -1, and the distance is 2 (1–1=2). The clustering program generates two, and then three groups, called mind-sets, because the clusters represent groups who attend to the elements or messages in different ways. We select that cluster solution (the array of mind-sets) which tells the most obvious story (interpretable), and which comprises the smallest number of segments (mind-sets). For the data in this study, the three-mind-set solution was easier to understand.

Step 10: Create the Model for All Appropriate Data from the Respondents from Each Key Subgroup

Each group (Total, three Mind-Sets) generates three models or equation; Top3 (drivers of positive response), Bot3 (drivers of negative response), and RT (response time, or consideration time, measure of engagement with the material, whether the response to the element was positive or negative).

The model is a simple weighted, linear equation of the form:

Top3 (or Bot3) = ko + k1(A1) + k2(A2) … k16 (D4)

Response Time = k1(A1) + k2(A2) …. K16 (D4)

The additive constant k0, shows the estimated Top3 (or Bot3) response in the absence of elements. The additive constant can be thought of as a baseline response, or the underlying, fundamental likelihood of the respondent to ‘donate’ (Top3) or ‘not donate’ (Bot3). The additive constant is not meaningful for response time RT, since in the absence of elements there is nothing to which one can respond.

Step 11: Assign a New Person to One of the Mind-sets by Means of a Short Questionnaire, the PVI, Personal Viewpoint Identifier

The PVI assigns a NEW person to one of the mind-sets, and by so doing expands the scope of the small-scale studies to practical use, whether to create a more effective campaign (application), or to understand the distribution and possibly nature of the people in the different mind-sets. This adds to our general knowledge of the minds of people regarding messages relevant to donations (science).

Results

The Two Studies

To illustrate the value of small studies and what can be learned with a sequential approach requiring 2-3 days, we present the results of two studies designed to understand what messages may work for a campaign. The project deals with messaging to drive donations for Children’s Cancer Center, a hospital devoted to pediatric cancer (name of actual hospital disguised to maintain confidentiality). To make the topic general, the actual study was conducted among the general population to uncover the messages which would appeal the general population, not simply appeal to previous donors to Children’s Cancer Center.

The knowledge development was done in two phases. The first phase, or experiment, can be considered a pilot study with 10 respondents, sufficient to provide deep insights. The key difference between a pilot study of 10 respondents and a larger scale study of 40-50 respondents, or even a much larger scale study of 100-200 respondents, is simply the ability to identify different groups in the population and study the pattern of their responses.

Study 1: Preliminary Learning through a ‘Mini-Study’

As noted above, the Mind Genomics project begins with the topic (donating to Children’s Cancer Center specifically, or a cancer hospital for children in general). The next step requires the researcher to formulate the four questions that ‘tell a story.’ The questions emerging from the initial discussion tell such a story. They may not be the only questions, but in an exploratory study the objective is to learn just ‘what works.’ The four questions are:

A. Question A: What is it like to be a pediatric cancer patient?

B. Question B: Why is it important to support Children’s Cancer Center?

C. Question C: What are the outcomes for children when you donate?

D. Question D: How do you give your donation?

The study was executed with 10 respondents chosen from a large group of panel participants recruited by Luc.id, Inc., based in Louisiana, a provider of panel participants for on-line studies. Each respondent evaluated a different set of 24 vignettes, constructed according to Step 6 above. With as few as one respondent the Mind Genomics study generates meaningful data, readable at the level of that single respondent. With 10 respondents, and occasionally even as few as three or four, patterns rapidly emerge, patterns which are relevant for the respondents, but which may or may not be projectible to the population at large.

Table 1 shows the coefficients for the response time, the positive coefficients for the positive responses (I will donate), and the positive coefficients for the negative responses (I will not donate).

Table 1: The four questions, four answers to each question and the coefficients from the grand model relating the 16 elements to the binary transformed rating. To help the underlying patterns emerge, only the positive, non-zero, coefficients are shown for Top3 and for Bot3. The response times are shown for all elements, but only the response times of 1.1 seconds are shown, those driving ‘engagement’.
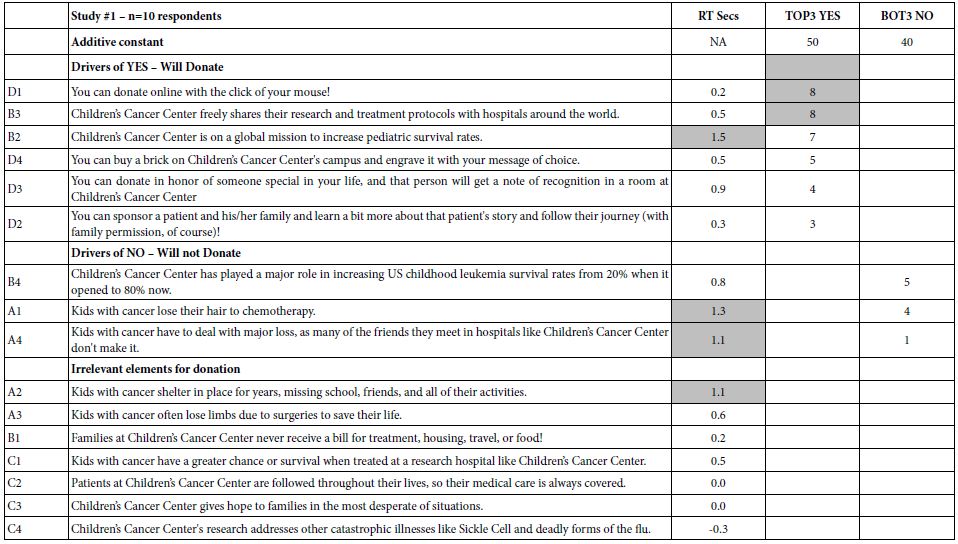
table 1

The response time gives a sense of the elements which most engage the respondent. Even with a small base size of 10 respondents, the data from the deconstruction of the ratings into the contribution of the elements gives a sense of the nature of elements that effectively engage. Those elements talk about the children, and survival. The elements may not ‘drive expected donations,’ but they do engage as shown by the long response time (consideration time). Moving on to the ratings, or more specifically the transformed ratings, Table 1 suggests that the additive constant, the proclivity to donate or not to donate ranges between 40 and 50. In the absence of elements which provide specific information, there is no dramatic drive to donate or not to donate, at least for these randomly chosen respondents. What is more important, however, is that among the 16 elements or, the messages, only two reach significance (coefficients of 8 or higher).

You can donate online with the click of your mouse!

Children’s Cancer Center freely shares their research and treatment protocols with hospitals around the world.

The two elements have little in common, suggesting that there is probably no single strong message. It is the nature of researchers to continue looking. These data suggest no ‘magic bullet.’ They do suggest that if there are any ‘magic bullets,’ they may be found in different mind-sets in the population, if such mind-sets can be identified. It is at this point that one can begin to formulate hypotheses about the psychology of donations. The hypothesis emerging here is that ‘painting a graphic word picture’ of the child will engage attention. The science of Mind Genomics has now enriched our thinking about the psychology of donations and generosity, suggesting that graphic design of the recipient is something to consider. The data suggest a further opportunity to understand the nature of the portrait being painted.

Study 2: Identifying the Underlying Structure of What Works for Donating to the Hospital

Study 1 constituted the first foray into the topic, executed with 10 respondents. Although 10 respondents are not often considered to be sufficient to establish results, a base of 10 respondents from one or two focus groups is acceptable when considered to be an exploratory step. Thus, we considered Study 1 to be exploratory, providing information in a disciplined way, but with simply too few respondents.

Here again are the questions from Study 1

Question A: What is it like to be a pediatric cancer patient?

Question B: Why is it important to support Children’s Cancer Center?

Question C: What are the outcomes for children when you donate?

Question D: How do you give your donation?

Based upon the patterns of responses, here are the four revised questions. The key change is Question D, and of course the text of the elements themselves.

Question A: What is it like to be a pediatric cancer patient (why would you want to help)?

Question B: Why is it important to support Children’s Cancer Center?

Question C: What are the outcomes for children when you donate?

Question D: What would inspire you to give?

The second study was conducted with 50 respondents, of which the data from 48 respondents were retained. The remaining two respondents did not provide age or gender, and so their data were eliminated.

Table 2 shows the same type of data as does Table 1, this time for the new set of respondents, and the new set of elements. Once again, each respondent evaluated a unique set of 24 vignettes, constructed by experimental design, so that the data can be analyzed down to the level of the individual respondent. This strategy, so-called ‘within-subjects design’ ensures that the data can be further deconstructed into subgroups called ‘mind-sets,’ based upon the patterns of the coefficients for each respondent. At first glance, the data reaffirm the previous finding from Study #1 that there are no elements which strongly driving expected donations, when the topic is associated with Children’s Cancer Center. One might consider this a failure when the objective is to discover the so-called ‘magic bullet,’ the message that will work for everyone. The result might be the continued search for this ‘magic bullet’ in successive efforts, only to realize in the end that there is no ‘magic bullet,’ or if there is, no one has any idea about what specifically it is  and how to express it. At the practical level, the effort will be seen to have been wasted. There will be no science of communication about charitable contributions and how people feel. The unsatisfactory conclusion, soon to be discarded is ‘no business results, no contributions to the science of people, no additional knowledge for science of charity communications.’

Table 2: Results from the total panel from Study #2.
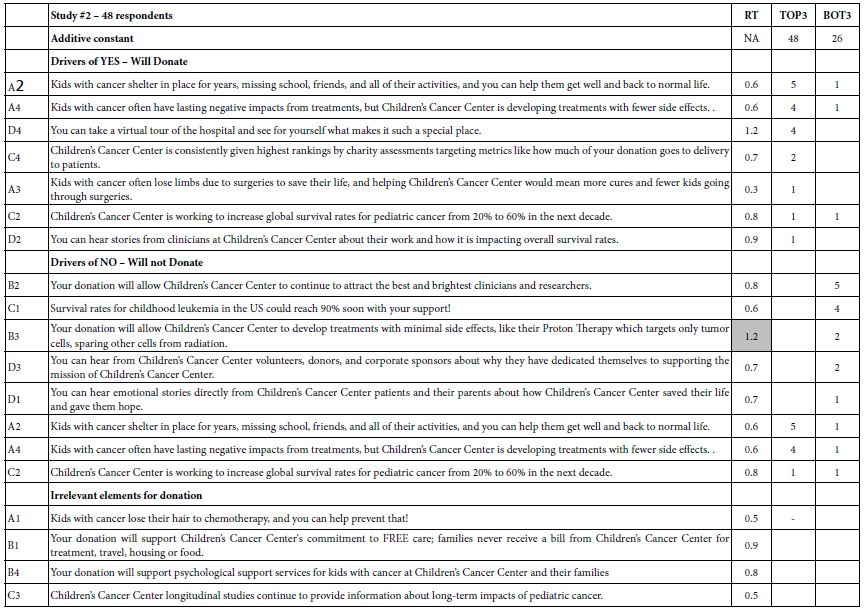
table 2

The picture changes, and significant learning for practical application and for foundational knowledge emerges, when one dives more deeply into Mind Genomics and discovers mind-sets. In Mind Genomics, the continuing data suggest the existence of what could be called mind-sets, different patterns of ideas which are interpretable in the form of a ‘story,’ patterns that seem to attach themselves to people. In the world of Mind-Genomics, considering people simply as ‘protoplasm which responds,’ there emerge groups of ideas which separately drive strong responses. People are the carriers of these ideas. People allow these groups of ideas to emerge. A person typically falls into a specific mind-set for a topic and not into the other mind-sets for the same topic. When we look at the data through the lens of mind-sets, using the computational process outlined in Steps 9 and 10 above and doing the computation on the Top3 (positive responses), we emerge with three new-to-the-world mind-sets, shown in Table 3 for Top3 (positive response – likely to donate), and in Table 4 for Bot3 (negative response – not likely to donate).

Table 3: Drivers of positive responses to messages, showing total panel, gender, and the three emergent mind-sets based on clustering using Top3.
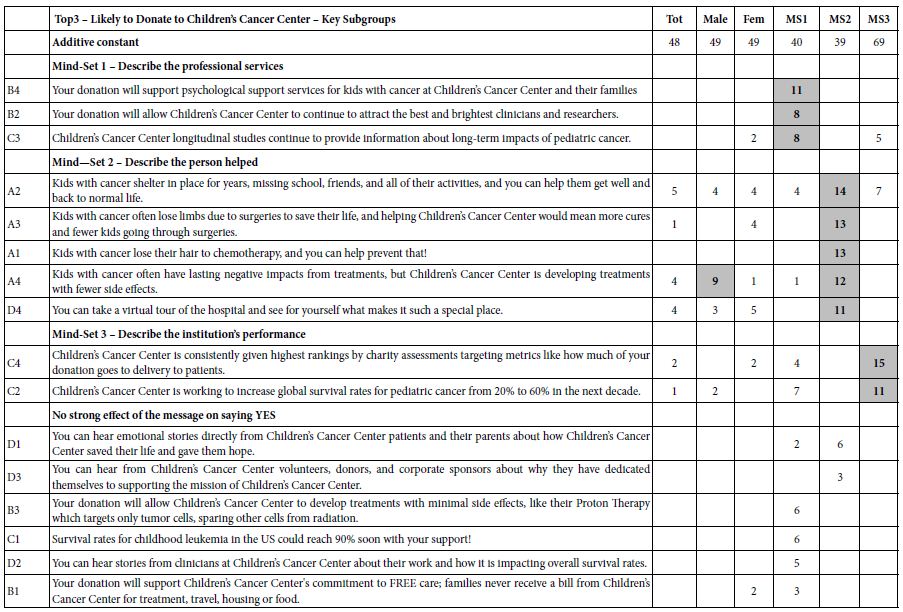
table 3

To strengthen the scientific aspect of the results—the learning which is meant to be foundational rather than simply a direction for messaging to raise money—we include gender, as well, comparing the responses of males and females. Table 3 suggests three mind-sets. It is in the mind-sets that the strong elements emerge, elements with coefficients of +8 or higher.

a. There are some positive elements by gender, but no strong performers at all. Both male and female respondents are modestly interested in donating (additive constant=49)

b. Mind-Set 1 – Describe the professional services (modestly interested in donating at a basic level, additive constant=40)

c. Mind-Set 2 – Describe the person helped (modestly interested in donating at a basic level, additive constant=39)

d. Mind-Set 3 – Describe the institution’s performance (strongly interested in donating at a basic level, additive constant=69).

Table 4 shows the messages that should be avoided, the messages driving the response of ‘Not Donate.’ The coefficients emerge from considering only ratings of 1 and 2 as relevant on the 5-point scale, with ratings of 3-5 (neutral, will donate) as not relevant, and coded as 0. The additive constant is far lower for Not Donate than it is for Donate, meaning that people are more inclined to say that they will donate. Several messages to be used by the Center are likely to ‘backfire’, driving donors away. Mind-Set 2 is especially sensitive to the wrong messages.

Table 4: Drivers of negative responses to messages, showing total panel, gender, and the three emergent mind-sets based on clustering using Top3.
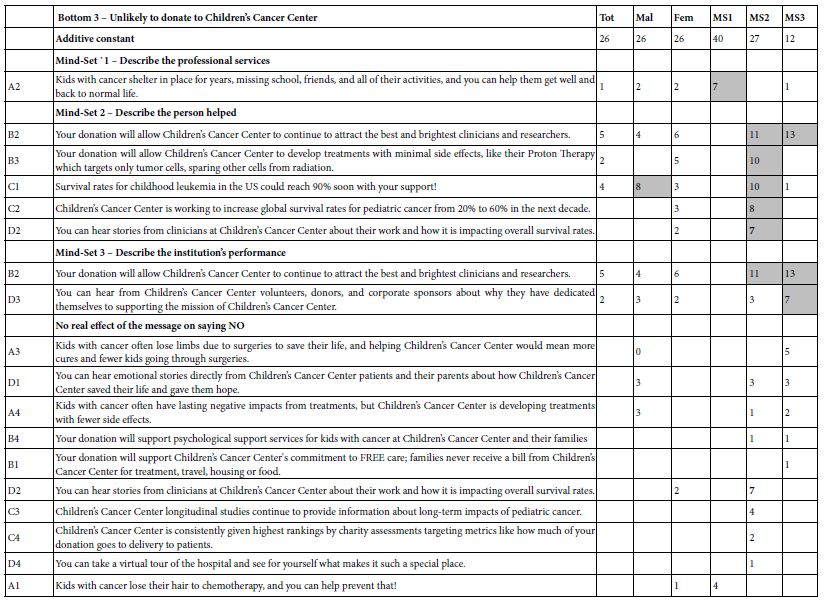
table 4

Finding these Respondents in the Population

A continuing topic in Mind Genomics is the value of a ‘next step’ beyond the already-important discovery of mind-sets. Mind-sets themselves provide a way of understanding daily life, through a new focus on the every-day and the way people differ in their typical behaviors. Yet, beyond the scientific contribution of knowledge is the remarkable potential of expanding the value of the learning, moving beyond the respondents tested in the study to the entire world. A simile is the colorimeter used to quantify colors of objects. The science of color can be developed in any location with any material. The real value of the science in terms of the ‘world outside’ is to measure the colors of new objects, not by repeating the study in which the colors were discovered, but rather by measuring the colors of the new objects using a machine in which the science has been already programmed [17-23]. The approach used in Mind Genomics is called the PVI, the personal viewpoint identifier. The objective is to use the data from Table 3 (MS1, MS2, MS3) to create a short questionnaire (six questions), on a simple to-use scale. The questions come from the actual study. The pattern of responses assigns a NEW PERSON to one of the three mind-sets. There are 64 possible patterns, each pattern mapping to one of the three mind-sets. Figure 1 shows the PVI, doing so in two parts. The left part is a short introduction, to introduce the person to the task, and to obtain optional background information. The right part is the actual PVI, including some basic questions about attitudes towards ‘giving’ and the six-question PVI. The results are forwarded to a database and can be sent to the respondents, as well.
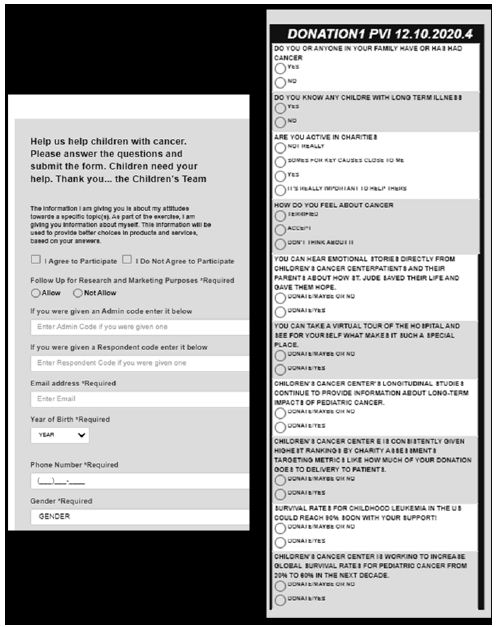
fig 1

Figure 1: The PVI, personal viewpoint identifier, based upon the second study. The PVI is located at: https://www.pvi360.com/TypingToolPage.aspx?projectid=1261&userid=2018.

Discussion and Conclusion

The empirical results are simple to discover, just by looking at the table of elements and how the elements or messages drive interest in donating. The message used in requesting should be straightforward and focus on how the organization saves and changes lives for the better. The outcome of the organization’s work, and not the process, should be the main message. One should avoid directly focusing on needs and tax breaks, respectively. Although a minority of prospective donors will care about needs or tax advantages, most people say that they will contribute when they are suitably convinced by the cause and mission of the effort and in the vision detailing how their contribution can help. It is at this point that one can begin to formulate hypotheses about the psychology of donations. The hypothesis emerging here is that ‘painting a graphic word picture’ of the child will engage attention. The science of Mind Genomics has now enriched our thinking about the psychology of donations and generosity, suggesting that graphic design of the recipient is something to consider. The data suggest a further opportunity to understand the nature of the portrait being painted. It is not important to point out major ‘learnings’ from the results, learnings which confirm or disconfirm what is known in the literature, or what is hypothesized to be the case for the psychology of donors or the psychology of children with cancer. That information is, of course, important to know for science. What is more important, however, is the ability to have at one’s disposal a tool for small-scale, iterative experimentation: Mind Genomics, a tool which returns rich information even with remarkably small base sizes, such as n=10 or even fewer. In the world of science, Mind Genomics becomes a tool bridging the gap between the idiographic (individual) and the nomothetic (the general world). Just as important, Mind Genomics becomes both a practical tool to increase donations, as well as a tool for the development of systematized knowledge, both for the current generation and for those to come—a ‘wiki of the mind.’ Finally, viewed from the grand proscenium arch of civilization, Mind Genomics provides a record of how people of a certain time, in a specific environment, and faced with known needs, think about topics— a record of inestimable value to philosophy, psychology, history, sociology, anthropology, and economics, just to name a few disciplines where knowledge of the granular is important.

References

  1. Cao X, Jia L (2017) The effects of the facial expression of beneficiaries in charity appeals and psychological involvement on donation intentions: evidence from an online experiment. Nonprofit Management and Leadership 27: 457-473.
  2. Das N, Guha, A, Biswas A, Krishnan B (2016) How product–cause fit and donation quantifier interact in cause-related marketing (CRM) settings: Evidence of the cue congruency effect. Marketing Letters 27: 295-308.
  3. Mejova Y, Garimella VRK, Weber I, Dougal MC (2014) February. Giving is caring: understanding donation behavior through email. In Proceedings of the 17th ACM conference on Computer supported cooperative work & social computing pg: 1297-1307.
  4. Childhood Cancer Survivor Study: An Overview. (2018, September 27). The National Cancer Institute. https://www.cancer.gov/types/childhood-cancers/ccss
  5. Childhood Cancer. (2020, Nov 7). The National Cancer Institute. https://www.cancer.gov/types/childhood-cancers
  6. Alex’s Lemonade (2020) Global Childhood Cancer Facts: By the Numbers. (2020, Dec 7). Alex’s Lemonade. https://bit.ly/3a49Cpl
  7. Connor, K. (2015, May 25). Why childhood cancer research gets shortchanged. Washington Examiner. https://www.washingtonexaminer.com/why-childhood-cancer-research-gets-shortchanged.
  8. Jude’s Children Research Hospital, 2020 Childhood Cancer Facts. (2020, Dec 7). St. Jude Children’s Research Hospital. https://www.stjude.org/treatment/pediatric-oncology/childhood-cancer-facts.html .
  9. Gabay G, Moskowitz HR (2012) The algebra of health concerns: implications of consumer perception of health loss, illness and the breakdown of the health system on anxiety. International Journal of Consumer Studies 36: 635-646.
  10. Galanter E, Moskowitz H, Silcher M (2011) The Price of Grace: Donations, Charities, and the Mind. People, Preferences and Prices: Sequencing the Economic Genome of the Consumer Mind pg:103.
  11. Moskowitz HR, Gofman A (2007) Selling blue elephants: How to make great products that people want before they even know they want them. Pearson Education.
  12. Williams LL, Quave K (2019) Quantitative Anthropology, A workbook. Elsevier.
  13. Gabay G, Moskowitz H, Gere A (2019) September. UNDERSTANDING THE DONATING MIND & OPTIMIZING MESSAGING–PUBLIC HOSPITALS. In 12th Annual Conference of the EuroMed Academy of Business.
  14. Gofman A, Moskowitz H (2010a) Isomorphic permuted experimental designs and their application in conjoint analysis. Journal of Sensory Studies 25: 127-145.
  15. Moskowitz H, Gofman A, I novation Inc (2003) System and method for content optimization. U.S. Patent 6,662,215.
  16. Ramasubbareddy S, Srinivas TAS, Govinda K, Manivannan SS (2020) Comparative Study of Clustering Techniques in Market Segmentation. In Innovations in Computer Science and Engineering, pg: 117-125, Springer, Singapore.
  17. Gofman A, Moskowitz, HR (2010b) Improving customers targeting with short intervention testing. International Journal of Innovation Management, 14: 435-448.
  18. Global Initiative for Childhood Cancer. World Health Organization. (2020, December 7). https://www.who.int/cancer/childhood-cancer/en/
  19. Health Affairs, 2020. https://www.healthaffairs.org/doi/full/10.1377/hlthaff.25.2.541
  20. Importance of CEO involvement in creating a culture of philanthropy in hospitals.
  21. Moskowitz HR, Gofman A, Innovation Inc, (2011). System and method for performing conjoint analysis. U.S. Patent 7,941,335.
  22. Notaro S (2020) https://bit.ly/3b7wBQi.
  23. Social Science Direct (2020) https://www.sciencedirect.com/science/article/abs/pii/S2213076415300051. Use of social media by US Children’s’ hospitals.
The Organization of the Dental Service in the Voronezh Region


In the article, on the territory of a large subject of the Russian Federation, the features of the organization of dental care for adults and children are considered. During the meetings in the autonomous health care institution, in accordance with the action plan of the Department of Health of the Voronezh Region, the issues of primary prevention of dental diseases among the population of the Voronezh Region within the framework of the state program of the Russian Federation “Development of Health Care”are highlighted. When considering the current state of scientific medicine and the practical direction of preserving the health of the population, the relevance of dental research remains unchanged. The analysis of literature sources and reporting materials showed the importance of dynamic observation of medical and social indicators, conditions and lifestyle, the level and structure of dental morbidity, and the demographic situation. The author of the work is well aware of the importance of the background of dental measures aimed at prevention (first of all) and treatment (if necessary). Speaking about the indicators of morbidity in dentistry, the author emphasizes the need to study it to assess the public health of the entire population. The data of the social and hygienic monitoring of the Voronezh Region for 2017-2019 were used.

Keywords

Curatorship, Dental service, Perspective directions of development

In recent decades, the broadest powers to provide medical care to the population have been transferred to the level of the constituent entities of the Russian Federation, including the dental service. The broad capabilities of specialized medical organizations operating in legally permitted forms of ownership are provided by a significant number of personnel, high external and internal resources, and constant updating of prescriptive directives on professional activities in relation to all personnel with explanations on the implementation of effective and high-quality provision of medical care. The dental service in the health care system of the Voronezh Region is currently characterized by the availability and quality of care to the population, the introduction of modern dental technologies into practice, and constantly improving the professional level of specialists [1].

Materials and Methods

In order to analyze and evaluate the results of preventive and curative work to reduce the incidence of diseases among the population in the dental profile, it is extremely important to consider the shortcomings available in the official accounting documents. Therefore, every year the results of the work are summed up through the preparation of an analytical review of the activities of the dental service of the Voronezh Region. It is such a study that creates the possibility of forming a strategy for organizing work on the part of a dentist working in outpatient clinics (APU) and managing the health care vertical at the regional level. At the beginning of 2020 in the Voronezh region, the number of initially applying for dental care fell by 3.9%, while initially seeking children at 6.5%. There is no doubt about the information that crisis situations in various spheres of society aggravate social and hygienic factors that affect the dental morbidity in the direction of deterioration. This constantly directs the theoretical and practical parts of the work carried out to re-evaluate the forces of these factors, as well as to find ways to optimize the ongoing preventive work.

We have studied and used the data of the reports, conducted a comparative analysis concerning the personnel potential of the dental service of the Voronezh region in 2017-2019. (report forms No. 17, 30, 47), the availability of resources, as well as the opinion that the health of the population is directly related to medical and demographic indicators against the background of the results of preventive work included in the main indicators of the dental service. This work, carried out in the Voronezh Region, is fully comparable with the existing world experience in planning preventive programs to reduce the dental morbidity of the population, for the strategic unity of science and practice.

Results of the Study

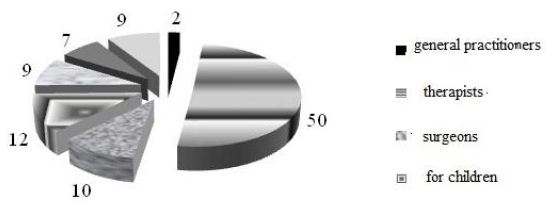
At the beginning of 2020, the dental service of the Voronezh Region, as a subject of the Russian Federation, has 13 dental clinics, including one for children, 19 dental departments, 10 dental offices at district hospitals (RB), 293-at other medical organizations of the Voronezh region, including dispensaries, sanatoriums, general education institutions, enterprises. The structural composition of dental specialists has remained virtually unchanged over the past years. In 2019, 1156 doctors of the dental profile (in state medical organizations) and 607 doctors of the non-state dental profile provided outpatient dental care in the region. The share of dentists in the structure of the region’s dental specialists working in the public sector was 8.8% in the reporting year (9.1% in 2018).

In recent years, the stability of the personnel potential of public sector dental doctors has been noted. In state medical organizations in the region as a whole, in 2019, 1308.5 full – time positions of dental doctors were allocated (in 2018 – 1319), employed – 1151 (in 2018 – 1164.25), individuals – 1156 (in 2018-1156). The percentage of staffing for occupied positions was 88% (in 2018 – 88.3%), for individuals-88.3% (in 2018-87). The percentage of dental doctors in 2019 by position (public sector) is shown in Figure 1.

fig 1

Figure 1: Percentage of dental doctors in 2019 in the Voronezh Region.

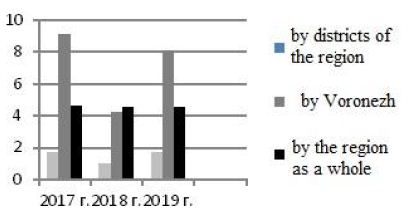
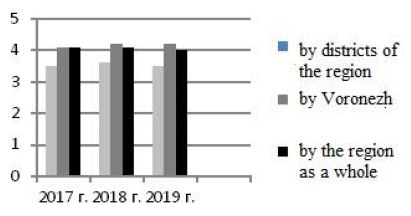
Of course, the focus is on the work of the therapeutic APUs of the region, both in the adult and in the child population, the figures show the indicators of the availability of dentists-therapists for 2017 – 2019 (Figure 2 and 3, respectively). The priority remains to work with the younger generation on the basis of the principle “prevention is better than treatment” [2]. But with the staff at pediatric dentistry of the medical organizations of the districts in a difficult situation: a low security child population by dentists for children (1.7 while the recommended ratio of 5.0) due to insufficient staffing and lack of them in a few areas (in 2019 is not entered into the appointment with a dentist in BUZ VO “Nizhnedevitskiy RB”) (Figures 2 and 3).

fig 2

Figure 2: The provision of dentists-therapists per 10 thousand adults in the region in 2017-2019.

fig 3

Figure 3: Provision of dentists-therapists for 10 thousand children in the region in 2017-2019.

Children’s dentists actively participated in the medical examination of the children’s population of the region [3]. The school preventive program is carried out in all general education institutions of Voronezh and the districts of the region. The activities of the dental service of the Voronezh Region are carried out in accordance with the Procedures for Providing Medical Care to Adults and Children with dental diseases, as well as in accordance with the Clinical Recommendations (treatment protocols) of major dental diseases. The proportion of sanitized patients from primary referrals in the region in 2019 was 59.85% (in 2018 – 60.1%), in the regions of the region decreased from 60.5% in 2018 to 57.62% in 2019, in Voronezh increased from 63.1% in 2018 to 63.4% in 2019. The indicator of those examined for preventive purposes from the number of primary applicants in the region decreased from 50.1% in 2018 to 47.36% in 2019, in Voronezh also decreased from 46.2% in 2018 to 45.16% in 2019, in the regions of the region there was also a decrease – from 52.4% in 2018 to 50.04% in 2019.

In all schools, gymnasiums and lyceums of Voronezh, hygiene lessons are held in primary school classes on the rules of oral care, and health schools are open. Despite this, the number of people with a healthy oral cavity per 1000 children under the age of 14 years, 11 months and 29 days in the whole region decreased and amounted to 548.73 (in 2018 – 575.42), in the districts of the region the indicator increased slightly – from 477.04 in 2018 to 477.66 in 2019, and in Voronezh it decreased – from 695.28 in 2018 to 627.13 in 2019 [4].

Discussion

The implementation of the financial plan for 1 dentist-orthopedist for 2019 was 98.5% in the region (in 2018 – 99.4%), including 98.5% in the regions of the region (in 2018 – 104%), 100.8% in Voronezh (in 2018 – 97.6%). Kantemirovskaya RB (92%), Repyevskaya RB (93.7%), Rossoshanskaya RB (91.2%), Ternovskaya RB (95.97%), Ertilskaya RB (86%), VOKB No. 2 (34.3%), VSP No. 2 (86.7%), VSMU Dental Polyclinic did not meet this indicator.. N. N. Burdenko (92.6%), BUZ VO “VSP No. 5” (99.1%). ganizations of the dental profile of the Voronezh region actively participate in the actions held within the framework of the regional interdepartmental project “Live long!”, with the support of the Department of Health – the program “Kaleidoscope of Health”, with the support of the Dental Association of Russia in the person of the VROO “Dental Association” from 01.03.2019 to 31.03.2019, the campaign “A dazzling smile for life” was held for schoolchildren of the Voronezh region. And on May 23, 2019, the departure of 3 specialists of the AUZ VO “VOKSP” was carried out in the city of Liski for participation in the review-competition within the framework of the specified project. This event was attended by representatives of all dental clinics in Voronezh. In 2019, the specialists of the regional clinical dental polyclinic (AUZ VO “VOKSP”) carried out 17 visits to medical organizations in the region (in 2018 – 17).

Supervision is in AUZ IN “WAXP” a huge breakthrough in the provision of organizational and methodological assistance to the heads of the dental service areas. In 2019, 1710,438 visits were made to the doctors of the dental profile of the region, which is 2.8% less than in 2018 (1759,157 visits). In order to improve dental knowledge in the field and in accordance with the work plan of the dental service of the region, together with the specialized departments of the Burdenko State Medical University, 6 events were held in 2019 (7 in 2018): inter – regional events – 3, regional workshop – 2, city event – 1. Annually, the staff of the regional clinical dental clinic publishes information and methodological materials for dentists of the region. The program of state guarantees for dentistry for 2019, according to preliminary data, was implemented in the region by 101.3% in the UET, in Voronezh-by 100.9%, in the regions of the region-by 100.5%. Below the control values, the PGG was performed by the dental services of the Bogucharskaya RB, Petropavlovsk RB, Podgorenskaya RB, and Ternovskaya RB dental hospitals.

The development and implementation of the main directions of development of stoma-tragicheskoi services, and coordination of dental medical organizations of all forms of ownership in the field provides organizational and methodical study of the regional clinical dental clinic.

The priority areas of organizational and methodological work are defined as:

  • providing organizational, methodological and advisory assistance to the heads of dental services
  • field forms of operational control over the activities of dental units
  • systematic analysis of the activities of the dental service of the region, the implementation of analytical work on the assessment of the state and dynamics of the development of its individual structures
  • development of current and long-term plans for the activities of the dental service of the region, strategic planning
  • organization of activities in priority areas of development of the dental service of the region, their implementation, monitoring and evaluation of the effectiveness of implementation
  • conducting permanent training of specialists of the dental service of the region of the middle and senior level (conferences, seminars)
  • information support (issue of methodological recommendations and information letters).

Insufficient provision and understaffing of staff in the districts of the region, especially secondary medical personnel, weak material and technical base of a number of facilities for providing dental care to the population of the districts of the region remain problematic [5]. The best performance has reached the dental service of BUZ VO “Anna RB”, BUZ VO “Bobrovskaya RB”, BUZ VO “Kalacheevskogo RB”, BUZ VO “Liskinsky RB”, BUZ VO “Pavlovskaya RB”, BUZ VO “Ramon RB”, BUZ VO “Buturlinovskiy RB”, BUZ VO “Novousmanskiy RB”. Last rank place in the rating table of the medical organizations of the districts is a dental service BUZ VO “Bogucharskaya RB”, BUZ VO “Vorob RB”, BUZ VO “Ternovskaya RB”, BUZ VO “Kantemirovskaya RB”, BUZ VO “Novokhoperskiy RB”.

Among the dental clinics in Voronezh, the best indicators were achieved by the VSP No. 6 and VKSP No. 4 dental clinics [5].

Conclusion

The priority directions of the development of the dental service of the Voronezh region can be considered:

  • strict implementation of the Program of state guarantees to the population of the region for the provision of dental care
  • equipping dental departments and offices in accordance with the standards of equipping Procedures for providing medical care to adults and children with dental diseases
  • improving the availability, safety and quality of dental care to the population
  • priority of prevention in the field of health protection, including in the organization of the work of the school dental service of the districts of the region
  • entry into the continuing medical education program.

References

  1. Antonenkov Yu E, Chaikina NN, Saurina OS (2020) About the dental service of the Voronezh region. Problems of social hygiene, health care and the history of medicine 28: 239-242.
  2. Korolenkova MV, Khachatryan AG, Harutyunyan LK (2020) Perinatal risk factors for caries of temporary teeth 99: 47-51.
  3. Pervushina OA, Antonenkov Yu E, Chaikina NN (2014) On the issues of optimizing the work of secondary medical personnel with the adult population in the dentistry of the Voronezh region. Current Issues of Education and Science 1: 99-100.
  4. Chubirko MI, JM Chubirko, Yu e He (2019) Internal quality control of medical care in scientific publications and normativnyh legal acts of the Russian Federation (review). Saratov Journal of Medical Scientific 15: 928-930.
  5. Golikova LO, Yu E Antonenkov, Yu Yu Bortnikova (2020) Formation of a health-saving environment in youth educational organizations as a basis for the prevention of morbidity, Based on the materials of the international scientific and practical conference. Modern Society, Education and Science 64: 76-80.

Health Care Provider’s Knowledge on Snakes and Snakebites – A Study in the Three Tongu Districts of the Volta Region, Ghana

Abstract

Objectives: According to the World Health Organization, out of the 5 million snakebites that occur annually, 2.7 million results in envenomation out of which between 81,000 and 139,000 leads to death. Since snakebite is more prevalent in developing countries, it is imperative that their healthcare professionals should be knowledgeable on snakes and snakebites to enable them provide the optimal management of snakebite. This study therefore assessed health professionals’ preparedness by way estimating their knowledge on snakes and snakebites three Tongu districts in Ghana.

Method: Using a de novo semi-structured questionnaire, data was collected from 186 health workers using a google form whose link was sent via WhatsApp platforms on their Android phones. Data was analyzed using Statistical Package for the Social Sciences (SPSS) Version 23. Results were presented in the form of tables and association between variables determined using the appropriate tools at a confidence interval of 95%.

Results: The study showed the respondents’ overall mean knowledge score on snakes was lower than their knowledge on snakebites [(8.31 ± 2.95/18 (46.2%)] vs. [13.78 ± 4.0/22 (62.6%)]. Respondents’ sex and a previous training on snakebite were significantly associated with their knowledge on snakes. Their knowledge on snakebites, was significant associated with type of health facility, professional grouping and training experience (p<0.05).

Conclusions: The knowledge of health workers in the Tongu districts in Ghana on snakes and snakebite was inadequate. Since previous in-service training was associated with respondents’ knowledge on snakes and snakebite, educational intervention is imperative, especially the nursing professionals who are frontline health workers.

Keywords

Knowledge, Healthcare providers, Snakes, Snakebites, Tongu districts

Introduction

According to the World Health Organization, (2010) when venomous snakes bite, it may not introduce venom into the tissue referred to as dry bite or non-venomous bite [1]. Dry bites may or may not be associated with local inflammation but do not present with systemic manifestations. Following a dry bite, the victim may present with presence of fang marks, local swelling, pain, redness and bleeding from the bite sites as well as reduced function of the affected body part resulting in anxiety [1]. The systemic effects produced after injection of large amount of venoms into the victim may cause haemotoxicity, neurotoxicity, nephrotoxicity, and cardiotoxicity.

In West Africa, most of the snakebites occur in the savanna regions with the saw-scaled or carpet viper (Echis ocellatus) being the snake most implicated in causing morbidity and mortality [2]. Other venomous snakes in the West African region include the spitting cobras (Naja nigricollis and N. katiensis), the puff adders (Bitis arietans) and (Dendroaspis spp) the manbas [1].

Although, the exact number of snakebites globally is not known, the WHO (2019a) estimated that about 5.4 million snake bites occur each year, resulting in 1.8 to 2.7 million cases of envenoming [3]. There are between 81 410 and 137 880 deaths and around three times as many amputations and other permanent disabilities each year. Most snake envenoming and fatalities occur in South Asia, Southeast Asia, and sub-Sahara Africa, with India reporting the most snakebite deaths of any country [4]. In sub-Saharan Africa, about a million people are estimated to be bitten by snake each year, with estimated 7000-20 000 deaths occurring with West Africa bearing an annual snakebite deaths of 3,557 to 5,450 [5]. Europe, Australia, and North America statistically have the lowest incidence of envenoming [5]. Many people who survive bites nevertheless suffer from permanent tissue damage caused by venom, leading to disability [6]. Despite the number of deaths caused by snakebite annually, it was until June, 2017 that the World Health Organization formally listed snakebite envenoming as a highest priority neglected tropical disease [7]. Worldwide, snakebites occur most frequently in the summer or dry seasons when snakes are active and humans are undertaking outdoors related activities such as agriculture [8].

Injuries, disabilities and deaths from snakebites are something that happens daily in most parts of the world particularly in the poorest communities. Knowledge in relation to the management of snakebite patients is therefore very important. If clinicians are unfamiliar with the different species of snakes and unable to distinguish between venomous and non-venomous snakes, as well as the characteristics of snakebites, it can be difficult to know how to respond appropriately in terms of management in the event of a bite. Therefore, it is important for healthcare providers especially those in rural environments to be well equipped in terms of knowledge on snakes and snakebites which is required for effective management of victims who get bitten by snakes hence the need for this study in three rurally situated Tongu districts of the Volta region of Ghana. Again, this study is important since a search on the internet found no publication on the level of knowledge of health care professionals on snakes and snake bites in Ghana although some studies were done in some African countries.

Methodology

Study Design

A descriptive cross-sectional design was used to conduct this study between May to July 2019 among health care providers comprising of medical doctors, pharmacists, pharmacy technicians, physician/medical assistants, nurses of various categories and midwives working in selected Community-Based Health Planning and Service (CHPS) compound, health centres and hospitals.

Study Location

The study was undertaken in selected health facilities across the three neighbouring districts in the Volta region of Ghana namely South Tongu, North Tongu and Central Tongu. The selected health facilities include the Sogakope district and Comboni hospitals, Kpotame, Dabala, and Adutor health centres, Sasekope and Agbakope CHPS compounds from the South Tongu district; the Battor Catholic hospital and Volo health centre in the North Tongu district; the Adidome hospital, Mafi-Kumase and Mafi Dove health centres in the Central Tongu district. The Tongu districts are located in the South eastern part of the Ghana and are mainly inhabited by people of the Ewe tribe speaking the Tongu dialect. The total population of these districts in the 2010 population census was 237, 138 with agriculture as the main occupation of the people [9].

Sample Size

The sample size for this study was calculated using the Cochran formula, formula 1

Where t = value for selected alpha level of 0.025 in each tail = 1.96, d = acceptable margin of error for proportion being estimated = 0.05, p is the estimated proportion of an attribute that is present in the population, which is considered as 0.5 and q is 1-p. The knowledge of health care providers about snakes, snakebites and the management of snakebites was estimated at 50%.

formula 2

Since 384 exceeds the 5% (537 x 0.05 = 26.9) of the eligible study population of 537 having excluded the 20 who took part in the piloting, there was the need to use the Cochran correction formula to get adjusted sample size formula 5

formula 3

Assuming a response rate of 90%, the actual sample size = formula 4 = 244

The total response received was 186 giving a response rate of 76.2% (186/244*100).

Sampling Technique

A total of 186 respondents across the three Tongu districts participated in the study. The selection of respondents for this study was done through the use of both census and convenience sampling techniques. Effort was made to take a census sample of all the pharmacists (5), physician/medical assistants (26), medical doctors (17), and pharmacy technicians (6) because of their small numbers in the selected health facilities. However, for the nurses and midwives who were about 483, convenience sampling technique was applied to select the respondents.

Collection Instrument and Technique

Data for the study was collected in the period between May and June, 2019 through the use of a self-administered semi-structured questionnaire designed using google form. Section one of the questionnaire consists of eight questions on sociodemographic characteristics of the respondents; section two, eighteen questions assessing the knowledge on snakes and section three, sixteen questions assessing the knowledge on snakebites. The questionnaire development was guided by the WHO (2010) publication on Guidelines for the prevention and clinical management of snakebites in Africa. The questionnaire was administered through the WhatsApp accounts of the respondents using the link https://forms.gle/iV5NtKzdjbg5LTSc9 which they submitted online after the completion of the form.

Data Analysis

Microsoft Excel spreadsheet was generated from the google form. The data was processed and cleaned after which analysis was done using Statistical Package for the Social Sciences (SPSS) Version 23. Descriptive data were presented as frequencies, percentages and means in tables. Association between variables was determined using a confidence interval of 95%. Significance was assumed when p<0.05.

Data Measurement

The level of knowledge of respondents on snakes and snakebite were assessed by scoring the answers provided by the respondents which are compared with literature sources. A score of 1 mark was awarded for any correctly answered question with options to choose from. Besides the wrong answer, an ‘I don’t know’ option also attracts no mark. For open-ended questions that requires the respondent to provide a specified number of answers, each correct answer scores 1 mark, hence the maximum total score for a question requiring three answers is 3. The total scores for the knowledge on snakes and snakebites of the respondents were 18 and 22 respectively.

Ethical Consideration

Permission was sought from the District Health Directorates, Medical Superintendents and the Administrators of the South Tongu, North Tongu and Central Tongu hospitals before the data was collected. Study tool used for the study was approved by the Ethic Committee of the School of Medicine and Health Sciences of the University for Development Studies. Consent was obtained once the respondents agree to take part in the study, completed the form and submitted it. The preamble on the questionnaire explained the purpose of the research and stating clearly that submitting the form after completion is indicative of giving consent. They were also assured of confidentiality of all the information they were to provide.

Results

Socio-Demographic Characteristics of Respondents

Table 1 shows the socio-demographic characteristics of respondents in this study. Majority, 95 (51.1%) were males, and were within the age group 30-39 years, 98 (52.7%). Most respondents, 87 (46.8%) were from the South Tongu district, followed by the North Tongu, 54 (29.0%) with Central Tongu having the least number of respondents, 45 (24.2%). For the number of years of practice, majority, 112 (60.2%) had served for less than five years with the least number, 3 (1.6%) working for more than ten years. Majority of respondents, 146 (78.5%) work at various hospitals, while those from health centres and CHPS zones were 25 (13.4%) and 15 (8.1%) respectively. Registered General Nurses, 80 (43.3%) formed the largest number of health professional group with the pharmacists, 4 (2.2%) being the least.

Table 1: Socio-demographic characteristics of respondents.

Variable Subgroup Frequency Percentage (%)
Sex Male 95 51.1
Female 91 48.9
Age (years) 20-29 81 43.5
30-39 98 52.7
>39 7 3.7
District South Tongu 87 46.8
Central Tongu 45 24.2
North Tongu 54 29.0
Number of years of practice (years) <5 112 60.2
5-10 71 38.2
>10 3 1.6
Level of health facility CHPS compounds 15 8.1
Health Centre 25 13.4
Hospital 146 78.5
Profession category Registered General Nurse 80 43.0
Enrolled/Community Nurse 37 26.3
Midwife 15 8.1
Medical Doctor 14 7.5
Pharmacy Technician 5 2.7
Pharmacist 4 2.2
Physician/Medical assistant 19 10.2

Knowledge of Respondents about Snakes

Table 2 shows knowledge of respondents on snakes. The top five best answered questions on the knowledge of respondents about snakes were; Snakes being reptiles (99.0%), Cobra being venomous (92.0%), not all snakes are venomous (85%), identification of Cobra (82.0%), Cobra being the snake that spit into the eyes of the perceived enemies and Puff adder being venomous (67.0%). Five questions about snakes which were most poorly scored were; Identification of Savanna egg eater (2.0%), identification of Boomslang (3.0%), identification of Africa beauty snake (4.0%), Savanna egg eater being nonvenomous (5.0%) and Africa beauty snake being partially venomous (10.0%). The overall average knowledge score of respondents about snakes was 8.31 ± 2.950/18 (46.2%).

Table 2: Knowledge of respondents on snakes.

Question Responses Mean knowledge score Percentage knowledge score
Correctness Frequency Percentage
What type of animals are snakes? (Reptiles) Incorrect 2 1.1 0.99 ± 0.103 99.0
Correct 184 98.9
All snakes are carnivorous, i.e. feed on other animals. (Yes) Incorrect 78 41.9 0.58 ± 0.495 58.1
Correct 108 58.1
All snakes are venomous, i.e. inject “toxins” or venom into a person after a bite? (No) Incorrect 28 15.1 0.85 ± 0.359 85.0
Correct 158 84.9
All snakes have fangs in front of their mouth. (No) Incorrect 86 46.2 0.54 ± 0.500 54.0
Correct 100 53.8
Snakes pick sounds using their ears? (No) Incorrect 133 71.5 0.28 ± 0.453 29.0
Correct 53 28.5
Name of snake that spits venom towards the eyes’ enemies? (Cobra) Incorrect 62 33.3 0.67 ± 0.473 67.0
Correct 124 66.7
Identify the snake A

{Boomslang/green tree snake)

Incorrect 181 97.3 0.03 ± 0.162 3.0
Correct 5 2.7
Is snake A venomous, partially venomous (V) or nonvenomous (NV)? (NV) Incorrect 94 50.5 0.49 ± 0.501 50.0
Correct 92 49.5
Identify snake B (Cobra)


Incorrect 34 18.3 0.82 ± 0.388 82.0
Correct 152 81.7
Is snake B venomous, partially venomous or nonvenomous? (V) Incorrect 15 8.1 0.92 ± 0.273 92.0
Correct 171 91.9
 Identify snake C (Python)


Incorrect 76 40.9 0.59 ± 0.493 59.0
Correct 110 59.1
Is snake C venomous, partially venomous or nonvenomous? (NV) Incorrect 114 61.3 0.39 ± 0.488 39.0
Correct 72 38.7
Identify snake D (Savanna egg eater) Incorrect 183 98.4 0.02 ± 0.126 2.0
Correct 3 1.6
Is snake D venomous, partially venomous or nonvenomous? (NV) Incorrect 176 94.6 0.05 ± 0.226 5.0
Correct 10 5.4
Identify snake E (Puff adder) Incorrect 133 71.5 0.28 ± 0.453 29.0
Correct 53 28.5
Is snake E venomous, partially venomous or nonvenomous? Incorrect 62 33.3 0.67 ± 0.473 67.0
Correct 124 66.7
Identify snake F (Africa beauty snake) Incorrect 178 95.7 0.04 ± 0.203 4.0
Correct 8 4.3
Is snake F venomous, partially venomous (PV) or nonvenomous? (PV) Incorrect 167 89.8 0.10 ± 0.304 10.0
Correct 19 10.2
Overall mean score 8.31 ± 2.950/18 46.2%

Correct answers are in parenthesis ( ) at the end of the question.

Association between Socio-Demographic Characteristics and Knowledge on Snakes

Table 3 shows association between socio-demographic characteristics and knowledge on snakes. For knowledge of respondents about snakes, males significantly scored better than females (9.04 vs. 7.55; p < 0.001). Respondents working at the lowest part of the health system, the CHPS compound obtained the best scores (9.27), followed by those in the health centres (9.24) while respondents in hospitals scores the least of 8.05 but the differences were not significant. Respondents from the Central Tongu district obtained the best mean score (9.04) followed by North Tongu (8.67) and South Tongu recorded the lowest (7.17) but the differences were not significant. There was no significant association between area of profession and knowledge on snakes but pharmacists had the highest mean score (10.25) and the Registered General Nurses (RGNs) had the lowest mean score (7.80). The prescribers and pharmacy groups had a better knowledge mean scores of 9.67 and 9.27 respectively while the nurses and the midwives group scored 8.01 but there were no significant differences. Respondents who had training on snakebite management significantly scored better than those who did not received training (9.93 vs. 7.60; p < 0.0001). Respondents with more than 10 years of practice scored better with mean score of 12.50, followed by respondents with < 5years (8.48) and 5-10 years (7.93) in that order but there were no significant differences.

Table 3: Association between socio-demographic characteristics and knowledge on snakes.

Variable Sub group Mean score ± standard deviation (SD) p-value
Sex Male 9.04 ± 2.982 < 0.001*
Female 7.55 ± 2.730
Level of health facility CHPS compound 9.27 ± 2.963 0.75
Health centre 9.24 ± 3.551
Hospital 8.05 ± 2.803
District of health facility South Tongu 7.71 ± 2.753 0.27
Central Tongu 9.04 ± 3.398
North Tongu 8.67 ± 2.706
Area of profession RGN 7.80 ± 2.528 0.35
Pharmacist 10.25 ± 4.924
Medical officer 9.64 ± 3.455
Physician assistant 9.00 ± 3.448
CHN/ENa 7.82 ± 2.855
Pharmacy technician 9.20 ± 3.114
Registered midwife 9.73 ± 2.890
Professional groups Nursing and midwifery group 8.01 ± 2.726 0.30
Prescriber group 9.67 ± 3.755
Pharmacy group 9.27 ± 3.412
Training No training 7.60 ± 2.600 <0.001*
Received training 9.93 ± 3.076
Number of years of practice <5 years 8.48 ± 2.825 0.060
5-10 years 7.93 ± 3.073
>10 years 12.50 ± 2.121

aCHN/EN – Community Health Nurse/Enrolled Nurse, * Statistically significant.

Knowledge of Respondents on Snakebite

The top five best answered questions on the knowledge of respondents about snakebite were; the local signs and symptoms of snakebite (93.0%), ways of preventing snakebite (84.0%), handling of a death snake not being safe enough (78.0%), signs and symptoms of snakebite being determined by the type of snake responsible for the bite (78.0%), the rainy season being the season with most snakebite incidence in Ghana (74.3%), The five most poorly scored questions on knowledge about snakebite were; percentage of snakebite (out of hundred percent) that may come from venomous snakes (1.1%), walking on a log of wood being the best thing to do to prevent snakebite when you come across a log of wood on your path in the forest (11.2%), number of times a venom will be injected into a victim out of hundred bites (13.4%), sleeping under mosquito nets preventing snakebites (32.1%) and the day being the most common time of snakebite (37.0%). The overall average knowledge score of the respondents on snakebite was 13.78 ± 4.000/22 (63%). Table 4 shows knowledge of respondents on snakebite.

Table 4: Knowledge of respondents on snakebite.

Question

Responses

Mean knowledge score ± SD Percentage knowledge score
Sub-group/

Correctness

Frequency Percentage
State 3 ways a person can prevent snake bitesa 0/3 3 1.6 2.53 ± 0.758 84.0
1/3 21 11.2
2/3 36 19.3
3/3 126 67.4
Handling a dead snake’s head is safe enough? (No) Incorrect 41 21.9 0.78 ± 0.416 78.0
Correct 145 77.5
Fang marks can always be seen or found on the victim after every snake bite? (No) Incorrect 57 30.5 0.69 ± 0.462 69.0
Correct 129 69.0
Can a person report at the hospital with symptoms of snake bite toxin injection without actually being bitten by a snake after he or she might have been pricked by an object he or she suspected to be a snake? (Yes) Incorrect 70 37.4 0.62 ± 0.486 62.0
Correct 116 62.0
Sleeping under mosquito nets can prevent snakebites. (Yes) Incorrect 126 67.4 0.32 ± 0.469 32.1
Correct 60 32.1
Do you think every time a venomous (“poisonous”) snake bites, it always injects venom (poison) into the victim? (No) Incorrect 93 49.7 0.50 ± 0.501 50.0
Correct 93 49.7
Which of the following is best used to determine if a person bitten by a snake had venom actually being injected into him or her by the snake?b Incorrect 64 34.2 0.66 ± 0.476 65.2
Correct 122 65.2
Signs and symptoms of snake bites are determined by the type of snake responsible for the bite. (Yes) Incorrect 41 21.9 0.78 ± 0.416 78.0
Correct 145 77.5
State 3 local symptoms and signs you will see on the part of the human body bitten by a snake.c 0/3 4 2.1 2.78 ± 0.612 93.0
1/3 7 3.7
2/3 14 7.5
3/3 161 86.1
State 3 general or systemic signs and symptoms that may be exhibited by a venomous snake bite victim.d 0/3 20 10.7 2.12 ± 1.030 71.0
1/3 28 15.0
2/3 47 25.1
3/3 91 48.7
Out of ONE HUNDRED (100) snake bites, what percent may come from venomous snakes? (30) Incorrect 184 98.4 0.01 ± 0.103 1.1
Correct 2 1.1
Out of ONE HUNDRED (100) bites by venomous snakes, how many times do you think venom will be injected into the victim? (50) Incorrect 161 86.1 0.13 ± 0.342 13.4
Correct 25 13.4
The signs and symptoms of snake bite depends on the amount of venom injected by the snake. (Yes) Incorrect 73 39.0 0.61 ± 0.490 60.4
Correct 113 60.4
What time of the day do you think snake bites are most common? (During the day) Incorrect 117 62.6 0.37 ± 0.484 37.0
Correct 69 36.9
Which season in Ghana is snake bites most common? (Rainy) Incorrect 47 25.1 0.75 ± 0.436 74.3
Correct 139 74.3
When you are walking in the forest or farm and you come across a log of wood across your path, what would be the best thing to do prevent being bitten possibly by a snake? e Incorrect 165 88.2 0.11 ± 0.317 11.2
Correct 21 11.2
Overall mean score 13.78 ± 4.000/22 (63%)

aKeep grass short or the ground clear around your house; Clear underneath low bushes to close to the house; Avoid keeping livestock in the house; Store food in rat- proof containers; Do not have tree branches touching your house; Use a light and proper shoe when walking at night; Clear heaps of rubbish from near your house. bSigns and symptoms. cPain, swelling, fang marks, blisters formation, swollen lymph nodes draining the site, local bruising and bleeding, redness of the site. dBleeding and clotting disorders, dizziness, blurred vision, and syncope which may occur as a result of hypotension after the bite, Transient paraesthesiae of the tongue and lips, heaviness of the eyelid, nausea and vomiting, bilateral ptosis, respiratory and generalized flaccid paralysis. eStep/walk on it. Correct answers are in parenthesis ( ) at the end of the question.

Association between Socio-Demographic Characteristics and Knowledge on Snakebite

Table 5 shows association between socio-demographic characteristics and knowledge on snakebite. Male respondents had a better means knowledge score on snakebites than their female counterparts (14.49 vs. 13.03) but the difference was not significant. Respondents from the CHPS compound significantly scored better than respondents from the health centres and hospitals (16.6 > 14.84 > 13.31; p < 0.03). Respondents from Central Tongu obtained the highest mean score, (14.36) on knowledge about snakebite, followed by North Tongu (14.28) and South Tongu scored the lowest (13.17) but the differences were not significant. Pharmacists and medical doctors significantly scored better than Physicians assistants (PAs), Pharmacist technicians, Community health nurses/Enrolled nurses (CHN/ENs) and Registered general nurses (RGNs) on knowledge on snakebite (p 15.09 > 13.35; p < 0.020). Respondents who had training on snakebite management significantly scored better than those who had not received training on snakebite management (15.60 vs. 12.98; p < 0.0001). There was no significant association between number of years of practice and knowledge on snakebite management. Respondents with more than 10 years of practice obtained the best mean score of 15.50, followed by < 5 years (14.13) and lastly 5-10 years (13.18) but the differences were not significant.

Table 5: Association between socio-demographic characteristics and knowledge on snakebite.

Characteristic Sub-group Mean Score + SD P-value
Sex Male 14.49 ± 3.670 0.12
Female 13.03 ± 4.210
Type of health facility CHPS compound 16.60 ± 4.290 0.03*
Health centre 14.84 ± 5.088
Hospital 13.31 ± 3.621
District of health facility South Tongu 13.17 ± 3.593 0.152
Central Tongu 14.36 ± 4.107
North Tongu 14.28 ± 4.444
Area of profession RGN 12.80 ± 3.107 0.023*
Pharmacist 16.50 ± 3.416
Medical officer 16.50 ± 2.739
Physician assistant 14.05 ± 3.908
CHN/EN 13.96 ± 4.528
Pharmacy technician 15.40 ± 6.693
Registered midwife 14.27 ± 5.325
Professional group Nursing and midwifery group 13.35 ± 3.921 0.020*
Prescribers 15.89 ± 5.207
Pharmacy group 15.09 ± 3.625
Training No training 12.98 ± 3.686 <0.001*
Received training 15.60 ± 4.118
Number of years of practice <5 years 14.13 ± 4.186 0.240
5-10 years 13.18 ± 3.386
>10 years 15.50 ± 2.121

*Statistically significant.

Discussion

The findings from the study showed that, majority, 95 (51.1%) of the respondents were males to similar studies in Nigeria and Cameroun but different from the study in Laos [10-12]. This could be because in Ghana, health care professional groups (medical doctors, pharmacists and pharmacy technicians, physician assistants) in exception of the nursing and midwifery profession are dominated by males although presently there are more males in the nursing profession than it used to be some years ago. Most of the respondents were within the age groups 30-39 years (52.7%)) and 20-29 years (43.3%). This age groups fall within the group considered to be the working age group (15 years and above) in Ghana by the Ghana Statistical Service (GSS) [9]. It is therefore not surprising that majority of health care professionals in the three districts are of a youthful age group. The result of the study also showed that the South Tongu district recorded the highest number of respondents, 87 (46.8%) in the study. This was because the South Tongu district has two main hospitals (the District hospital and Comboni hospital) and more health centres and CHPS compounds combined than the North and South Tongu districts. The results on the number of years of practice revealed that 112 (60.2%) of the respondents form the majority with less than five years of practice. This result corresponded with the findings of Michael et al. (2018) where 66.3% of the respondents were with < 10 years working experience. This could be due to the reason that most professionals who had served for more than five years had gone to further their studies as health professionals in Ghana are granted study leave after working for a period of 3 to 5 years. The study also revealed that majority, 146 (78.5%) worked at the hospitals while to 25 (13.4%) and 15 (8.1%) worked in the health centres and CHPS compound respectively. This is because the hospitals have larger number of health care professionals than the lower level health facilities. The nursing group (RGN: 43% and EN/CHN: 26.3%) formed the most common group of health workers in the study because of their dominance in terms of numbers in every health facility in Ghana. This result is in contrast with a similar study conducted in Lao People Democratic Republic (Lao PDR) and Cameroun where physicians formed the majority of the respondents [11,12]. The difference clearly could be the difference in the settings of the different studies and target groups involved in these studies.

The overall average knowledge score rated by the respondents on knowledge on snakes in the study was 46.2%. This score shows that the health care providers performed below average in the assessment of their knowledge about snakes. Health professionals were least knowledgeable about identity of various species of snakes. Similar study done in India [13] revealed that 65% of the respondents had poor information about snake identification. Similar studies in Lao, Nigeria and Cameroun also found health professional exhibiting poor knowledge on identification of snakes [10-12]. This means the health training schools in many countries do not have enough materials on snakes and snakebites and even after graduation, not many health authorities organize in-service training on snakes and snake bite management. This is of a great concern because, to be able to determine whether envenoming could occur or had occurred after a snakebite, the health care professionals need to identify the type of snake involved in the bite if brought along or upon description by victim or relatives. Knowing that the offending snake species is venomous, partially venomous or nonvenomous will guide the health care professional on how best to manage the condition and whether it will be necessary to administer anti-snake venom which is usually difficult to get in many countries. Despite the low overall level of knowledge, male health workers possess a significantly better knowledge on snakes than females. The difference in knowledge score between the sexes on snakes could possibly be because women generally fear snakes and would do everything to avoid issues concerning snakes [14]. The reason why health care providers working in the lowest part of the health system (CHPS zones and health centres) had better score on knowledge on snakes than those working in the higher level (hospitals) could be because since they work in more rural communities where snakes are more common, they will invariably be more familiar with snake species than those from the facilities located in the bigger towns where encounters with snakes are less common. The results of this study also showed that the prescribers (medical officers and physician assistants) and the pharmacy group (pharmacists and pharmacy technicians) had better knowledge on snakes than the nurses and midwives just as reported in the Cameroonian study [11]. These differences in knowledge between these groups of health care professionals could be because the prescribers and the pharmacy professionals may have had more training on snakebite management than the nurses and the midwives. Again, the prescribers also play important role in the management of snakebites while the pharmacy personnel supply the medications but the involvement of a nurse in the snakebite issues depended on his or her area of work. The study showed a high level of knowledge among the health care professionals on the local signs and symptoms (93.0%) and preventive measures (84.0) of snakebites. These results corroborated the findings in a similar study in Northern Nigeria where respondents scored 62.3% on clinical features of snakebite and 97.1% on preventive measures [10]. The reason that could account for the high level of knowledge among the health care professional on the local sign and symptoms of snakebite could be that most of them have severally seen victims of snakebite reporting to the health facility presenting with these signs and symptoms. The study also revealed that majority (74.3%) of the respondents knew that snake bites occur more often during the rainy season in Ghana. The high knowledge on the season with the most prevalence of snakebite may be because during the rainy season, the number of snake bite cases reporting to the health facilities increases as compared to the dry season. The overall average knowledge score of 63.0% on the knowledge about snakebite is an indication of some deficit in knowledge of health care professionals in the Tongu districts about snakebites. The overall knowledge score on snakebite is a little higher (63.0% vs. 52.9%) than what was recorded in the study conducted among physicians in Northern Nigeria [10]. A study in Cameroon also recorded poor knowledge on snake bites among health professionals [11]. This study therefore reveals a yawning gap between what our health care professionals should know and what they know about snakes and snake bites which will compromise their management of victims of snake bites. If health workers in rural environments where more snake bites will be reported seem to possess such low level of knowledge about consequences and management of effects of human snake conflict, then it can be extrapolated to mean than health practitioners in urban areas will be more deficient in snake bite management. This study however had some limitations worth noting. This study was conducted in only three out of about two hundred and sixty districts of Ghana so may not represent the situation across the country. Again, since convenience sampling was used in the selection of the nursing professionals, there may be some biases in their selection which can affect the generalization of the results of this study. Despite these limitations, the outcomes of this study being the first of its kind in Ghana, should cause health policy-makers to provide more in-service training on snakes and snake bites to all health workers so as to bridge the gap of knowledge deficit. Again, health training institutions should include snake bites issues in their academic curricula so that their trainees will be adequately equipped to help reduce morbidity and mortality associated with snake bites after graduation.

Conclusion

This study had shown some inadequacies in knowledge regarding snakes and snakebites among health care professional in the three Tongu districts of the Volta region of Ghana. Since in-service training was associated with respondents’ knowledge on snakes and snakebite, there is a clear need for improvement in knowledge about snakes and snakebites among health workers in the three Tongu districts and across the Ghana.

Acknowledgement

We wish to acknowledge the support of heads of health facilities where the data was collected for granting the permission for the study to be conducted in their health institutions. We also acknowledge the support given the team of researchers by health workers in the North, Central and South Tongu districts of the Volta region. The authors had no conflict of interest in this research since the study was funded by the researchers themselves.

References

    1. WHO Regional Office for Africa. Guidelines for the prevention and clinical management of snakebite in Africa: Mauritius. 2010. Retrieved April 15 2019 from
      http://afrolib.afro.who.int/documents/2010/En/Snakebite_guidelines.pdf.
    2. Habib AG. Public health aspects of snakebite care in West Africa: perspectives from Nigeria. Journal of Venomous Animals and Toxins including Tropical Diseases. 2013;19:1-4.
      https://doi.org/10.1371/journal.pntd.000671
    3. Prevalence of snakebite envenoming. 2019a. Retrieved June 5, 2019 from
      https://www.who.int/snakebites/epidemiology/en/
    4. Kasturiratne A, Wickremasinghe AR, de Silva N, Gunawardena NK, Pathmeswaran A, Premaratna R, Savioli L, Lalloo DG, de Silva HJ. The global burden of snakebite: a literature analysis and modelling based on regional estimates of envenoming and deaths. PLoS Med. 2008 Nov 4;5(11):e218.
    5. Snakebite envenoming. 2019b. Retrieved May 21, 2019 from
      https://www.who.int/snakebites/treatment/Diagnostic_tests_and_tools/en/
    6. Williams D, Gutiérrez JM, Harrison R, Warrell DA, White J, Winkel KD, Gopalakrishnakone P. The Global Snake Bite Initiative: an antidote for snake bite. The lancet. 2010 Jan 2;375(9708):89-91.
    7. Chippaux JP. Snakebite envenomation turns again into a neglected tropical disease! Journal of Venomous Animals and Toxins including Tropical Diseases. 2017 Dec;23(1):38.e218.
    8. Wingert WA, Chan L. Rattlesnake bites in southern California and rationale for recommended treatment. Western Journal of Medicine. 1988 Jan;148(1):37.
    9. Ghana Statistical Service.  Population and Housing Census Summary Results of Final. 2012. Retrieved July 17, 2019 from
      http://statsghana.gov.gh/gssmain/storage/img/marqueeupdater/Census2010_Summary_report_of_final_results.pdf
    10. Michael GC, Grema BA, Aliyu I, Alhaji MA, Lawal TO, Ibrahim H, Fikin AG, Gyaran FS, Kane KN, Thacher TD, Badamasi AK. Knowledge of venomous snakes, snakebite first aid, treatment, and prevention among clinicians in northern Nigeria: a cross-sectional multicentre study. Transactions of The Royal Society of Tropical Medicine and Hygiene. 2018 Feb 1;112(2):47-56.
    11. Taieb F, Dub T, Madec Y, Tondeur L, Chippaux JP, Lebreton M, Medang R, Foute FN, Tchoffo D, Potet J, Alcoba G. Knowledge, attitude and practices of snakebite management amongst health workers in Cameroon: Need for continuous training and capacity building. PLoS neglected tropical diseases. 2018 Oct 25;12(10):e0006716.
    12. Inthanomchanh V, Reyer JA, Blessmen J, Phrasisombath K, Yamamoto E, Hamajima N. Assessment of knowledge about snakebite management amongst healthcare providers in the provincial and two district hospitals in Savannakhet Province, Lao PDR. Nagoya journal of medical science. 2017 Aug;79(3):299.
    13. Pandve HT, Makan A, Kulkarni TA. Assessment of awareness regarding snakebites and its related issues among rural communities. SF J Pub Health. 2017;1(1).
    14. Rakison DH. Does women’s greater fear of snakes and spiders originate in infancy?. Evolution and Human Behavior. 2009 Nov 1;30(6):438-444.

Disease, Duration and Death

Abstract

Life has always been threaten by diseases, calamities, catastrophes leading to death caused by various known or unknown, animate or inanimate objects in human’s relatively medium life span. Ever since the documentation of the human history, it is well known that man loved their body and prefer to live in accordance with their wishes. When rationale judgment became prominent after the experiences and observations of life and death events, they started searching remedies such as medicine. This is how medicine evolved since our early civilization. With the development of reason, logic, observation, experimentation and practical application, we learned tremendous ways of saving body, brain and behavior. However, as time passes human environment changes unpredictably leading to change in human behavior and attitude towards objects/materials and living beings. It is not only a matter of physical, biological or cosmic change but also behavior of everything that brought unprecedented events such as unexpected war, epidemic, catastrophes etc. leading to death [1,2]. Measurement of several physical parameters of human and universal bodies has become routine but various functions/characters in relation to time has yet to measure fully. This is the point we fall short to save humans promptly resulting high number of unexpected loss of life such as in COVID-19 pandemic. Among 1554960 covid-19 infected population in more than 209 countries, territories and two conveyances 5.9% died, and among the deaths more than 80% occurring in just 10 countries (USA, Spain, Italy, Germany, France, China, Iran, UK, Belgium, Netherlands) of the world in the last three months duration [2].

Disease is an abnormal architecture/anatomy, function, condition of the body and mind in a specific duration. Many times and circumstances death occurs due to unprecedented cause, behavior or ignorance. Therefore, it is essential to know the unknown environment and diverse nature and behavior of human beings to diagnose epidemicity of the disease. Despite vast scientific discoveries and new achievement, there is a big hole in the measurement of core human behavior and intelligence. Human body, intelligence and behavior plays a great role in the defense mechanism as well as association in the causation, development, cessation of disease in specific duration in specific place/s. So far we are devoid of the precise knowledge on the creation of covid-19 however many scientists have been trying to explore the mystery of the occurrences, nature and impact on the human population of the globe [3].

The duration or natural course of illness or diseases is important in the management of cases, carrier as well as prevention of complications and death [4]. Alert researchers identify the key factors of the disease when there is sudden rise of cases of similar features in a short period. Ignorance about the nature of pathogen and ignorance of the general population about the disease leads to higher number of deaths in a very short duration. Lack of alertness in changing behavior and environment of the disease in the population further complicates its management and increases the number of deaths. The challenge of the new disease, ignorance on the part of environment and human behavior help to expand disease dimensions in terms of time, place and person.

Opportunities such as chance, experience, observation and experimentation lead to discovery and development of medicine and care system that can make our life easier, comfortable and lengthier. This is the beauty of medical discipline, research and practice in human population. A dynamic patience where a body and brain searches a remedy continuously in response to disease is probably the best stimulus to initiate new knowledge, skills, practice to cure patient and prevent death. Lack of precise knowledge of duration and the nature of the disease is biggest obstacles in managing covid-19 at present and many more diseases that are possible in the future. Following the spread of disease and management of the patient (source) meticulously in global environment, recording the evidences and continuous sharing among the fellow researchers and responsible individuals are the most important aspects of pandemic control.

Alertness, continuous searches, dynamic patience can help humans to increase its capacity to deal with covid-19 pandemic. Change in seasonality in different geographical regions may affect duration of the diseases and distribution of death in humans. This demands thinking globally and acting globally.

Keywords

Covid-19, Death, Disease, Duration, Pandemic

References

  1. Riedel S (2004) Biological warfare and bioterrorism: a historical review. BUMCProceedings17: 400-406. [crossref]
  2. Covid-19 Coronavirus Pandemic, Worldometer. Accessed on April 09, 2020, 16:30 GMT.
  3. Zhou P, Yang X, Wang X, Hu B, Zhang L, et al. (2020) A pneumonia outbreak associated with a new coronavirus of probable bat origin. Nature579: 270-273. [crossref]
  4. Rothan HA,ByrareddySN (2020) The epidemiology and pathogenesis of coronavirus disease (COVID-19) outbreak. Journal of Autoimmunity109: 102433. [crossref]

Mapping Contextual Drivers of HIV Vulnerability: A Qualitative Study of African, Caribbean, Black Youth in Windsor, Canada

Abstract

Background: Based on POWER study: Promoting and owning empowerment and resilience among African, Caribbean, and Black Canadian (ACB) youth, this paper explored the contextual factors that expose ACB youth to HIV infection.

Method: We conducted six focused community-mapping sessions with 43 purposively drawn ACB youth living in Windsor, Canada. Based on socio-environmental approach, we investigated a number of issues including, where to find ACB people, places afraid to go, places to find casual partners, where they spend leisure time, healthy and unhealthy places.

Results: The findings showed that ACB population mainly resides in poor areas, with close proximity to bars, strip shops, recreational/sports places. And, multifaceted factors, such as economic deprivation, marginalization, discrimination, and substance use provided an enabling environment for ACB youth exposure to HIV/AIDS. Conclusion: Future HIV/AIDS prevention must be locality specific and culturally sensitive, by taking into account individual, structural, environmental and socio-cultural factors in future HIV prevention strategies.

Keywords

HIV/AIDS, ACB youth, Community mapping, Contextual factors

Introduction

According to 2018 HIV surveillance report in Canada, Ontario accounted for the highest population of HIV cases (39.2%), with the second highest reported cases among 20-29 at 22.5% Gay, bisexual and men who have sex with men (gbMSM) continue to account for the highest exposure to HIV 58.1%, while heterosexual transmission accounts for 32.3%, of which 15.4% are from HIV endemic countries [1]. Similarly in 2017, Ontario accounted for the highest population of new HIV cases (38.9%), and ACB people infected with HIV through heterosexual contact account for 20% of the estimated total of all HIV-positive people, and youth aged 15 to 29 accounted for 23% of HIV cases, and between 2016 to 2017 a 17% increase in 15 to 19 and 4% decrease among 20 to 29 [2]. More so, the Black population, which makes up 3.9% of the population accounts for 22.5% of persons living with HIV in the province [3]. It also has been estimated that in Ontario, Windsor diagnosis of HIV new cases of 5.7 was fifth, with Toronto having the highest diagnosis rate of 15.7 [4].

Community-based and participatory action research programs on HIV/AIDS risk behaviors have reported that mapping of locations with high concentrations of bars, shops, strip clubs, trucking places, sex workers and other geographical places is crucial in identifying at-risk places, groups, as well as, in designing and implementing effective and sustainable HIV prevention interventions [5]. Community mapping has been used to address development and health issues across multidisciplinary sectors, particularly health issues like infectious diseases [6-8] and HIV/AIDS [9,10]. Other focus of community mapping includes HIV prevention intervention [11,12], and health promotion [13], sex and HIV education [14].

However, mapping as a social research approach has become a growing basis for many interventions in developing countries/contexts, on development interventions to promote HIV prevention [15-17]. Community mapping is a mixed method approach that involves brainstorming and geographical mapping to visually present ACB youth ideas and perceptions of their vulnerability and resilience to HIV/AIDS. Participants actively participated in ensuring that the maps are explicit, representing and providing adequate knowledge that represents the diverse views of participants.

The present paper explores the factors that expose young ACB youth to HIV infection in a border city, Windsor, Ontario Canada. It focuses on individual, interpersonal, societal and environmental factors (e.g. access to resources, oppression, discrimination, poverty, and racism) that are often beyond the control of individuals [18-21].

Theoretical Perspectives

Based on socio-environmental approach, this paper recognizes that individual and collective health are intertwined, such that health disparities are the outcomes of intersecting social determinants including neighborhoods, access to economic and social resources, everyday encounters of discrimination and racism, and social exclusion [22]. Integral to this paper are the concepts of masculinity and vulnerabilities. According to UNAIDS [23], people’s vulnerability to HIV depends on their personal circumstances, societal factors such as disempowering cultural practices and laws, and the extent to which they have access to appropriate services and supports. However, the UNAIDS definition of HIV vulnerability neglects the role of structural determinants, such as various forms of social oppression, deprivation, and poverty [24]. This paper measures vulnerability in terms of individual attributes such as self-esteem, personal competence, optimism, and related attributes. The focus on individual factors makes invisible those situational and socio-environmental factors (e.g. cultural safety, access to resources, social capital, intergenerational trauma) that are often beyond the control of individuals [21].

Methodology

Study Community

Windsor, located in southwestern region of Ontario, and has also been identified as has one the highest rates of immigrants proportional to its population, having the sixth largest concentration of people who have ancestral ties to Africa [25]. According to Statistics Canada (2011) [26], Windsor has the highest proportion (33.3%) of low-income population living in very low-income neighborhoods. Windsor with the fifth highest HIV diagnosis rate (5.7) among new cases is also a border town with Detroit, Michigan, USA, which has 603 positive sero-status persons per 100,000 people [27]. In addition, its low legal age for alcohol and tobacco consumption, attracts young Americans to visit Windsor bars regularly on weekends and has opened more avenues for social and sexual networking [28]. This networking is likely to create unique local issues. Therefore, it becomes crucial to conduct a study that focuses on Windsor because issues such as youth’s and parents’ socioeconomic status, inter-country migration or mobility, social hubs, and diversity may nurture cross-border politics and relations.

This study is based on the community mapping of a larger CIHR (2009-2012) funded project on “Promoting and owning empowerment and resilience among African, Caribbean and Black youth in Windsor (POWER)”. Engagement process began by organizing a public forum for ACB youth and community based organizations and stakeholders. At the public forum, we developed a list of volunteers to serve in the Youth Advisory Committee (YAC). YAC became a bridge that links the project to the study communities, target population (youth) and promoted participatory involvement of youth at all levels of the research process. We provided a brief overview of the project and particularly the community-based approach that focus on partnering with the communities and target group as significant actors in the project implementation.

Data Collection

Two investigators and three staff undertook six focused community mapping group sessions between May and November 2015 with 18-24 years ACB youth living in Windsor. The six group sessions comprised of Youth Advisory Committee (YAC) of university of Windsor students (7), St Claire College (7), Caribbean non-students (7), Black non-students (8) and African non-student (7). Purposive sampling was used to recruit a total of 43 participants. Each group session comprised of homogenous participants in terms of racial/ethnic groups and student status. Two project staff facilitated after being trained over one-week training on community mapping. Each focused group session included seven to eight participants of the same ethno-racial group organizations and student status. Two staff and one investigator facilitated the focused sessions. To begin each session, facilitators introduced the community mapping methodology, including a de-briefing on what the project purpose and goals. Facilitators used a focused semi-structured guide containing prompt questions to lead the discussions, exploring commonalities and differences across the conversation. After each session, the project team debriefed with facilitators, providing additional coaching on issues or ideas that arose during the session. Going around the table, each participant was giving the opportunity to contribute to the discussions. Participants were provided with sticky notes to put down their response if too shy to speak out. Participants had ample uninterrupted time to respond promptly. Participants as a group placed some of their answers on the map of Windsor. Each session lasted between 90 and 120 minutes. The language of communication was English. We took notes and audio taped the discussions. We served snacks and paid participants stipend of $25, which included $5 for transportation.

Data Analysis

The staff transcribed the audio recordings verbatim. Two investigators verified the transcripts for accuracy. Project coordinator created the codebook used for coding the transcripts. We used pattern coding by Miles and Huberman (1991) to summarize each transcript. Codes were compiled to record the experiences and perceptions of barriers that tend to expose ACB youth to HIV/AIDS. Staff and two investigators re-examined the coded transcripts for accuracy. And, N6 qualitative software, online coding and data management was used to organize and code the transcripts. The coding process resulted in the identification of the data supporting the emergent themes and the corresponding quotations buttressing the arguments. We made a table of emergent themes, sub-themes and corresponding quotations, which was further reviewed by staff and one investigator for validation. The team overseeing the community mapping read and re-read the themes against the quotations to identify the pattern of arguments.

Results and Discussion

Background of Participants

Table 1 shows that participants of African heritage make up the majority (51.2 percent), those of Black heritage were 23.3%, while Caribbean were 20.9% and only 4.6% classified themselves as of mixed heritage. Additionally, in terms of gender, males were 55.8% and females were 19%. All the sessions were held in a place of close proximity to the participants. For example for university of Windsor and St. Claire College, the sessions were held in the two campuses, while others tended to be held at downtown Windsor.

Table 1: Participants’ Background Characteristics.

Characteristics

Frequency

Percent

Race/Ethnicity (N= 43)

No.


African

22

51.2

Black

10

23.3

Caribbean

9

20.9

Mixed

2

4.6

Gender (N=43)
Female

19

44.2

Male

24

55.8

Places to Find ACB People

The study probed for the places where ACB people commonly lived. The participants reported that ACB people commonly resided in places where there were affordable housing, with close proximity to social institutions and amenities such as schools, recreations centers. Government provided most of affordable housing tailored to income of tenants. Public maintenance of these housings was timely and at no extra cost to the tenant. More importantly, it was a common practice for newcomers to seek and identify residential places populated by ACB people. Participants identified the west, around sandwich, central and downtown areas as the places to find most ACB people, while they are sparsely located in South Wood Lake area, where the wealthy and affluent ACB families reside. More ACB people are congregated in the west end/Sandwich, central and downtown, which are crime and poverty-ridden areas. They also noted that a high population of ACB youth, as students, wage earners and those not gainfully employed resided in these areas, either alone or with parents/guardians. Participants also reported a number of social vices such as availability and accessibility to drugs like marijuana, partying, and sex work, which are common around affordable housing places. These social vices expose ACB youth to risk behavior and HIV infection.

In terms of their opinion on living in these places, there were varied ideas. In the Black Canadian mapping session, participants described these areas as: Dirty, lot of prostitutes, Rough area that used to be more violent back in (10), it’s a bad area, prostitution, people get robbed beat up all the time (13), it’s so retched, ghetto, lots of poverty, No money or jobs are here, A lot of drugs and violence.

The YAC Group Noted That

There are a lot of young people; a lot of influence, peer pressure, drugs, sports, unprotected sex, good or poor academics, some of the neighborhoods are associated with public housing, immigrant settlement, Glengarry has a waterpark, STAG, community centers, where people can go, ———————, black people are excluded from networking (union)

In the University Students’ Session, a Participant Noted

Relatively impoverished; roads and everything is poorly cared; not much of the city funds go there; a little dangerous; its more affordable; but there is always some type of altercation on my lawn or across the street; I just assumed I would find something more affordable in West Windsor; familiar; they might also feel they can find someone they can relate to (Female Caribbean).

While in the Non-student Group Session, a Participant Added

Black people are spread out in little areas; West Windsor; bad; but I think it is inclusive, culturally sensitive a good place; unkempt; drugs, boarded houses; not true; there is Windsor housing for immigrants.

Discrimination and Contact with the Police

Despite the importance of social networking with friends and peers, participants reported that the presence of ACB youth in predominantly white residential neighborhoods at out-skirts of Windsor, high-end stores, and electronic sections/units of departmental stores, grocery stores and around police stations raises suspicion. Other places identified where teen health center and blood clinic (cited by University group), and prisons (African non-students). The common reasons provided for avoiding these areas are to avoid confrontations with the police, and confrontations involving wrong identity. Participant noted that “If a conflict/confrontation occurs- automatically the Black person(s) will be confronted even though the fight was from another race” (African female session). Other youth reported that “violence and crime” are high at downtown Windsor, and ACB youth are often the first suspects.

Participants also reiterated their experiences with the police in a number of places such as residential areas around downtown, west end, university areas; clubs – Boom Boom, house parties; highways and other places such as the mall and stores. Often such encounters with peers and relatives end up as mistaken identity, or it involves highway offense and road checks. A youth noted that with police in Windsor, “they think all Blacks look alike” (African Female, AF). A participant reported that there was a time when a “girl’s house was robbed; a dozen police car were present, the last one had a gun pulled out, stopped us for an hour, asked foolish questions, and said you fit the description”.

A participant also noted an incident downtown, where ACB boys were hanging out at “McDonalds with white girls, cops harassed us, told us to go home or be arrested for loitering, and promised to call the girl’s parents.” Police officers would stop an ACB youth and say, “Are you up to something? Are you from Somalia?” (African Male) A student participant also noted: “walking home from university, 20 minutes-walk from home, 2am I was questioned about seeing someone in the area” (AM).

Where do Youth Spend their Free Time?

In response to the question, “where do youth spend their free time?” participants highlighted a number of places in west of Windsor, such as Sandwich and downtown areas where ACB youth most frequently spend their free time. These places included bars, clubs, strip shops, parks, and sport centers like St. Denis center at the University of Windsor and YMCA, house parties, malls, University library – Leddy and at the theaters. These were common meeting places where they engage in social and sexual networking with each other. Data also showed gender differences as males frequented more places for sports and clubbing, while females tended to patronize places that are less costly, for dancing and were often in company with older siblings and friends. During the walking tours of these areas, the research team and staff were informed that other ACB youth residing in other places in Windsor tended to visit and congregate in these areas to be in company of other peers and friends. We also probed for healthy and unhealthy places in Windsor. The participants reported diverse settings. The healthy places ranged from sport places like gyms at YMCA and St. Denis of the University of Windsor; leisure places like STAG, water front located at downtown Windsor; faith-based institutions-churches and mosques, NGO offices like Windsor Women Working With Immigrant Women, Women Entrepreneur Skills Training, New Canadian Center for Excellence, AIDS Committee of Windsor, Youth Connection Association, Salvation Army, and community centers like STAG, Caribbean center. For these youth, these places provided low cost services and were safe and fun places. However, they noted that unhealthy places included parks; downtown area, street allies, and places where many sex workers line the streets, and house parties. The reasons provided ranges from availability of drugs, sexual networking, and exposure to unhealthy behaviors such as sexual activities, drugs and despicable behaviors such as sexing in public places like parks. A participant in identifying what makes these places unhealthy said: Downtown; drugs and alcohol; white women approach Black men; border city; girls from Cincinnati, Pittsburgh, Detroit; 1 in 4 Americans have an STI; Black women give stink eye because it’s not healthy (sexually networking with men who have exposed themselves to “risky” White women); strip clubs; studio 4; Teasers; human and drug trafficking; leopards owns 2 houses; keep green cards in safe; European girls; you don’t know what they have; police department; racial profiling; west end (street level crime); university of Windsor; break ins and misdemeanours (Caribbean Black Male).

Where to Find Casual Sex Partners

Participants identified downtown area and facilities -bars, strip clubs, house parties, Studio 4, casino, riverside after hour, massage parlors, parking lots, university library and residences, High school, St Clair, workplaces – factories, street corners – next to Bistro, shops – sex shops (Maxine, Dougall), residential Areas – condos downtown, restaurants – McDonalds (Escorts) as places to find casual sex partners. These places have close proximity to places where ACB people reside provided easy access to “alcohol and casual sexual activity” (African Female, AF). A participant in the University community mapping session said:

You will be surprised at what goes on at this campus. A friend finds a message at Leddy “for a good time call this number” (African Male, AM).

Another participant added, “campus for variety and safety” (African Female, AF)

A participant from the university also said:

AM: bars, strip clubs; university (you would be surprised at what goes on at this campus); speaks about friend who finds a message at Leddy; “for a good time call this number; meet at a house;” (African Male, AM)

Silvers on Seminole, Casino (Caribbean Female, CF).

Secret Places for Secret Things

To the probe on the secret places where ACB visit and/or congregate to do secret things, not to be heard or known by their parents/guardians, the participants reported bars/s clubs, located in the Sandwich and downtown areas, and specifically university and college campuses where a variety of activities occurred including “alcohol and casual sexual activity” (AF), and youth solicitation for sexual activity. Other activities included drugs, illicit sex, unsafe sex, and prostitution, which are unhealthy and expose persons to STIs including HIV/AIDS. The common reason given for engaging in these activities at these places is that they are “away from home and parents and no need to keep good name”.

P4 AF: residence; houses near campus; sell drugs; Askin street near the university; friends of friends; word of mouth

P1 BM: university; residence; college life involves it; alcohol and weed; houses right by campus

P6 CF: apartments on Peter Street; people come in and out at odd hours

P5 ACF: parks; accessible for sex and drugs

P7 AM; coronation school pike park; when house party ends, can go there to be loud or drink

CBM: Riverfront (car sex); hotels on Huron church (strippers from Ottawa, nova scotia); downtown Windsor condos by police station (drugs); Wyandotte and Windermere (S and M club); massage parlours downtown; houses in west end (coke spots); south Windsor (behind Devonshire mall area; cocaine); Banwell (ecstasy).

Discussion

Community mapping sessions and walking tours provided the researchers and staff a journey into the lived experiences and observations of ACB youth in Windsor, Ontario. The common thread in these accounts and activities was the social inequality, which was more along racial lines that tended to create social exclusion, perpetuating feelings of discrimination and overt racism, which have been reported to have serious impact on ACB communities particularly youth [18,19,29,30] and their attitude to the police [31]. Although these experiences results in lack of entitlement and privilege, thus threatening the social existential survival of ACB population, particularly youth, the community mapping strategies, gave back to these youth some elements of power not just as research participants but also as researchers in the front drive of data collection, informing and making contributions to all stages in the project.

The findings that neighborhoods’ context and organization promote ACB youth vulnerability to HIV infection has been buttressed by similar findings from existing studies from the United States and Canada depicting the influence of neighborhood environment and social disorder [19,20,32] neighborhood economic disadvantage [33-35] on HIV exposure.

The study also reported that the proliferation of some neighborhoods densely populated by ACB populations with bars, street allies, abandoned houses, availability and accessibility to drugs and alcohol, perpetuate risky behaviors like drug and alcohol use, accessibility and availability of female sex workers. Of significance is the report by participants that there have been rape cases of male and female victims in such neighborhoods due to bad people hiding in abandoned properties, and coercing or luring young persons and children into such places. Similarly, a few studies [36-38] suggest that physical environment influences sexual risk and HIV vulnerability. For instance [36], study notes that characteristics of the urban environment influence a wide variety of health behaviors and disease outcomes. They contend that the physical, social and cultural characteristics of urban environment have tolerant social policies through which behaviors and identities may be enacted with less fear. Also noted that inadequately housed individuals tend to be socially isolated or involved in networks that support risky behaviors such as drug use, unstable intimate relationships, multiple sex partners, casual sex exchange and low rates of marriage [39].

The present study also found that a majority of ACB population resides in affordable housing for low to medium very income people families. According to Statistics Canada (2011) [26], Windsor as a town has the highest proportion of low-income populations living in very low-income neighborhoods. Research evidence also shows that people living in very low-income neighborhoods appear to have higher HIV risk profile than those living in higher income areas [18]. Similarly, studies from North America also bear credence to the findings by its association of poverty from social and economic deprivation with HIV risk behaviors [39,40].

Of great importance are past evidence that local bars in Windsor, which attracts youth across the border due to its lower age for alcohol consumption increases the scope of social and sexual networking among Canadian and American youth [28]. Noting that the HIV prevalence rate is very high across Windsor’s border city of Detroit (35 new cases per 100,000 residents), and coupled with the early initiation of sex in youth and the poor attitude to and low use of condoms [27,41] the networking between the two cities is likely to increase the exposure of youth to HIV infection. In addition, participants reported going to hidden places away from parents and homes to use drugs, party and indulge in sexual activity. These findings have been documented in other empirical studies showing that young boys and girls use drugs like marijuana and alcohol, which may affect their decision-making [42], and invariable lead to risky behaviors including anal sex [43-46], violence [47-51], unprotected sex [52], and having casual and/or opportunistic sex [53-58].

Finally, low parent-child communication on sex also matters. It has been well documented that there is lack of sex talks in families and particularly between parents and children [59-61]. This gap exposes younger ACB youth to risky sexual behaviors such as low condom use and ability to negotiate sex, which has been reported to have serious sexual and reproductive heath consequences like exposure to sexually transmitted infections including HIV/AIDS. However, existing studies on Caribbean population have shown parents willingness to talk about sex and related issues with children [62]. And, it has been reported that parents talk about sex with children leads to abstinence, postponement of sexual initiation, positive attitude to safe sex practices including condom use, and engagement in monogamous relationships [63-68]. Invariably, parent-child communication about sex better prepares children when faced with the decision to have or not to have sex [69]. On the contrary, other studies however reported that some parents feel talking about sex matters with their children and adolescents will introduce them into sexual activities and therefore, they avoid such conversations [64,70]. Although studies remain inconclusive on the outcomes of parent-child talk about sex matters, parental efficacy to improve effective parent-child communication about sex matters remains important [71-85].

Conclusion

For decades, many HIV prevention research focused on determining, planning and implementing interventions to address individual-level risk behaviors that expose individuals to HIV infection. This present study indicates the importance in examining the environment, social and cultural impediments influencing risky behaviors. African, Caribbean and Black youth in Windsor, specifically young men face pressure from parents and families on children to conform to the social and cultural gendered expectations that makes you a woman (practicing abstinence) and a real man, like being the provider, economically stable, having multiple sex partners, and engaging in unprotected sex, which invariably are likely to increase exposure to HIV infection. This gives credence to this study that engaged AB youth as both research participants and as researchers, through membership in the Youth Advisory Committee, and actively engaged in recruiting and participating in community mapping and walking tours. More future research need to adopt a mixed method approach, which includes community and/or concept mapping, and other qualitative methods like focus groups, in-depth interviews, photovoice, and questionnaire to study specific subgroups of ACB population like self-identified heterosexual ACB youth, men and women, on a broader scale, provincially or regionally. So doing, we will then be able to establish the differences and similarities across space, neighborhood, race/ethnic subgroups, religion, class and gender in the general population.

The mapping and construction of factors in the environment, neighborhoods, social and cultural contexts among ACB boys, men, girls and women would gain immensely from further investigations. Such interests may provide broader-based data on perceptions of HIV vulnerability, environment and neighborhood factors, with issues of masculinity, specifically perceptions of black masculinity and sexuality that affect sexual scripts, what having sex means, condom use decision making, opportunistic sex, and perceptions of HIV testing.

Furthermore, the findings from this study can begin to inform HIV prevention strategies among ACB youth on how best to increase HIV prevention services. Such programs will focus efforts on addressing multi-level factors by adopting multidimensional, effective and sustainable interventions, which address individual, social, cultural and environmental risky behaviors, like unsafe sexual practices (having multiple sex partners, lack of effective condom use), while also addressing and implementing policies and interventions to improve the environment, neighborhoods, and socio-cultural factors like perceptions of a real black man that hamper the delivery of HIV services aimed at buttressing the sexual and reproductive health of ACB population, specifically youth.

Acknowledgements

Canadian Institutes of Health Research (CIHR) provided the funding. The ACBY team includes Kenny Gbadebo, Youth Connection Association; Eleanor Maticka-Tyndale, University of Windsor; Valerie Pierre-Pierre, African Caribbean Council of HIV in Ontario; Robb Travers, Wilfrid Laurier University; Jelani Kerr, University of Louisville, Louisville, KY. Thanks to the study participants for their contribution. The content is solely the responsibility of the author.

References

  1. Haddad N, Robert A, Weeks A, Popovic N, Siu W, et al. (2019) HIV in Canada-Surveillance Report, 2018. Canadian Communicable Respiratory Diseases 45: 304-312. [crossref]
  2. Haddad N, Li JS, Totten S, McGuire M (2018) HIV in Canada-surveillance report, 2017. Centre for Communicable Diseases Research (CCDR) 44: 348-356. [crossref]
  3. Wilton J, Liu J, Sullivan A, Sider D, Kroch A (2017) New HIV diagnoses in Ontario: Preliminary Update, 2016. Ontario HIV Epidemiology and Surveillance Initiative, Toronto, Ontario, October 2017.
  4. OHESI Ontario HIV Epidemiology and Surveillance Initiative 2018. HIV in Ontario by public health unit: Testing, new diagnoses and care cascade. November 2018. Toronto, Canada.
  5. Campbell C, Foulis C, Maimane S, Sibiya Z (2005) I have an evil child in my house: Stigma and HIV/AIDS management in a South African Community. American Journal of Public Health 95: 808-815. [crossref]
  6. Pigott DM, Golding N, Mylne A, Huang Z, Henry AJ, Weiss DJ, et al. (2015a) Mapping the zoonotic niche of Ebola virus disease in Africa. Transactions of the Royal Society of Tropical Medicine and Hygiene 109: 486-492. [crossref]
  7. Pigott DM, Golding N, Mylne A, Huang Z, Weiss DJ, et al (2015b). Mapping the zoonotic niche of Marburg virus disease in Africa. Transactions of the Royal Society of Tropical Medicine and Hygiene 109: 366-378. [crossref]
  8. Gagnon M, Guta A (2012) Mapping HIV community viral load: Space, power and the government of bodies. Critical Public Health 22: 471-483. [crossref]
  9. Dubois-Arber F, Jeannin A, Spencer B, Gervasoni J, Graz B, et al. (2010) Mapping HIV/STI behavioural surveillance in Europe. BMC Infectious Diseases 10: 290.
  10. Manda S, Masenyetse L, Cai B, Meyer R (2015) Mapping HIV prevalence using population and antenatal sentinel-based HIV surveys: a multi-stage approach. Population Health Metrics 13: 1-15.
  11. Lorway R, Khan S (2014) Reassembling epidemiology: Mapping, monitoring and making-up people in the context of HIV prevention in India. Social Science & Medicine 112: 51-62. [crossref]
  12. Corbie-Smith G, Akers A, Blumenthal C, Council B, M. Wynn, et al. (2010) Intervention mapping as a participatory approach to developing an HIV prevention intervention in rural African American communities. AIDS Education Prevention 22: 184-202. [crossref]
  13. Kruger DJ, Lewis Y, Schlemmer E (2010) Mapping a message for faith leaders: encouraging … Health Promotion Practice 11: 837-844. [crossref]
  14. Mpofu E, Mutepfa M, Hallfors D (2012) Mapping structural influences on sex and HIV education in church and secular schools. Evaluation and the Health Professions 35: 346-359. [crossref]
  15. Abdul-Quader AS, Collins C (2011) Identification of structural interventions for HIV/AIDS prevention: The concept mapping exercisePublic Health Reports 126: 777-788. [crossref]
  16. Ridings JW, Powell DM, Johnson JE, Pullie CJ, Jones CM, et al. (2008) Using concept mapping to promote community building:The African American initiative at RoselandJournal of Community Practice 16: 39-63.
  17. Ridings JW, Piedra LM, Capeles JC, Rodríguez R, Freire F (2010) Building a Latino youth program: Using concept mapping to identify community-based strategies for successJournal of Social Service Research 37: 34-49.
  18. Baidoobonso S, Bauer GR, Speechley KN, Lawson E (2013) HIV risk perception and distribution of HIV risk among African, Caribbean and Other Black people in a Canadian City: Mixed methods results from the BLACCH study. BMC Public Health 13: 184. [crossref]
  19. Kerr J, Maticka E -Tyndale, Bynum S, Mihan R (2017) Sexual networking and partner characteristics among single, African, Caribbean, and black youth in Windsor, Ontario. Archives of Sexual Behaviour 46: 1891-1899. [crossref]
  20. Kerr J, Northington T, Sockdjou T, Maticka-Tyndale E (2018) Perceived neighborhood quality and HIV-related stigma among African diasporic youth: Results from African,            Caribbean, and Black youth (ACBY) study. Journal of Health Care for the Poor and Underserved 29: 651-653. [crossref]
  21. Prince-Embury S, Courville T (2008) Comparison of one-, two-, and three-factor models of personal resiliency using the resiliency scales for children and adolescents. Canadian Journal of School Psychology 23: 11-25.
  22. Marmot M, Friel S, Bell R, TAJ Houweling, Taylor S (2008) Closing the gap in a generation: Health equity through action on the social determinants of health. Public Health 372: 1661-1669.
  23. Szekeres G (2008) The next 5 years of global HIV/AIDS policy: Critical gaps and strategies for effective responsesAIDS 22: S9-S17. [crossref]
  24. Doyal L, Anderson J, Paparini S (2009) ‘You are not yourself’: Exploring masculinities among heterosexual African men living with HIV in London. Social Science & Medicine S8: 1901-1907. [crossref]
  25. Maticka-Tyndale E, Kerr J, Mihan R, the ACBY Team (2016) A profile of the sexual experiences of African, Caribbean and Black Canadian youth in the context of Canadian youth sexuality. The Canadian Journal of Human Sexuality 25: 41-52.
  26. Statistics Canada 2011. Immigration and ethnocultural diversity in Canada: 2011 National household surveyCatalogue number 99-010-X2011001. Accessed June 3 2015.
  27. Michigan State Government (2015) Annual HIV Surveillance Report, Michigan. 2015. Lansing, MI: Michigan Department of Health and Human Services.
  28. Omorodion F, Gbadebo K, Ishak P (2007) HIV vulnerability and sexual risk among African youth in Windsor, Canada. Culture, Health & Sexuality 9: 429-437. [crossref]
  29. Bowleg L, Neilands TB, Tabb LP, Burkholder GJ, Malebranche DJ, et al. (2014) Neighborhood context and Black heterosexual men’s sexual HIV risk behaviors. AIDS Behaviour 18: 2207-2218. [crossref]
  30. Husbands W, Oakes W, Mbulaheni T, Ongoïba F, Pierre-Pierre V, et al. (2017) Resourceful masculinities: Exploring heterosexual Black men’s vulnerability to HIV in Ontario, Canada. Ethnicity & Health 25: 1-17. [crossref]
  31. Peirone A, Maticka E -Tyndale, Gbadebo K, Kerr J (2017) The social environment of daily life and perceptions of police and/or court discrimination among African, Caribbean, and Black Youth. Canadian Journal of Criminology and Criminal Justice 59: 346-372.
  32. Bowen A, Agboatwalla M, Luby S, Tobery T, Ayers T, et al. (2012) Improvements in child development following a cluster-randomized, controlled trial of intensive hand washing promotion in Karachi, Pakistan. Archives of Pediatrics and Adolescent Medicine 166: 1037-1044.
  33. Hyndman J, Holman J (2001) Accessibility and spatial distribution of general practice services in an Australian city by level of social disadvantage. Social Science and Medicine 53: 1599-1609. [crossref]
  34. Hendryx M, Ahern M, Lovrich N, McCurdy A (2002) Access to healthcare and community social capital. Health Services Research 37: 87-103.
  35. Kaukinen C, Fulcher C (2006) Mapping the social demography and location of HIV services across Toronto neighbourhoodsHealth and Social Care in the Community 14: 37-48. [crossref]
  36. Frye V, et al. (2006) The urban environment and sexual risk behavior among men who have sex with men. Journal of Urban Health 83: 308-324. [crossref]
  37. Marshall BDL (2008) The contextual determinants of sexually transmissible infections among street‐involved youth in North America. Culture, Health & Sexuality 10: 787-799. [crossref]
  38. Sanders T, Campbell R (2007) Designing out vulnerability, building in respect: violence, safety and sex work policy. British Journal of Sociology 58: 1-19. [crossref]
  39. Aidala AA, Lee G, Abramson DM, Messeri P, Siegler A (2007) Housing need, housing assistance and connection to HIV medical care. AIDS and Behaviour 11: S101-S115. [crossref]
  40. Adimora AA, Schoenbach VJ (2002) Contextual factors and the Black-White disparity in heterosexual HIV transmission. Epidemiology 13: 707-712. [crossref]
  41. Vincent W, Gordon DM, Campbell C, Ward NL, Albritton T, et al (2016) Adherence to traditionally masculine norms and condom-related beliefs: Emphasis on African American and Hispanic men. Psychology of Men & Masculinity 17: 42-53. [crossref]
  42. Wells BE, Kelly BC, Rendina HJ, Parsons JT (2016) Prescription drug misuse and sexual behavior among young adults. Journal of Sex Research 52: 659-668. [crossref]
  43. Jenness SM, Begier EM, Neaigus A, Murrill CS, Wendel T, et al. (2010) Unprotected anal intercourse and sexually transmitted diseases in high-risk heterosexual women. American Journal of Public Health 101: 745-750. [crossref]
  44. McBride KR, Fortenberry JD (2010) Heterosexual anal sexuality and anal sexual behaviours: A review. Journal of Sex Research 47: 123-136. [crossref]
  45. Baggaley RK, Dimitrov D, Owen BN, Pickles M, Butler AR, et al. (2014) Heterosexual anal intercourse: A neglected risk factor for HIV? American Journal of Reproductive Immunology 69: 95-105. [crossref]
  46. Marston C, Lewis R (2014) Anal heterosex among young people and implications for health promotion: A qualitative study in the UK. British Medical Journal 4: 1-7.
  47. Callands TA, Sipsma HL, Betancourt TS, Hansen NB (2013) Experiences and acceptance of intimate partner violence: Associations with sexually transmitted infection symptoms and ability to negotiate sexual safety among young Liberian women. Culture, Health & Sexuality 15: 680-694. [crossref]
  48. Casey EA, Quema K, Masters NT, Beadnell B, et al. (2016) Patterns of IPV and sexual behaviour among young heterosexually active men. Journal of Sex Research 53: 239-250. [crossref]
  49. Levesque S, Rodrique C, Beaulieu-Prevost D, Blais M, Boislard M, et al. (2016) Intimate partner violence, sexual assault, and reproductive health among university women. The Canadian Journal of Human Sexuality 25: 9-20.
  50. Moya EM, Chavez-Baray S, Martinez O (2014) Intimate partner violence and sexual health: Voices and images of Latina immigrant survivors in South-western United States. Health Promotion Practice 15: 881-893. [crossref]
  51. Stockman JK, Lucea MB, Draughon JE, Sabri B, Andersen JC, et al. (2013) Intimate partner violence and HIV risk factors among African-American and African-Caribbean women in clinic-based settings. AIDS Care 25: 472-480. [crossref]
  52. Roye CF, Krauss BJ, Silverman PL (2010) Prevalence and correlates of heterosexual anal intercourse among Black and Latina female adolescents Journal of the Association of Nurses in AIDS Care 21: 291-301. [crossref]
  53. Barnett JP, Maticka E -Tyndale, HP4RY (2011) The gift of agency: Sexual exchange scripts among Nigerian youth. Journal of Sex Research 48: 349-359. [crossref]
  54. Devries KM, Free C (2010) ‘I told him not to use condoms’: masculinities, femininities and sexual health of Aboriginal Canadian young people. Sociology of Health & Illness 32: 827-842. [crossref]
  55. Homma Y, Saewyc EM, Wong ST, Zumbo BD (2013) Sexual health and risk behaviour among East Asian adolescents in British Columbia. The Canadian Journal of Human Sexuality 22: 13-24. [crossref]
  56. Lavee E (2016) Exchanging sex for material resources: Reinforcement of gender and oppressive survival strategy. Women’s Studies International Forum 56: 83-91.
  57. Norbelius A, Kalina B, Pool B, Whitworth J, Chesters J, et al. (2010) ‘‘You still need to give her a token of appreciation’’: The meaning of the exchange of money in the sexual relationships of out-of-school adolescents in rural southwest Uganda. Journal of Sex Research 47: 490-503. [crossref]
  58. Poon C, Smith A, Saewyc E, McCreary Centre Society (2015) Sexual health of youth in BC. Vancouver, BC: McCreary Centre Society.
  59. Davis AN, Gahagan JC, George C (2013) Everyone just keeps their eyes closed and their fingers crossed: Sexual health communication among black parents and children in Nova Scotia, Canada. International Journal for Equity in Health 12: 55. [crossref]
  60. Izugbara CO, Undie C (2008) Masculinity scripts and the sexual vulnerability of male youth in Malawi. International Journal of Sexual Health 20: 281-294.
  61. Kuvalanka KA, Weiner JL, Mahan D (2014) Child, family, and community transformations: Findings from interviews with mothers of transgender girls. Journal of GLBT Family Studies 10: 354-379.
  62. Wang B, Stanton B, Deveaux L, X Li, Koci V, et al. (2014) The impact of parent involvement in an effective adolescent risk reduction intervention on sexual risk communication and adolescent outcomes. AIDS Education Prevention 26: 500-520.
  63. Blake SM, Simkin L, Ledsky R, Perkins C, Calabrese JM (2001) Effects of a parent-child communications intervention on young adolescents’ risk for early onset of sexual intercourse. Family Planning Perspectives 33: 52-61. [crossref]
  64. DiIorio C, Kelley M, Hockenberry-Eaton M (1999) Communication about sexual issues: Mothers, fathers, and friends. Journal of Adolescent Health 24: 181-189. [crossref]
  65. Ford CA, Pence BW, Miller WC, Resnick MD, Bearinger LH, et al. (2005) Predicting adolescents’ longitudinal risk for sexually transmitted infection: Results from the National Longitudinal Study of Adolescent Health. Archives of Pediatric Adolescent Medicine 159: 657-664. [crossref]
  66. McNeely C, Shew ML, Beuhring T, Sieving R, Miller BC, RVM Blum (2002) Mothers’ influence on the timing of first sex among 14- and 15-year-olds. Journal of Adolescent Health 31: 256-265. [crossref]
  67. O’Donnell L, Wilson-Simmons R, Dash K, Jeanbaptiste V, Myint UA, et al. (2007) Saving Sex for Later: developing a parent-child communication intervention to delay sexual initiation among young adolescents. Sex Education 7: 107-125.
  68. Zhang L, Li X, Shah IH, Baldwin W, Stanton B (2007) Parent-adolescent sex communication in China. The European Journal of Contraception & Reproductive Health Care: The Official Journal of the European Society of Contraception 12: 138-147. [crossref]
  69. Haffner DW, Tartaglione AH (2008) Beyond the big talk: Every parent’s guide to raising sexually healthy teens-from middle school to high school and beyond. New York, NY: Newmarket Press.
  70. Marcell AV, Ford CA, Pleck JH, Sonenstein FL (2007) Masculine beliefs, parental communication, and male adolescents’ health care use. Pediatrics 119: e966-e975. [crossref]
  71. Wyckoff SC, Miller KS, Forehand R, Bau JJ, Fastula A, et al. (2008) Patterns of sexuality communication between preadolescents and their mothers and fathers. Journal of Child & Family Studies 17: 649-662. [crossref]
  72. African and Caribbean Council on HIV/AIDS in Ontario (2013) Ontario HIV/AIDS strategy for African, Caribbean and Black communities 2013-2018. Toronto: African and Caribbean Council on HIV/AIDS in Ontario.
  73. Adimora AA, Schoenbach VJ, FEA Martinson, Coyne-Beasley T, Doherty I, et al. (2006) Heterosexually transmitted HIV infection among African Americans in North Carolina. Journal of Acquired Immune Deficiency Syndrome 41: 616-623. [crossref]
  74. Challacombe L (2016) The epidemiology of HIV in females. Accessed June 29.
  75. DiClemente RJ, Wingood GM, Crosby R, Cobb BK, Harrington K, et al. (2001) Parent- adolescent communication and sexual risk behaviours among African-American adolescent females. Journal of Pediatrics 139: 407-412. [crossref]
  76. Ford K, Wirawan DN, Muliawan P (2002) Social influence, AIDS/STD knowledge, and condom use among male clients of female sex workers in Bali. AIDS Education Prevention 14: 496-504. [crossref]
  77. Frisch M (2016) Higher frequency of unprotected insertive anal sex among young Black MSM who are circumcised. AIDS Behavior 20: 2543-2544. [crossref]
  78. Hess KL, DiNenno E, Sionean C, Ivy W, Paz-Bailey G (2016) Prevalence and correlates of heterosexual anal intercourse among men and women, 20 U.S. cities. AIDS Behavior 20: 2966-2975. [crossref]
  79. Hutchinson MK (2002) The influence of sexual risk communication between parents and daughters on sexual risk behaviour. Family Relations 51: 238-247.
  80. Hutchinson MK, Jemmott JB, Jemmott LS, Braverman P, Fong GT (2003) The role of mother-daughter sexual risk communication in reducing sexual risk behaviors among urban adolescent females: A prospective study. Journal of Adolescent Health 33: 98e107. [crossref]
  81. Kaul R, Cohen CR, Chege D, Yi TJ, Tharao W, McKinnon LR, et al. 2011. Biological factors that may contribute to regional and racial disparities in HIV prevalence. American Journal Reproductive Immunology 5: 317-324. [crossref]
  82. Miles M, Huberman A (1994) An expanded source book: Qualitative data analysis.(2nd ed). London: Sage.
  83. Remis R, Swantee C, Liu J (2012) Report on HIV/AIDS in Ontario 2009. Ontario HIV Epidemiologic Monitoring Unit.
  84. Tuckett A (2005) Part II: Rigour in qualitative research- complexities and solutions. Nurse Researcher 13: 29-42. [crossref]
  85. Vingilis E, McLeod AI, Seeley J, Mann R, Voas R, et al. (2006) The Impact of Ontario’s extended drinking hours on cross-border cities of Windsor and Detroit. Accident Analysis & Prevention 38: 63-70. [crossref]

Sources of Information and Health Care Experiences Related to COVID-19 among Women Involved in Criminal Legal System in Three U.S. Cities

Abstract

Women in the United States criminal legal (CL) system are at the nexus of several drivers of the COVID-19 pandemic, including incarceration, poverty, chronic illness and racism. There are 1.25 million women incarcerated or on community supervision (probation or parole) in the U.S. We present findings regarding the impact of COVID-19 on women in the CL system (N=344) during the early days of the pandemic. Participants were drawn from community settings in an ongoing study of cervical cancer risk in three U.S. cities: Birmingham, Alabama, Oakland, California and Kansas City, which straddles the states of Kansas and Missouri. Regional differences were found in COVID-19 testing and perceived susceptibility to the virus, but not in COVID-related disruptions to health care. We found differences by race/ethnicity in trusted sources of information about COVID. Black women had higher odds of choosing TV as their most trusted source of information, while White women were more likely to cite government or social service agencies as their most trusted source. Notably, 15% of women said they did not trust any source of information regarding COVID-19. COVID-19 disproportionately impacts populations with high levels of mistrust towards medical and government institutions, a result of the twin legacies of medical mistreatment and structural racism. Our findings underscore the need for innovative strategies to reach these groups with accurate and timely information.

Keywords

Health communication, COVID-19, Criminal justice, Racial disparities, Trust, Women

Introduction

As of 2017, there were 1.25 million women under control of the criminal legal (CL) system in the United States, including over 225,000 women in jails or prisons [1,2] and over a million women under community supervision (probation or parole) [3]. Women involved in the CL system live at the nexus of several drivers of the U.S. COVID-19 pandemic, including incarceration, poverty, chronic illness and racism [4]. They are predominantly low-income and disproportionately women of color [5]. They have markedly higher rates of underlying chronic health conditions, associated with poor COVID-19 outcomes, than women in the general population [6,7]. In addition, hundreds of thousands of women transition between community and carceral settings each year [8], and prisons and jails continue to be revealed as hotbeds of COVID-19 transmission [9]. Thus, COVID-19 is very much a pertinent risk for women who are involved in the CL system in the U.S [10].

In the U.S., the story of COVID-19 is one of distinct and marked racial/ethnic disparities, with Black and Hispanic/Latinx people afflicted by disproportionately high rates of infection [11-13] and death [14,15], In addition, the socioeconomic consequences of COVID-19, such as loss of employment and eviction from housing, disproportionately affect people of color [16,17] People of color are also overrepresented among those employed in jobs with high risk of exposure, such as home health aides, cashiers and meat packing workers [18]. Another central theme of the pandemic in the U.S. is the lack of a coordinated national response, leading to different policies and public health mandates in different regions of the country. The lack of a single authoritative source of guidance contributes to confusion and people relying on widely divergent sources of information about the virus. With this backdrop, we sought to understand how women with CL involvement were affected by COVID-19 early in the pandemic. Specifically, we examined how COVID-19 had affected their health care and what sources of information about the virus they relied on. The purpose was to determine whether there were regional or racial/ethnic differences in these outcomes, to help inform health care and communication efforts.

Materials and Methods

Research participants were enrolled in an ongoing, three-city study of cervical cancer risk among women involved in the CL system, funded by the National Cancer Institute (R01CA226838). Data are collected annually with a cohort of women in community settings in three U.S. cities: Kansas City (Midwest), Birmingham (South) and Oakland (West). In response to anecdotal evidence about challenges and disruptions created by the pandemic in the study population, we conducted a brief supplemental survey (5-10 mins) over eight weeks from mid-April to mid-June 2020. Interviews were conducted by telephone rather than in person due to shelter-in-place orders. Participants received a $20 incentive for responding to the survey. Regular check-ins with participants was a routine part of the research protocol and was approved in accordance with the National Institutes of Health single institutional review board policy for multisite research.

Measures

The primary independent variables were race/ethnicity and study site (city). Participants were asked “How do you identify in terms of your race or ethnicity (select all that apply)?” and read a list of several different racial/ethnic groups. We used responses to create a three-level nominal categorical variable race variable. A majority of participants endorsed one race, predominantly Black or White. Small numbers of women reported more than one race (n=10), Latinx only (n=17), American Indian or Alaska Native (n=1), or Asian or Pacific Islander (n=4). We combined these women into a single category as “Other People of Color (POC).” While useful for analytic purposes, we do not draw conclusions about this group in our findings, as we would be generalizing from numerous racial/ethnic backgrounds. Site was determined by the city in which interviews were conducted. To assess health care utilization, participants were asked “Has a health care provider canceled or postponed any regular appointments due coronavirus?” and “Have any of your health care appointments been conducted by phone or video (Telemedicine) instead of in person, due to the coronavirus?” which were both coded yes vs. no. Perceived susceptibility to COVID-19 was assessed with an item which asked, “On a scale of 1-10, how likely do you think you are to get the coronavirus, with 1 being not at all likely and 10 being certain to get it?” Dependent variables related to sources of information about COVID-19. Participants were asked, “What are your sources of information about COVID-19? (select all that apply)” and read a list of potential sources. Each source was dichotomized yes vs. no. To determine most trusted source of information, participants were asked a follow-up question, “Which single source do you trust the most?” Rather than use a multi-level variable, we dichotomized these responses (most trusted y/n) for a more precise examination of associations.

Data Analysis

Descriptive statistics were conducted for all study variables. Logistic regressions were used to determine the unadjusted odds ratios (ORs) and 95% confidence intervals (CIs) for the associations between outcomes and race. Adjusted ORs and 95% CIs for the associations between outcomes and race were examined controlling for study site, age, and other relevant factors (depending on the model). Analyses were run in STATA Version 16.1 (Stata Corp., College Station, TX, USA).

Results

We successfully reached 73% of the study cohort by telephone during the data collection period, for a sample of 344 women (Table 1). Race/ethnicity varied by site, with more White women in Kansas City and Birmingham. Mean age also varied by site, with a mean of 39 years in Kansas City, 40 in Birmingham and 46 in Oakland. All women had histories of criminal legal involvement, most having experienced both incarceration and community supervision (probation or parole). Women in Oakland were more likely to have health insurance, a result of California expanding Medicaid coverage under the Affordable Care Act in 2014. Despite this, three-quarters of all women had attended at least one health care visit by appointment in the past year. In addition, over half had sought care at a hospital Emergency Department (Table 1).

Table 1: Participant characteristics and health care by racial group.

All Black White Other POC p.
(N=344) (n=205) (n=98) (n=41)
n (%) n (%) n (%) n (%)
Oakland 181 (52.8) 146 (71.2) 16 (16.3) 19 (47.5) 0.001
Birmingham 93 (27.1) 35 (17.1) 53 (54.1) 5 (12.5)
Kansas City 69 (20.1) 24 (11.7) 29 (29.6) 16 (40.0)
Ever incarcerated 332 (96.5) 197 (97.0) 94 (96.9) 41 (100.0) 0.530
Ever probation or parole 315 (91.6) 183 (90.2) 92 (93.9) 40 (97.6) 0.205
Has health insurance 251 (73.0) 177 (86.8) 42 (43.3) 32 (78.1) 0.001
Health care by appointment past year 263 (76.5) 173 (84.4) 59 (60.2) 31 (75.6) 0.001
Medical appointment cancelled or postponed due to COVID-19 146 (42.4) 104 (50.7) 30 (30.6) 12 (29.3) 0.001
Medical care by tele-medicine due to COVID-19 152 (44.2) 108 (52.7) 30 (30.6) 14 (34.2) 0.001
Tested for COVID-19 66 (19.2) 44 (21) 12 (12) 4 (10) 0.054

Health Care Since COVID-19

Nearly half of women reported having medical appointments postponed or cancelled due to the COVID outbreak. However, many women also reported receiving health care by telemedicine (Table 2). The odd of having an appointment cancelled or postponed was significantly higher among Black women, after controlling for location, age and health insurance (Table 3). However, Black women also had higher odds of having a telemedicine appointment as a consequence of the outbreak. We found no differences by geographical region in COVID-related impacts on scheduled health care, once we controlled for race, age and health insurance (data not shown). Sixty (17%) of the women had been tested for COVID over the data collection period (April-June 2020), a timeframe in which testing resources were scarce. Two women reported a positive result. Testing was more common in Oakland, where 23% of women were tested, compared to 13% in Kansas City and 11% in Birmingham (p=0.027). Perceived susceptibility to COVID-19 was low overall: on a scale of 1 (not at all likely) to 10 (extremely likely), the mean score was 3.7 [SD 2.8]. Women in Oakland rated their susceptibility slighter higher (4.1) than women in Kansas City (3.2) or Birmingham (3.6) (p=0.041). There were no significant racial/ethnic differences in perceived susceptibility (data not shown).

Table 2: Most trusted source of information about COVID-19 by racial/ethnic group.

All Black White Other POC p.
(N=344) (n=205) (n=98) (n=41)
n (%) n (%) n (%) n (%)
Television news 147 (42.7) 104 (50.7) 31 (31.6) 12 (29.3) 0.001
Social media or websites 35 (10.2) 17 (8.3) 10 (10.2) 8 (19.5) 0.095
Friends/family 18 (5.2) 8 (3.9) 7 (7.1) 3 (7.3) 0.404
Government/social service agency 30 (8.7) 8 (3.9) 17 (17.4) 5 (12.2) 0.001
Medical provider 44 (12.8) 21 (10.2) 16 (16.3) 7 (17.1) 0.227
Other 17 (4.9) 10 (4.9) 5 (5.1) 2 (4.9) 0.996
Don’t trust any source 52 (15.1) 36 (17.6) 12 (2.2) 4 (9.8) 0.286

Table 3: Logistic regression of COVID-19 related health care experiences by race/ethnicity.

Model 1 Model 2 Model 3
Care cancelled/postponed Telemedicine visit Tested for COVID-19
AOR* (95% CI) p. AOR* (95% CI) p. AOR** (95% CI) p.
Race/ethnicity
African American Referent Ref Ref
White 0.53 (0.29-0.98) 0.045 0.50 (0.27-0.92) 0.027 0.85 (0.37-1.94) 0.698
Other POC 0.43 (0.20, 0.93) 0.033 0.56 (0.27-1.19) 0.131 0.54 (0.18-1.66) 0.181

*Adjusted for study site, insurance status and had 1> medical appointment past year.

**Adjusted for study site, age and insurance status.

Sources of Information about COVID-19

Most women reported multiple sources of information about COVID-19, with a mean of 2.4 [SD 1.1]. Television news was the most frequently cited source of information regarding COVID-19 (83%), followed by social media/websites (61%) and friends/family (43%). Other sources of information included government or social service agencies (21%), medical providers (19%) and radio (6%). When asked to identify their single most trusted source of information, over half of women chose television news (Table 2). While many women endorsed friends and family as a source of information, very few (5%) cited them as their most trusted source. Similarly, a relatively small proportion of women (13%) said medical providers were their most trusted source of information about COVID-19. Black women had higher odds of choosing TV as the most trusted source than the other groups of women, after controlling for age and study site (Table 4). White women had higher odds of citing government or social service agencies as their most trusted source of information (Table 4). It is noteworthy that fifteen percent of women said they did not trust any source of information about COVID-19. This was higher among Black women but did not reach statistical significance in regression controlling for age and site. We found no significant regional differences in information sources or most trusted sources once controlling for race and age in regression analysis (data not shown).

Table 4: Logistic regression models of most trusted source of COVID-19 information by race/ethnicity.

Model 1 Model 2 Model 3
Television News Web/social media Gov’t/social service
AOR* (95% CI) p. AOR* (95% CI) p. AOR* (95% CI) p.
Race/ethnicity
African American Referent Ref Ref
White 0.33 (0.18,0.59) 0.001 1.61 (0.62,4.21) 0.328 7.48 (2.61, 21.38) 0.001
Other POC 0.39 (0.18,0.85) 0.018 2.91 (1.10,7.69) 0.031 2.90 (0.79,10.64) 0.108

*Adjusted for study site and age.

Discussion

Our examination of health care-related effects of COVID-19 among women with CL involvement found mixed results. While over 40% of women reported having health care appointments cancelled or postponed due to COVID-19, a roughly equal proportion received care by telemedicine, and there were no differences by region. This is consistent with a rapid uptick in telehealth visits for publicly insured people in urban areas throughout the U.S. in April-June 2020 [19]. The higher prevalence of COVID-19 testing in Oakland is likely a reflection of the more aggressive stance California took towards controlling infection, compared to the Midwest (Kansas/Missouri) and Southern (Alabama) states. Given this higher level of activity to address the pandemic, it is not surprising that the mean level of perceived susceptibility to COVID-19 was also higher among women Oakland, CA. Our findings regarding trusted sources of COVID-19 information did not vary by region; however, they revealed some interesting variations by race/ethnicity. Black women were significantly less likely than White women to choose government institutions or social services agencies as their most trusted source of information about the virus. In addition, very few Black women identified health care providers as their most trusted source. The long history of racism in government and criminal justice policies in the United States likely contributes to this mistrust [20,21], as does the legacy of unequal treatment and abuse in U.S. medicine [20,22] Restorative work with communities of color is needed to address medical mistrust [23,24], particularly if a future vaccine is to be widely accepted among vulnerable groups [25]. Finally, it is striking that a notable proportion of women (15%) said they didn’t trust ANY source of information regarding COVID-19. This suggests an urgent need to investigate and implement innovative, non-traditional avenues for delivering public health information.

There are several substantial limitations to this study. While data were collected from women in different regions of the United States, the sample is not nationally representative of women involved in the CL system. Due to the exigencies of conducting data collection rapidly in the context of shelter-in-place orders, we were only able to reach three-quarters of women in the parent study. It is possible those we were unable to reach were having different experiences; for example, it is possible that some were hospitalized with the virus. The potential of socially desirable response choices is always present with self-report data, although our questions didn’t focus on typically stigmatized behaviors.

The COVID-19 pandemic has brought into sharp relief the underlying social drivers of poor health in the U.S., including racism, poverty and incarceration. In addition to affecting their health, these conditions affect the level of trust individuals put in social, medical and public health institutions. A U.S. national poll conducted in August 2020 found that, if a COVID-19 vaccine were made available, 45% of Black and 44% of Hispanic/Latinx people would not choose to be vaccinated, compared to 30% of Whites [26]. The need for accurate, trusted health communication to address this public health crisis is clear. It is incumbent on public health professionals to identify new, innovative avenues for public health messaging to vulnerable groups, and to improve the perceived trustworthiness of more traditional sources of information.

Acknowledgements

This research was supported by the U.S. National Cancer Institute (grant #R01CA226838) and the U.S. National Institute of Minority Health and Health Disparities (grant #R01MD010439). The authors thank the women who shared their experiences for the study, despite the disruption and uncertainty created by the COVID-19 pandemic.

References

    1. Bronson J, Carson E (2019) Prisoners in 2017, Bureau of Justice Statistics, (eds.). Office of Justice Programs: Washington DC.
    2. Zeng Z (2019) Jail Inmates in 2017 Bureau of Justice Statistics (eds.) Office of Justice Programs: Washington, DC.
    3. Kaebele D, Alper M (2020) Probation and Parole in the United States, 2017-2018, Bureau of Justice Statistics (eds.) Office of Justice Programs: Washington DC.
    4. Krieger N (2020) ENOUGH: COVID-19, Structural Racism, Police Brutality, Plutocracy, Climate Change—and Time for Health Justice, Democratic Governance, and an Equitable, Sustainable Future. American Journal of Public Health e1-e4. [crossref]
    5. The Sentencing Project (2020) Fact Sheet: Incarcerated Women and Gils. Available from: https://www.sentencingproject.org/publications/incarcerated-women-and-girls/.
    6. Binswanger IA, Krueger PM, Steiner JF (2009) Prevalence of chronic medical conditions among jail and prison inmates in the USA compared with the general population. J Epidemiol Community Health 63: 912-919.
    7. Hawks L, Emily A Wang, Benjamin Howell, Steffie Woolhandler, David U Himmelstein, et al. (2020) Health Status and Health Care Utilization of US Adults Under Probation: 2015-2018. Am J Public Health 110: 1411-1417. [crossref]
    8. Office of the Assistant Secretary for Planning and Evaluation (2020) Incarceration and Reentry. Available from: https://aspe.hhs.gov/incarceration-reentry.
    9. Akiyama MJ, Spaulding AC, Rich JD (2020) Flattening the Curve for Incarcerated Populations – Covid-19 in Jails and Prisons. N Engl J Med 382: 2075-2077. [crossref]
    10. Ramaswamy M, Jordana Hemberg, Alexandra Faust, Joi Wickliffe, Megan Comfort, et al. (2020) Criminal Justice-Involved Women Navigate COVID-19: Notes From the Field. Health Educ Behav 47: 544-548. [crossref]
    11. Rozenfeld Y, et al. (2020) A model of disparities: risk factors associated with COVID-19 infection. Int J Equity Health 19: 126.
    12. Millett GA, Austin T Jones, David Benkeser, Stefan Baral, Laina Mercer, et al. (2020) Assessing differential impacts of COVID-19 on black communities. Ann Epidemiol 47: 37-44. [crossref]
    13. Poteat T, Gregorio A Millett, LaRon E Nelson, Chris Beyrer (2020) Understanding COVID-19 risks and vulnerabilities among black communities in America: the lethal force of syndemics. Ann Epidemiol 47: 1-3. [crossref]
    14. Wadhera RK, Priya Wadhera, Prakriti Gaba, Jose F Figueroa, Karen E Joynt Maddox, et al. (2020) Variation in COVID-19 Hospitalizations and Deaths Across New York City Boroughs. JAMA 323: 2192-2195. [crossref]
    15. Rodriguez-Diaz CE, Vincent Guilamo-Ramos, Leandro Mena, Eric Hall, Brian Honermann, et al. (2020) Risk for COVID-19 infection and death among Latinos in the United States: Examining heterogeneity in transmission dynamics. Ann Epidemiol. [crossref]
    16. United States Bureau of Labor Statistics, Supplemental data measuring the effects of the coronavirus (COVID-19) pandemic on the labor market. 2020, United States Department of Labor: Washington DC.
    17. Institute TA (2020) The COVID-19 Eviction Crisis: an Estimated 30-40 Million People in America Are at Risk. Available from: https://www.aspeninstitute.org/blog-posts/the-covid-19-eviction-crisis-an-estimated-30-40-million-people-in-america-are-at-risk/
    18. Centers for Disease Control and Prevention (2020) Coronavirus disease: Health equity considerations and racial and ethnic minority groups. Available from: https://www.cdc.gov/coronavirus/2019-ncov/community/health
    19. ASPE (2020) Medicare beneficiary use of telehealth visits: Early data from the start of the COVID-19 pandemic, A.S.f.P.a. Evaluation, Editor. United States Department of Health and Human Services: Washington DC.
    20. Spigner C (2007) Medical Apartheid: The dark history of medical experimentation on Black Americans from colonial times to the present. Journal of the National Medical Association 99: 1074. [crossref]
    21. Binswanger IA, Nicole Redmond, John F Steiner, Leroi S Hicks (2012) Health disparities and the criminal justice system: an agenda for further research and action. J Urban Health 89: 98-107. [crossref]
    22. Arnett MJ, Thorpe RJ, Gaskin DJ, Bowie JV, LaVeist TA (2016) Race, Medical Mistrust, and Segregation in Primary Care as Usual Source of Care: Findings from the Exploring Health Disparities in Integrated Communities Study. Journal of Urban Health: Bulletin of the New York Academy of Medicine 93: 456-467. [crossref]
    23. Parsons S (2020) Addressing Racial Biases in Medicine: A Review of the Literature, Critique, and Recommendations. Int J Health Serv Pg no: 20731420940961. [crossref]
    24. Sullivan LS (2020) Trust, Risk, and Race in American Medicine. Hastings Cent Rep 50: 18-26. [crossref]
    25. Jamison AM, Quinn SC, Freimuth VS (2019) “You don’t trust a government vaccine”: Narratives of institutional trust and influenza vaccination among African American and white adults. Soc Sci Med 221: 87-94. [crossref]
    26. Marist Institute for Public Opinion (2020) NPR/PBS NewsHour/Marist Poll Results: Election 2020, Trump, & the Issues. Available from: http://maristpoll.marist.edu/npr-pbs-newshour-marist-poll-results-election-2020-trump-the-issues/#sthash.fm1RIlI9.dpbs.

Discharge Dilemma: COVID 19 Positive Patients from Hospital

Abstract

COVID 19 pandemic started as cluster of unexplained Pneumonia in Wuhan, China. More than 5 million cases have been reported so far. The disease process is variable, poorly understood and is evolving. It is highly infectious and main mode of transmission is person to person. Therefore, stringent public health measures have been in place such as social distancing, personal and hand hygiene, lockdown strategies etc to minimise the transmission. In hospital medicine, safe discharge and arranging a follow up of COVID positive patient poses a challenge and currently there are no clear guidelines available due to uncertainty of infectivity in patients (both immune competent and immune compromised). Safe discharging is very essential to restrict further cluster and outbreak of COVID19 in community.

Why is Safe Discharging Important? Infectivity and Transmission

WHO mission to China report mentioned that SARS-CoV-2 virus can be detected 1-2 days prior to onset of symptoms in nasal-oropharyngeal samples, can persist for 7-12 days in moderate cases and up to 2 weeks in severe cases [1]. Viral RNA is also detectable in faeces 4-5 weeks after symptom onset in approximately 30% of cases; however its clinical significance is not known [1]. In Singapore, prolonged viral shedding from upper airway aspirates was reported and in some cases up to at least 24 days after the onset of symptoms [2].Transmission of SARS-CoV-2 from asymptomatic individuals (or individuals within the incubation period) has also been well documented [3].

Zouet all reported that viral load is similar in both symptomatic and asymptomatic groups. Patients with no or modest symptoms had detectable viral RNA for at least 5 days indicating risk of transmission from asymptomatic patients [4].

The biologic basis for this is supported by a study of a SARS-CoV-2 outbreak in a long-term care facility, in which infectious virus was cultured from reverse transcription polymerase chain reaction (RT-PCR)-positive upper respiratory tract specimens in pre-symptomatic and asymptomatic patients as early as six days prior to the development of typical symptoms [5]. There is no data or study to determine the longest documented transmission from an asymptomatic person. Viral RNA can persist over long periods of time in bodily fluids. This does not necessarily mean that the person is still infectious. Isolation of viruses in virus culture is needed to show infectivity. Based on the data obtained it is uncertain to determine when exactly the patient will be non-infective and if precautions are not placed can lead to further outbreaks in community, which can lead to further burden on health care facilities.

Clinical Problem

Suspected and positive COVID-19 patients attending hospitals are Isolated as per clear pathways and all necessary precautions are taken with appropriate PPE. Some patients have mild respiratory compromise with normal radiographs, some have bilateral infiltrates and some are intubated and ventilated in ICU/HDU. Some patients were admitted for other medical conditions in hospital and were screened for concerns (exposure to COVID patients or clinical concerns) and were positive.

The varied presentation, spectrum and uncertainty about the illness pose a clinical challenge to arrange a safe discharge and follow up. Some of the challenges faced by our COVID teamat time of discharge of COVID patient when medically fit, stable or do not need any intervention in hospital are:

• When do you discharge COVID positive patients?

• Where do you discharge the patients? e.gin clinical situations where an elderly patient living on their own or with little support who lost mobility due to recent bilateral pneumonia/significant illness or patient who are clinically very well but have a family member at home who is immunocompromised?

• When do the patients become clear of infection?

• Is the onset of symptom history from patient reliable or the reference point should be when they were positive?

• Do COVID positive patients need any follow up?

• When do you re-image them if they had infiltrates?

• Do they need any formal respiratory follow up and is there a need of lung function testing?

• If the patients develop any new symptoms after discharge and are presumed to be non-infective as per current guidelines and re-present to the hospital, should they be isolated and retested because that can potentially expose other admitted patients?

• If the repeat swab or re-presentation to hospital is negative, is one negative swab enough to admit them in a general ward?

• What about immunocompromised, and patients with persistently positive swabs? Is their infectivity similar to the immunocompetent patients?

Current Clinical Guidelines for De-isolation of COVID-19 Cases

COVID-19 patients discharge planning is done by taking into account the existing capacity of healthcare, laboratory and diagnostic resources and the epidemiological situation at the time of discharge in that particular area. Some of the current clinical guidelines for de-isolation are:

1) Ministero della salute, Consiglio Superiore di Sanità, Italy (28 February 2020) -A COVID-19 patient can be considered cured after the resolution of symptoms and 2 negative tests for SARS-CoV-2 at 24-hour intervals. For patients who clinically recover earlier than 7 days after onset, an interval of 7 days between the first and the final test is advised.

2) CDC USA (Interim guidance) – Negative rT-PCR results from at least 2 consecutive sets of nasopharyngeal and throat swabs collected ≥ 24 hours apart from a patient with COVID-19 (a total of four negative specimens) and resolution of fever, without use of antipyretic medication, improvement in illness signs and symptoms.

3) CHINA CDC– Patients meeting the following criteria can be discharged: Afebrile for >3 days, Improved respiratory symptoms, pulmonary imaging shows obvious absorption of inflammation, and nucleic acid tests negative for respiratory tract pathogen twice consecutively (sampling interval ≥ 24 hours).

After discharge, patients are recommended to continue 14 days of isolation management and health monitoring, wear a mask, live in a single room with good ventilation, reduce close contact with family members, eat separately, keep hands clean and avoid outdoor activities. It is recommended that discharged patients should have follow-up visits after 2 and 4 weeks.

4) European Centre of Disease Prevention and Control Guidelines:

• Clinical criteria (e.g. no fever for > 3 days, improved respiratory symptoms, pulmonary imaging showing obvious absorption of inflammation, no hospital care needed for other pathology, clinician assessment)

• Laboratory evidence of SARS-CoV-2 clearance in respiratory samples; 2 to 4 negative RT-PCR tests for respiratory tract samples (nasopharynx and throat swabs with sampling interval ≥ 24 hours). Testing at a minimum of 7 days after the first positive RT-PCR test is recommended for patients that clinically improve earlier.

• Serology: appearance of specific IgG when an appropriate serological test is available.

Recommendations

Our suggestion is to classify patients who are deemed suitable for discharge from hospital, into mild, moderate and severe category based on certain clinical and radiological features. Our suggestion is to discharge patients to home or convalescent facility depending on patient’s physical, functional and home situation.

Mild Cases

Patients with no radiographic abnormalities and patient who did not require supplemental oxygen or had exercise induced desaturation to be classified as mild cases prior to discharge.

Moderate Cases

Patients with infiltrates or abnormalities on imaging requiring supplemental oxygen, who do not have significant co-morbid condition and good functional baseline, who did not require assisted ventilation can be classed as Moderate Cases prior to discharge.

Severe Cases

Patients, who had severe illness requiring NIV/High Flow Nasal Cannula/Mechanical Ventilation or had significant co-morbid conditions, or have had decline in functional capacity due to severe illness, would be classified as Severe Cases of COVID infection.

A discharge for mild cases may be considered to home if patient can isolate himself at home (e.g. single room with good ventilation, face-mask wear, reduced close contact with family members, separate meals, good hand sanitation, no outdoor activities) with follow up phone calls by specially designated health care provider due to the risk of worsening of the clinical symptoms, keeping in view the delayed onset of cytokine storm.

Moderate cases may be discharged home if they can self isolate and they are provided with Pulse oximeters and thermometers for home monitoring for further 7 days. They should be linked in with specially designated clinical nurse specialist for twice daily monitoring of symptoms and recording parameters. If patients are technology savvy and able to update symptoms and parameters on App either on Smartphone or computer, an App can be designed for maintain data of such patients and monitored centrally.

In severe cases that have experienced functional decline in terms of mobility, cognition and activities of daily living should be discharged to step-down facility with rehabilitation and multidisciplinary facility (physiotherapy, occupational therapy, pulmonary rehabilitation and geriatrician input). If the patient is not able to self-isolate due to reasons such as living in accommodation with multiple people, hostel or with immunocompromised and elderly population discharge to step down/convalescent facility speciallydesignated for similar cases should be considered to minimise cluster of infections.

COVID positive patients who had infiltrates/pneumonia or opacification on chest radiograph should have a follow up imaging to look for resolution. The timing of repeat imaging is uncertain due to the phenomenon of viral shedding and unclear infectivity of the disease. Our suggestion would be to repeat radiography 8 weeks after the onset of symptoms as viral shedding has not been observed after 6 weeks.

Current evidence suggesting viral shedding in bodily fluids for 6 weeks makes de-isolation decision difficult. At present, de-isolation guidance are unclear with a lot of institutional variability. The timeframe for de-isolation can only be provided after robust clinical trials exploring the infectivity of viral shedding in the bodily fluids to avoid clustering and re-infection. Antibody testing seems to be of benefit in cases that are immunocompromised or were COVID positive for prolonged duration. Patients who were immunocompromised or remained COVID positive on re-swabbing should be isolated on the side of precaution if they re-present to the hospital with a different medical problem.

A COVID team consisting of member of representative of medical team, infection control, microbiologist, occupational therapist and public health should have a daily meeting to determine appropriate discharge to reduce burden on health care an prevent community outbreaks.

References

  1. World Health Organization (2020) Report of the WHO-China Joint Mission on Coronavirus Disease 2019 (COVID-19). Geneva: WHO.
  2. Young BE, Ong SWX, Kalimuddin S, Low JG, Tan SY, et al. (2020) Epidemiologic features and clinical course of patients infected with SARS-CoV-2 in Singapore. JAMA.
  3. Rothe C, Schunk M, Sothmann P, Bretzel G, Froeschl G, et al.(2020) Transmission of 2019-nCoV Infection from an Asymptomatic Contact in Germany.N Engl J Med 382: 970.
  4. Zou L, Ruan F, Huang M, Liang L, Huang H, et al. (2020) SARS-CoV-2 Viral load in upper respiratory specimens of infected patients. New England Journal of Medicine 382: 1177-1179. [crossref]
  5. Arons MM, Hatfield KM, Reddy SC, Kimball A, James A, et al.(2020) Presymptomatic SARS-CoV-2 Infections and Transmission in a Skilled Nursing Facility:N Engl J Med.

Severe Spinal Column Deformity from Scoliosis with Harrington Rods Implant


Severe scoliotic deformity of the thoracolumbar spine imposes a significant anesthesia challenge for non-spine surgery. Patients with severe scoliosis are at increased risk for perioperative morbidity and mortality due to underlying pulmonary and cardiac dysfunctions [1-3]. Stress, pain, mechanical ventilation, and surgery-induced inflammation can further increase the risk of postoperative cardiopulmonary failure. We present a preoperative chest radiograph demonstrating extensive thoracolumbar scoliosis with Harrington rods implant, anatomic distortion, and bony dysmorphism (Panel A, white arrow). The patient underwent a living donor kidney transplant under general anesthesia. Preoperative anesthesia and surgical planning is crucial and should focus on airway difficulty, ventilation management, positioning, new kidney location, and postoperative pain management.

The kidney transplant is a heterotopic transplant surgery meaning the kidney is placed in a different location than existing kidneys. The new kidney is on the right or left side of the abdomen to allow the donor kidney to be easily anastomosed surgically to blood vessels and the bladder of the recipient. Due to the extensive deformity of the spinal column and right chest wall (Panel B, black arrow), the operation was performed in the left lateral decubitus position. Moreover, the donor kidney was placed to the right iliac fossa to decrease the risk of left lung atelectasis, restricted breathing, and sprinting from pain.

Ultrasound-guided quadratus lumborum was difficult in this patient due to atrophy of trunk muscles, chronic scarring, and artifacts from the implant, which required careful assessment of anatomical landmarks to perform a successful nerve block.

AWHC-3-4-324-g001

References

  1. APA Bradford, David S, Tay B, Hu S (1999) Adult Scoliosis: Surgical Indications, Operative Management, Complications, and Outcomes. Spine24: 2617-2629. [crossref]
  2. Albert TJ, Purtill J, Mesa J, McIntosh T, Balderston RA (1995) Health outcome assessment before and after adult deformity surgery. A prospective study. Spine 20: 2002-2005. [crossref]
  3. Kulkarni Anand H, Ambareesha M (2007) Scoliosis and anaesthetic considerations. Indian Journal of Anaesthesia. 51: 486-495

Application of Drainage Position Ventilation and Real- Time Bedside Monitoring in Mechanical Ventilation of Patients Infected with nCov-19

Abstract

At present, the new coronavirus has spread to more than 200 countries and regions around the world. Up to now, no specific antiviral drugs are proved effective in defeating the new coronavirus, some measures, such as postural drainage ventilation, real-time bedside pulmonary ultrasound and chest electrical impedance monitoring may provide some new ideas for mechanical ventilation patients infected with new coronavirus.

Keywords

New coronavirus, ARDS, Mechanical ventilation, Bioelectrical impedance tomography, Pulmonary ultrasound

Etiology and Pathogenesis

The novel coronavirus (2019-nCoV) belongs to the beta genus of coronavirus, the S protein of the new coronavirus binds to the angiotensin-converting enzyme 2 (ACE2) receptor of human alveolar type II epithelial cells, and then enters into the cell to replicate and spread through respiratory droplets and contact [1].

Clinical Manifestation

Fever, dry cough and fatigue are the main symptoms of the people infected with novel coronavirus. Critically ill patients usually have dyspnea and (or) hypoxemia one week after the onset of the disease. Some patients can rapidly progress to acute respiratory distress syndrome, septic shock, uncorrectable metabolic acidosis, coagulation dysfunction and multiple organ failure [1].

Chest Imaging

Chest radiographs showed multiple small patch shadows and interstitial changes in the lungs, especially in the lateral pulmonary zone in the early stage of the patients infected with new coronavirus. Then it developed into multiple ground glass shadows and infiltration shadows in both lungs, and in severe cases, lung consolidation could occur [1-3].

Pulmonary Pathophysiology

Lung pathology showed focal hemorrhage and necrosis, marked proliferation of the type II alveolar epithelial cells in the lung tissue. Serous, fibrin exudates, and hyaline membrane formation were seen in the alveolar cavity; it could also be observed that the alveolar septal vascular congestion and edema, and some alveolar exudates organization and pulmonary interstitial fibrosis. Part of the bronchial mucosa epithelium was shed; mucus and mucus emboli could be seen in the bronchial lumen. A small number of alveoli were over-inflated, the alveolar septum was broken or the cysts were formed [4].

Thus, critically ill patients infected with new coronavirus may present abnormal pathophysiological changes such as obstructive ventilation disorder, lung gas exchange disorder, imbalanced ventilation blood flow ratio, and increased shunt.

Antiviral Therapy

During the emergency clinical trial of antiviral drugs, a number of randomized, double-blind, antiviral-placebo controlled studies have been carried out, but no antiviral drugs proved effective in treating the new coronavirus infection.

Mechanical Ventilation

Early and appropriate invasive mechanical ventilation is an important treatment for critically ill patients. In general, when PaO2/FiO2 is less than 150 mmHg, the effect of high flow oxygen therapy or noninvasive ventilation is not good, endotracheal intubation should be considered in time for invasive mechanical ventilation in severe and critical ill cases [2]. The strategies of lung protective mechanical ventilation and lung recruitment are implemented. If there is no contraindication, it is suggested to implement prone position ventilation at the same time. Prone position ventilation can improve oxygenation in patients with ARDS by increasing functional residual volume, improving ventilation/blood flow ratio (V/Q), reducing shunt (Qs/Qt), improving diaphragmatic movement and promoting secretion excretion. In the airway management, posture drainage and sputum suction by bronchoscope should be adopted to promote the sputum drainage and lung rehabilitation [2].

Lung Protective Mechanical Ventilation Strategy

The individualized strategy of mechanical ventilation is to adopt the most suitable methods or parameters in ventilation mode, lung recruitment, tidal volume, PEEP and mechanical ventilation posture for patients according to their different pathophysiological conditions, so as to achieve the best treatment effect. At present, low tidal volume, high PEEP, lung recruitment and prone position ventilation are widely used in patients infected with new coronavirus [2]. The characteristics of severe new coronavirus cases, such as inflammatory serous and fibrin exudate, exudate organization, pulmonary fibrosis, alveolar septum destruction, atelectasis and pulmonary bullae, coexist in the patients’ lung [4]. Large tidal volume is not suitable for patients infected with new coronavirus due to the potential mechanical ventilation lung injury [2]. The selection of PEEP should be guided by the best pulmonary mechanics, the reduction of pulmonary shunt, the improvement of oxygenation and the function of stable circulation, while the effect of pulmonary recruitment should be examined by CT, MRI, bioelectrical impedance tomography (EIT) and ultrasound imaging. In the process of lung recruitment, there is the possibility of lung over inflation and the original pulmonary injury aggravation, and the effect on the hemodynamics should be concerned at the same time. The optimal method, opportunity and parameters of lung recruitment have not been determined, but it is necessary to judge the potential of pulmonary reinflation under real-time bedside EIT and ultrasound pulmonary monitoring.

The Advantage of Real Time Bedside Monitoring of EIT and Ultrasound

The goal-oriented mechanical ventilation is to adjust the mechanical ventilation strategy in time with the aim of imaging, respiratory and oxygen dynamics monitoring, blood gas examination, the function of circulatory system and the condition of other organs [2]. Blood oxygen saturation, blood gas, hemodynamics and respiratory mechanics are still routine and convenient monitoring methods of mechanical ventilation. Traditional lung images, such as X-ray, CT, MRI, certainly have the characteristics of clear images and easy analysis and diagnosis, but they are complicated to operate under the special circumstances of isolation and transportation of patients infected with new coronavirus. The chest electrical impedance tomography cannot provide clear image, but it is convenient to operate and can be continuously imaged [5]. Ultrasound lung images also have unique advantages in the diagnosis of pneumonia and the effect of ventilation [6]. These two methods can be real-time bedside monitoring, which are simple and practical to guide lung recruitment, to diagnose pneumonia, and to evaluate the mechanical ventilation effectiveness. In addition, while monitoring respiratory mechanics and oxygenation parameters during mechanical ventilation, we should pay close attention to the corresponding changes in the circulatory system and make timely adjustments.

Electrical Impedance Tomography

Electrical Impedance Tomography (EIT) is to use the impedance changes of living organisms or biological tissues, biological organs, and biological cells under the action of a safe current below the excitability threshold to obtain the organism internal resistance rate of distribution and changing images through image reconstruction [5,7]. The resistivity of different tissues or the same tissue under different physiological and pathological conditions is different. The periodic changes of air and blood flow in the lungs together determine the changes in the electrical impedance of the chest. The advantage of EIT lies in the use of the rich physiological and pathological information carried by bio-impedance to obtain damage-free functional imaging and medical image monitoring. Chest X-rays and CT are widely used in the diagnosis of lung infections. But they cannot monitor lung lesions in real time, cannot measure lung ventilation status, and most importantly cannot be used in patients with severe pneumonia and respiratory failure who cannot easily access these examination, so their application are limited. Lung EIT, as a brand new medical imaging technology, which is different from traditional imaging technology and conventional lung function monitoring, has outstanding features such as injury-free, portable, low-cost, functional imaging, and image monitoring. EIT can real-time dynamic monitor the pulmonary ventilation and blood flow distribution, evaluate the effectiveness of clinical treatment methods such as mechanical ventilation by measuring electrical resistance under different ventilation conditions [5,7].

At present, the commonly used methods to monitor the effectiveness of lung recruitment strategy and the suitability of PEEP include arterial blood gas analysis, peripheral oxygen saturation, pulmonary and chest maximum compliance, static pressure volume curve and so on, but these methods cannot meet the requirements of dynamic monitoring of regional lung perfusion. A number of studies have showed that in mechanical ventilation patients with ARDS, EIT has been used to accurately measure the whole lung and regional lung ventilation distribution, to show the influence of PEEP changes on alveolar expansion and collapse by gradually increasing and decreasing PEEP level, and in the end to obtain the optimal value of PEEP, which improves the ratio of ventilation and blood flow (V/Q), and plays an important role in individulized lung protective ventilation strategy [5,7].

Pulmonary Ultrasound

Bedside lung ultrasound can be used for the diagnosis and differential diagnosis of various lung diseases by using a low-frequency convex probe of 3 to 5 MHz and a high-frequency linear probe of 8 to 12 MHz [8]. Normal lung ultrasound images include bat sign, lung sliding sign, and A-line. Pathological images mainly include abnormal pleural lines, pulmonary consolidation, interstitial syndrome, fragmentation sign, dynamic bronchial signs, pleural effusion and so on [9].

With the development of ultrasound technology, pulmonary ultrasound is gradually found to be of great value in diagnosing acute respiratory distress syndrome, pulmonary edema, pneumonia, pneumothorax, pulmonary embolism and so on [6,10,11]. It can be used to monitor the changes in lung ventilation, to guide clinical fluid management and evaluate prognosis, especially in patients with severe diseases. Since chest X-rays and CT examinations are unsuitable for rapid diagnosis of critical diseases due to the shortages of inconvenient carrying, radiation exposition, poor reproducibility, position limitations, and high costs, and compared with chest CT, bedside lung ultrasound has advantages of non-invasive, dynamic and repeatable observation of patients with lung disease.

The Advantage of Drainage Position Ventilation

At present, prone position mechanical ventilation is widely used in patients infected with new coronavirus, which may be helpful to the drainage of pulmonary inflammation and the reduction of pulmonary shunt volume [2]. So far, no effective antiviral drugs have been found in defeating new coronavirus, so drainage becomes an important treatment for pulmonary inflammatory lesions. Because of inflammatory lesions in different parts of the lung, prone position ventilation is not suitable for all patients, and it may be more beneficial to adopt drainage position mechanical ventilation combined with tracheal suction with the infected side of lung lesions upper side. For example, the lateral and head-down position mechanical ventilation with the inflammatory lung upper side according to the characteristics of pulmonary imaging of some patients infected with new coronavirus. The lateral prone position can be tried to improve the inflammatory side lung ventilation, reduce pulmonary shunt, increase blood reflux and improve hemodynamics. However, it is important to avoid excessive head down, which increases abdominal pressure on the chest cavity.

In summary, based on the autopsy, clinical manifestations, lung pathological characteristics and present treatment of the patients infected with the new coronavirus, this article describes some possible improvement measures for the mechanical ventilation strategy. We believe that postural drainage ventilation, real-time bedside pulmonary ultrasound and chest electrical impedance monitoring will improve the clinical treatment of critical patients based on the previous guidelines for ARDS treatment. These methods provide some new ideas for clinical treatment and need to be used and verified in future clinical work.

References

  1. Guan WJ, Ni ZY, Hu Y, Liang WH, Ou CQ, et al. (2020) Clinical characteristics of coronavirus disease 2019 in China. N Engl J Med.
  2. Lingzhong Meng, Haibo Qiu, Li Wan, Yuhang Ai, Zhanggang Xue, et al. (2020) Intubation and Ventilation amid the COVID-19 Outbreak: Wuhan’s Experience. Anesthesiology 132: 1317-1332. [crossref]
  3. Huang C, Wang Y, Li X, Ren L, Zhao J, et al. (2020) Clinical features of patients infected with 2019 novel coronavirus in Wuhan, China. Lancet 395: 497-506.
  4. Qin Liu, Rongshuai wang, Guoqiang Qu, Yunyun wang, Pan Liu, et al. (2020) Gross Observation Report on the Autopsy of a nCov-2019 Pneumonia Death. Journal of Forensic Medicine (Chinese) 36: 21-23. [crossref]
  5. Hsu CF, Cheng JS, Lin WC, Cheng KS, Lin SH, et al. (2016) Electrical impedance tomography monitoring in acute respiratory distress syndrome patients with mechanical ventilation during prolonged positive end-expiratory pressure adjustments [J]. J Formos Med Assoc 115: 195-202. [crossref]
  6. Staub LJ, Mazzali Biscaro RR, Kaszubowski E, Maurici R (2019) Lung ultrasound for the emergency diagnosis of pneumonia, acute heart failure, and exacerbations of chronic obstructive pulmonary disease / asthma in adults: a systematic review and meta-analysis. J Emerg Med 56: 53-69. [crossref]
  7. Heines SJH, Strauch U, Van de Poll MCG, Paul MHJR, Dennis CJJB (2018) Clinical implementation of electric impedance tomography in the treatment of ARDS: a single centre experience [J]. J Clin Monit Comput. [crossref]
  8. Rouby JJ, Arbelot C, Gao YZ, Zhang M, Lv J, et al. (2018) APECHO Study Group. Training for lung ultrasound score measurement in critically ill patients. Am J Respir Crit Care Med 198: 398-401. [crossref]
  9. Lichtenstein DA (2015) BLUE-protocol and FALLS-protocol: two applications of lung ultrasound in the critically ill. Chest 147: 1659-1670.
  10. Chavez MA, Shams N, Ellington LE, Naithani N, Gilman RH, et al. (2014) Lung ultrasound for the diagnosis of pneumonia in adults: a systematic review and meta-analysis. Respir Res 15: 50. [crossref]
  11. Long L, Zhao HT, Zhang ZY, Wang GY, Zhao HL (2017) Lung ultrasound for the diagnosis of pneumonia in adults: a meta-analysis. Medicine (Baltimore) 96: e5713. [crossref]

Self-Recovery of Pancreatic Beta Cell’s Insulin Secretion Based on 10+ Years Annualized Data of Food, Exercise, Weight, and Glucose Using GHMethod: Math-Physical Medicine (No. 339)

Abstract

The author was inspired from reading two recently published medical papers regarding pancreatic beta cells insulin secretion or diabetes reversal via weight reduction. The weight reduction is directly related to the patient’s lifestyle improvement through diet and exercise. He has published six medical papers on beta cells based on different stages in observations of his continuous glucose improvements; therefore, in this article, he will investigate food ingredients, meal portions, weight, and glucose improvement based on his 10+ years of collected big data.

Here is the summary of his findings:

  1. His successful weight reduction, from 220 lbs. in 2010 to 171 lbs. in 2020, comes from his food portion reduction and exercise increase.
  2. His lower carbs/sugar intake amount, from 40 grams in 2010 to 12 grams in 2020, is resulted from his learned food nutrition knowledge and meal portion reduction, from 150% in 2010 to 67% in 2020.
  3. His weight reduction contributes to his FPG reduction, from 220 mg/dL in 2010 to 104 mg/dL in 2020. His carbs/sugar control and increased walking steps, from 2,000 steps in 2010 to ~16,000 steps in 202, have contributed to his PPG reduction, from 300 mg/dL in 2010 to 109 mg/dL in 2020. When both FPG and PPG are reduced, his daily glucose is decreased as well, from 280 mg/dL in 2010 to 108 mg/dL in 2020.
  4. His damaged beta cell’s insulin production and functionality, most likely, have been repaired about 16% for the past 6 years or 27% in the past 10 years at a self-repair rate of 2.7% per year.

The conclusion from this paper is a 2.7% annual beta cells self-repair rate which is similar to his previously published papers regarding his range of pancreatic beta cells self-recovery of insulin secretion with an annual rate between 2.3% to 3.2%.

To date, the author has written seven papers discussing his pancreatic beta cell’s self-recovery of insulin secretion. In his first six papers [1-7], he used several different “cutting angles” or “analysis approaches” to delve deeper into this complex biomedical subject and achieved consistent results within the range of 2.3% to 3.2% of annual self-recovery rate.

He used a quantitative approach with precision to discover and reconfirm his pancreatic beta cell’s health state by linking it backwards step-by-step with his collected data of glucose, weight, diet, and exercise. He has produced another dataset for a self-repair rate of 2.7% which is located right in the middle between 2.3% and 3.2% from his previous findings.

In his opinion, type 2 diabetes (T2D) is no longer a non-reversible or non-curable disease. Diabetes is not only “controllable” but it is also “self-repairable”, even though at a rather slow rate. He would like to share his research findings and his persistent efforts from the past decade with his medical research colleagues and to provide encouragement to motivate other T2D patients like himself to reverse their diabetes conditions.

Introduction

The author was inspired from reading two recently published medical papers regarding pancreatic beta cells insulin secretion or diabetes reversal via weight reduction. The weight reduction is directly related to the patient’s lifestyle improvement through diet and exercise. He has published six medical papers on beta cells based on different stages in observations of his continuous glucose improvements; therefore, in this article, he will investigate food ingredients, meal portions, weight, and glucose improvement based on his 10+ years of collected big data.

Methods

Background

To learn more about his developed GH-Method: math-physical medicine (MPM) research methodology, readers can review his article, Biomedical research methodology based on GH-Method: math-physical medicine (No. 54 and No. 310), in Reference [1] to understand his MPM analysis method.

Diabetes History

In 1995, the author was diagnosed with severe type 2 diabetes (T2D). His daily average glucose reached 280 mg/dL with a peak glucose at 398 mg/dL and his HbA1C was at 10% in 2010. Since 2005, he has suffered many kinds of diabetes complications, including five cardiac episodes (without having a stroke), foot ulcer, renal complications, bladder infection, diabetic retinopathy, and hypothyroidism.

As of 9/30/2020, his daily average glucose is approximately 106 mg/dL and HbA1C at 6.1%. It should be mentioned that he started to reduce the dosage of his three different diabetes medications (maximum dosages) in early 2013 and finally stop taking them on 12/8/2015. In other words, his glucose record since 2016 to the present is totally “medication-free”.

Beginning on 1/1/2012, he started to collect his weight value in the early morning and his glucose values four times a day: FPG x1 in the early morning and PPG x3 at two hours after the first bite of each meal. Since 1/1/2014, he also started to collect his carbs/sugar amount in grams and post-meal walking steps. Prior to these two dates, especially during the period of 2010 to 2012, the manually collected biomarkers and lifestyle details were scattered and unorganized. Therefore, those annualized data from 2010 to 2012 or 2014 were guesstimated values with his best effort. It should be further mentioned that on 1/1/2013, he began to reduce his dosages of three diabetes educations step by step. By 1/1/2015, he was only taking 500 mg of Metformin for controlling his diabetes conditions. Finally, he completely ceased taking Metformin on 12/8/2015; therefore, since 1/1/2016, his body has been completely free of any diabetes medications.

Other Research Results

Recently, a Danish medical research team has published an article on JAMA which emphasizes a strengthen lifestyle program can “reverse” T2D. This program includes a weekly exercise (5-6 times and 30-60 minutes each time), daily walking more than 10,000 steps using smart phone to keep a record, personalized diet and nutritional guidance by healthcare professionals, etc. The observed results from this Danish report are patients’ overall HbA1C reduction of 0.31%, and their diabetes medication dosage reduction from 73% to 26%.

DiRECT research report from UK also indicated that an aggressive weight reduction program can induce improvement on diabetes conditions. This UK program includes low-calories diet for 3-5 months with 825-853 K-calories per day, plus daily walking of 15,000 steps per day. The observed results from this UK report are patients’ overall HbA1C reduction of 0.9%, weight reduction of 10 kg (or 22 lbs.), and reduced diabetes medication dosage as well.

The Author’s Approach

Inspired by the results from the two European studies and based on his own collected big data over the past 10+ years, from 2010 to 2020, he decided to conduct a similar research on his own. He has separated his 10+ years data into two periods. The first period of 5 years, from 2010 to 2014, with partially collected and partially guesstimated data under different degrees of medication influence, and the second period of 6 years, from 2015 to 2020, with a complete set of collected raw data stored in software and severs without any medication influence.

His trend of thoughts include a sequence from cause to consequence as listed below from top to bottom:

  • Food and meal’s portion %
  • K-calories per day
  • Weight (lbs.)
  • FPG (mg/dL)
  • Carbs/sugar intake (grams)
  • Walking
  • PPG (mg/dL)
  • Daily glucose (mg/dL)

He has further conducted nine calculations of correlation coefficient based on the above parameters to examine the degree of connections between any 2 elements of these total 8 parameters. It should be mentioned that the correlation coefficients can only be done between two data sets, or two curves.

More importantly, in addition to examining the raw data, he also placing an emphasis on the annual change rate percentage, its trend, and their comparisons of these 8 parameters.

Results

Figure 1 shows his background data table which includes his calculated annual averages of the 8 parameters plus proteins, fat, and daily K-calories, based on his daily data collected during 2010 to 2020.

fig 1

Figure 1: Background data table.

Figure 2 depicts the annual change rate percentage of his food (meal portion %, K-calories, and carbs/sugar) and his weight. In this figure, meal portion and weight have similar change rates which means the less he eats, the lighter his weight. Also, carbs/sugar amount and K-calories have similar change rates which means the less his K-calories, the less his carbs/sugar intake amount.

fig 2

Figure 2: Annual change rates of Weight and Food (meal portion, K-calories, and carbs/sugar).

Figure 3 illustrates the similar trend of annual data of his weight and three food components (meal portion, K-calories, and carbs/sugar amount).

fig 3

Figure 3: Annual change rates of Weight and Food (meal portion, K-calories, and carbs/sugar).

Exercise is a missing component from this figure which is also essential on weight reduction. The more he eats, the higher intake amounts of his K-calories and his carbs/sugar as well. During the past decade on his effort for weight reduction, he has focused on reducing both of his meal portion percentage and carb/sugar intake amount. As a result, he was able to reduce his weight from 220 lbs (100 kg) and his average glucose from 280 mg/dL in 2010 to 171 lbs. (78 kg) and 106 mg/dL in 2020 (without any medication).

Figure 4 reflects the annual change rate percentage of his daily glucose, weight and carbs/sugar amount. In this figure, the change rates of his glucose and weight are remarkably similar, almost a mirror image, which indicates the lower his weight, the lower his glucose. This finding matches the two European studies and the common knowledge possessed by healthcare professionals. The reason for the obviously mismatched change rates between carbs/sugar and glucose or weight is due to the missing component of exercise which is equally important on glucose reduction.

fig 4

Figure 4: Annual change rates of Weight, Glucose, and Carbs/sugar.

Figure 5 focuses exclusively on the relationships among data of glucose, carbs/sugar, and exercise. The positive correlation coefficient between glucose and carbs/sugar is expressed by these two similar moving trends. On the other hand, the negative correlation coefficient between glucose and exercise (walking) is expressed by these two opposite moving trends.

fig 5

Figure 5: Annual data of Weight, Glucose, and Carbs/sugar.

Figures 6-8 collectively collective together to show the 9 sets of calculated correlation coefficients among those 8 listed elements in above section of Methods. A better illustration of these three figures can be found in a table, where all of the calculated correlations are above 90%, which means they are highly connected to each other (Figure 9). Even the correlation of -89% between glucose and walking exercise is also extremely high in a negative manner.

fig 6

Figure 6: Correlation coefficients among Weight, K-calories, meal portion.

fig 7

Figure 7: Correlation coefficients among Weight, Glucose, Carbs/sugar.

fig 8

Figure 8: Correlation coefficients among PPG, Carb/sugar, Walking, FPG, Weight.

fig 9

Figure 9: A combined data table of 9 correlation coefficients among 8 elements.

Figure 10 reveals the detailed annual change rates of 8 elements for a 10+ year period from 2010 to 2020. It should be pointed out that his average change rates within 6 years from 2015 through 2020 are 2.7% per year for both FPG and PPG, and 3.4% for daily glucose. This conclusion is similar to his six previously published papers regarding his pancreatic beta cell’s self-recovery rate of insulin secretion. Most likely, his beta cells insulin production and functionality have been repaired about 16% during the past 6 years or 27% during the past 10 years at a self-repair rate of 2.7% per year.

fig 10

Figure 10: A combined data table of annual change rates of 7 elements, especially glucose change rates of 2.7%.

Here is the summary of his findings:

  1. His successful weight reduction, from 220 lbs. in 2010 to 171 lbs. in 2020, comes from his food portion reduction and exercise increase.
  2. His lower carbs/sugar intake amount, from 40 grams in 2010 to 12 grams in 2020, is resulted from his learned food nutrition knowledge and meal portion reduction, from 150% in 2010 to 67% in 2020.
  3. His weight reduction contributes to his FPG reduction, from 220 mg/dL in 2010 to 104 mg/dL in 2020. His carbs/sugar control and increased walking steps, from 2,000 steps in 2010 to ~16,000 steps in 202, have contributed to his PPG reduction, from 300 mg/dL in 2010 to 109 mg/dL in 2020. When both FPG and PPG are reduced, his daily glucose is decreased as well, from 280 mg/dL in 2010 to 108 mg/dL in 2020.
  4. His damaged beta cell’s insulin production and functionality, most likely, have been repaired about 16% for the past 6 years or 27% in the past 10 years at a self-repair rate of 2.7% per year.

Summary

To date, the author has written seven papers discussing his pancreatic beta cell’s self-recovery of insulin secretion. In his first six papers [2-7], he used several different “cutting angles” or “analysis approaches” to delve deeper into this complex biomedical subject and achieved consistent results within the range of 2.3% to 3.2% of annual self-recovery rate.

He used a quantitative approach with precision to discover and reconfirm his pancreatic beta cell’s health state by linking it backwards step-by-step with his collected data of glucose, weight, diet, and exercise. He has produced another dataset for a self-repair rate of 2.7% which is located right in the middle between 2.3% and 3.2% from his previous findings.

In his opinion, type 2 diabetes (T2D) is no longer a non-reversible or non-curable disease. Diabetes is not only “controllable” but it is also “self-repairable”, even though at a rather slow rate. He would like to share his research findings and his persistent efforts from the past decade with his medical research colleagues and to provide encouragement to motivate other T2D patients like himself to reverse their diabetes conditions.

References

  1. Hsu, Gerald C. eclaireMD Foundation, USA. “GH-Method: Methodology of math-physical medicine, No. 54 and No. 310.”
  2. Hsu, Gerald C. eclaireMD Foundation, USA. “Changes in relative health state of pancreas beta cells over eleven years using GH-Method: math-physical medicine (No. 112).”
  3. Hsu, Gerald C. eclaireMD Foundation, USA. “Probable partial recovery of pancreatic beta cells insulin regeneration using annualized fasting plasma glucose via GH-Method: math-physical medicine (No. 133).”
  4. Hsu, Gerald C. eclaireMD Foundation, USA. “Probable partial self-recovery of pancreatic beta cells using calculations of annualized fasting plasma glucose using GH-Method: math-physical medicine (No. 138).”
  5. Hsu, Gerald C. eclaireMD Foundation, USA. “Guesstimate probable partial self-recovery of pancreatic beta cells using calculations of annualized glucose data using GH-Method: math-physical medicine (No. 139).”
  6. Hsu, Gerald C. eclaireMD Foundation, USA. “Relationship between metabolism and risk of cardiovascular disease and stroke, risk of chronic kidney disease, and probability of pancreatic beta cells self-recovery using GH-Method: Math-Physical Medicine (No. 259).”
  7. Hsu, Gerald C. eclaireMD Foundation, USA. “Self-recovery of pancreatic beta cell’s insulin secretion based on annualized fasting plasma glucose, baseline postprandial plasma glucose, and baseline daily glucose data using GH-Method: math-physical medicine (No. 297).”